
| The essentials: On September 25 to 28, 2026, the FDA approved Degevma (denosumab-adet, Teva Pharmaceutical Industries) as a biosimilar to Xgeva (denosumab, Amgen) across all indications of the reference product. Degevma is indicated for: prevention of skeletal-related events (SREs) in patients with multiple myeloma; prevention of SREs in patients with bone metastases from solid tumors; treatment of giant cell tumor of bone in adults and skeletally mature adolescents; and treatment of hypercalcemia of malignancy. The active molecule is identical to Xgeva: denosumab 120 mg/1.7 mL solution for injection in a vial, administered subcutaneously. The approved dose and schedule mirror Xgeva across all four indications. Teva’s naming: Degevma shares the biosimilar suffix -adet with PONLIMSI (denosumab-adet), Teva’s biosimilar to Prolia (denosumab) approved in March 2026 for osteoporosis and hormone therapy-related bone loss indications. Together, Degevma and PONLIMSI constitute Teva’s comprehensive denosumab biosimilar portfolio spanning both Amgen denosumab reference products and their distinct indications. Degevma is already approved in the European Union (November 18, 2025). Regulatory basis: totality of evidence, including analytical and clinical data demonstrating no clinically meaningful differences from Xgeva in safety, purity, and potency. Clinical support references the pivotal Xgeva trials, including the randomized double-blind trial demonstrating that denosumab delayed skeletal-related events versus zoledronic acid in patients with bone metastases. Interchangeability status: not designated as interchangeable at this time. Teva has announced a U.S. commercial launch for both Degevma and PONLIMSI in the coming months. Not yet on the market at time of publication. Important distinction from PONLIMSI: Degevma is dosed at 120 mg every 4 weeks for bone metastases and multiple myeloma indications, and at higher doses for giant cell tumor of bone and hypercalcemia. PONLIMSI covers the Prolia indications (60 mg every 6 months for osteoporosis). These are not interchangeable products. |
|---|
Denosumab is one of the most widely used drugs in oncology bone health, and one of the most expensive. As covered in HED’s earlier post on PONLIMSI (denosumab-adet), Teva’s biosimilar to Prolia approved in March 2026, the denosumab biosimilar market has been building for years. But that post focused on osteoporosis and the Prolia reference product. Degevma is a different product for a different patient population: people with cancer whose tumors have spread to bone, or whose tumor itself involves bone directly.
The distinction between Prolia and Xgeva is not a branding distinction. They are the same molecule at different doses, for different indications, governed by different clinical evidence bases, and reimbursed through different coverage pathways. Prolia is dosed at 60 mg every 6 months; Xgeva is dosed at 120 mg every 4 weeks. Prolia goes through pharmacy benefit coverage; Xgeva is typically reimbursed through the medical benefit as a physician-administered drug. Mixing them up is a meaningful medication safety issue.
Degevma (denosumab-adet, Teva) is the Xgeva biosimilar. It completes Teva’s full denosumab portfolio alongside PONLIMSI, giving the company a biosimilar option for every denosumab-eligible patient regardless of which condition they are being treated for.
Denosumab and the RANK/RANKL Axis in Cancer-Related Bone Disease
To understand why Degevma matters, it helps to understand what Xgeva does and why bone metastases are such a serious clinical problem.
Bone metastases occur when cancer cells from a primary tumor travel through the bloodstream or lymphatic system and colonize bone tissue. They are common in advanced cancers, particularly breast cancer, prostate cancer, lung cancer, kidney cancer, and multiple myeloma. Once established, bone metastases are rarely curable. The clinical focus shifts to preventing the complications they cause: skeletal-related events (SREs), defined as pathologic fracture, the need for radiation or surgery to bone, spinal cord compression, and hypercalcemia.
SREs cause significant pain, reduce mobility and independence, and are associated with worse survival. Preventing them is a meaningful clinical goal in a population already managing advanced cancer.
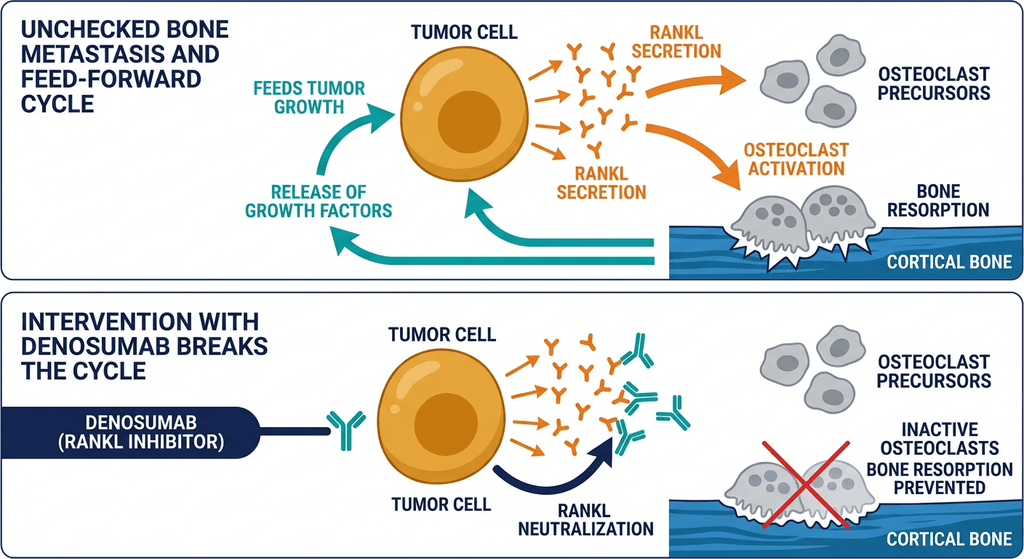
The mechanism by which bone metastases cause these complications runs through the RANK/RANKL pathway. RANKL (receptor activator of nuclear factor kappa-B ligand) is a protein produced by osteoblasts, bone marrow stromal cells, and crucially, by tumor cells themselves in the bone microenvironment. RANKL binds to its receptor RANK on the surface of osteoclast precursors, driving their maturation, activation, and survival. Activated osteoclasts resorb bone, releasing growth factors stored in the bone matrix that further stimulate tumor cell proliferation, creating a destructive feed-forward cycle between the tumor and the bone.
Denosumab, the molecule in both Xgeva and its biosimilars, is a fully human monoclonal antibody that binds RANKL with high affinity, preventing it from activating RANK. By neutralizing RANKL, denosumab suppresses osteoclast activity, reduces bone resorption, decreases the feed-forward tumor-bone cycle, and substantially reduces the incidence of skeletal-related events in patients with bone metastases or multiple myeloma.
The pivotal clinical evidence for Xgeva demonstrated that denosumab 120 mg every 4 weeks delayed time to first SRE compared to zoledronic acid (a bisphosphonate bone-protective agent) in large randomized trials in breast cancer, prostate cancer, and other solid tumors with bone metastases. This evidence base is what Degevma’s biosimilar approval references.
Degevma’s Four Approved Indications and What Each Means Clinically
Degevma covers all four of Xgeva’s indications, which address distinct patient populations and clinical scenarios.
Prevention of skeletal-related events in bone metastases from solid tumors
The broadest and most commonly used indication. Adults with solid tumor cancers (breast, prostate, lung, kidney, and others) that have metastasized to bone and who are at risk for SREs receive Degevma 120 mg subcutaneously every 4 weeks. The goal is to reduce fracture risk, reduce the need for radiation or surgical bone intervention, and prevent spinal cord compression. Denosumab’s head-to-head trial data showed it delayed time to first SRE by a median of 8.2 months versus zoledronic acid in breast cancer bone metastases.
Prevention of skeletal-related events in multiple myeloma
Multiple myeloma is a plasma cell malignancy of the bone marrow that directly activates osteoclasts through RANKL-mediated mechanisms, causing osteolytic lesions that produce severe bone pain and pathologic fractures. Denosumab was approved specifically for multiple myeloma following the Phase 3 20060358 study demonstrating noninferiority to zoledronic acid for time to first SRE. The myeloma indication provides patients and oncologists an alternative to zoledronic acid, particularly important for patients with renal impairment, since zoledronic acid requires renal dose adjustment and carries nephrotoxicity risk.
Treatment of giant cell tumor of bone
Giant cell tumor of bone (GCTB) is a rare, locally aggressive primary bone tumor in which the stromal cells express high levels of RANKL, driving extensive osteoclast recruitment and bone destruction. Denosumab targets the fundamental driver of GCTB’s bone destruction, shrinking the tumor and allowing surgery in patients previously considered inoperable due to tumor location or extent. The GCTB indication covers adults and skeletally mature adolescents. The dosing is more intensive during the loading phase: 120 mg subcutaneously every 4 weeks with additional 120 mg doses on days 8 and 15 of the first month.
Treatment of hypercalcemia of malignancy
Hypercalcemia of malignancy (HCM) is a life-threatening complication of advanced cancer occurring when excessive bone resorption releases calcium into the blood at rates that overwhelm the kidneys’ ability to excrete it. It affects approximately 20 to 30% of cancer patients at some point. Denosumab addresses HCM driven by osteolytic bone metastases through RANKL-mediated osteoclast suppression, and also addresses HCM driven by tumor PTHrP secretion. The indication covers patients refractory to bisphosphonate therapy, where denosumab provides a meaningful rescue option.
The Regulatory Basis for Approval
The FDA based Degevma’s approval on a totality of evidence, consistent with the standard framework for biosimilar approvals. This included:
Analytical data: Extensive physicochemical and structural characterization demonstrating that denosumab-adet produced by Teva’s manufacturing process is highly similar to Xgeva in structure, purity, and functional activity, including RANKL binding affinity and RANK activation inhibition.
Clinical data: A randomized, double-blind, controlled clinical trial demonstrating comparable pharmacokinetics, pharmacodynamics, efficacy, safety, and immunogenicity between Degevma and Xgeva in the proposed biosimilar population.
Preclinical data: Nonclinical studies supporting the totality-of-evidence package.
The FDA concluded there are no clinically meaningful differences between Degevma and Xgeva in safety, purity, or potency. This conclusion supports the full extrapolation of the approval to all four Xgeva indications, a standard approach in biosimilar regulation that avoids requiring separate clinical trials for each individual indication.
How Degevma Fits Into the Xgeva Biosimilar Market
Degevma enters a market where Xgeva biosimilar competition has been slower to develop than the Prolia biosimilar space. Wyost (denosumab-bbdz, Sandoz), the first FDA-approved Xgeva biosimilar, launched in late 2024 and has begun gaining market share, though uptake has been modest for the same structural reasons discussed in HED’s PONLIMSI post: Amgen’s rebate practices and the physician-administered route of administration (Part B rather than Part D) create different dynamics than traditional pharmacy-dispensed drugs.
Degevma is Teva’s entry into the Xgeva biosimilar space, aligning with the company’s broader strategy of building out its denosumab franchise across both reference products. Teva has not yet disclosed pricing for Degevma or PONLIMSI in the United States. The European approval of Degevma in November 2025 preceded the U.S. approval, consistent with the Prolia biosimilar experience where European competition preceded U.S. competition.
Interchangeability status: Degevma does not carry an interchangeability designation at this time, meaning a pharmacist cannot automatically substitute it for Xgeva without prescriber authorization in most U.S. states. This mirrors the situation with most denosumab biosimilars, including PONLIMSI, and limits the speed at which formulary switching can occur at the payer level.
Critical clinical safety note: Degevma (Xgeva reference) and PONLIMSI (Prolia reference) share the same biosimilar suffix (-adet) and the same active molecule, but they are not interchangeable with each other. They are dosed differently, indicated for different conditions, and covered through different benefit structures. Substituting one for the other would constitute a dosing error. Prescribers, pharmacists, and payers must clearly distinguish between the two products.
Safety: What the Prescribing Information Covers
The safety profile of Degevma is consistent with the well-established safety experience of Xgeva across its clinical development and post-marketing history.
Osteonecrosis of the jaw (ONJ): ONJ is the most important serious adverse event associated with denosumab at Xgeva doses. It involves avascular necrosis of jawbone tissue, typically precipitated by invasive dental procedures (tooth extractions, dental implants, oral surgery) during denosumab therapy. The risk increases with duration of exposure. Patients should undergo a dental examination and complete any necessary dental work before initiating Degevma. Invasive dental procedures should be avoided during treatment whenever possible, and patients should inform their dentist they are on a RANKL inhibitor.
Hypocalcemia: Suppressing osteoclast activity reduces the ongoing release of calcium from bone, which can lower serum calcium levels, particularly in patients with pre-existing vitamin D deficiency, renal impairment, or those receiving high-dose denosumab. Calcium and vitamin D supplementation is required unless hypercalcemia is present. Serum calcium should be monitored, especially during the first weeks of treatment.
Atypical femoral fractures: Long-term RANKL inhibition suppresses bone remodeling, which can reduce the bone’s ability to repair microfractures. Atypical subtrochanteric and diaphyseal femoral fractures, distinct from the usual osteoporotic fractures, have been reported with prolonged denosumab use. Patients with new thigh or groin pain during treatment should be evaluated.
Embryo-fetal toxicity: Denosumab can cause fetal harm. Women of reproductive potential should use effective contraception during treatment and for at least 5 months after the last dose. Pregnancy exposure warrants immediate discussion with the treating oncologist.
Infections: Suppression of RANKL-mediated immune functions, particularly in the respiratory tract, may be associated with an increased risk of serious infections including cellulitis. Patients should be counseled to report signs of infection promptly.
What This Means for Oncologists, Pharmacists, and Patients
For oncologists and oncology pharmacists
Degevma provides an additional biosimilar option for the Xgeva indications across all four approved populations: solid tumor bone metastases, multiple myeloma, GCTB, and HCM refractory to bisphosphonates. Whether and when to prescribe Degevma versus Xgeva or Wyost will depend on formulary placement, payer coverage, and institutional protocols.
The most important clinical point for teams managing denosumab therapy is the clear separation between Degevma (Xgeva reference, 120 mg/4 weeks) and PONLIMSI (Prolia reference, 60 mg/6 months). The shared biosimilar suffix -adet may create confusion at the prescribing, dispensing, and administration level. Institutional ordering systems should clearly distinguish the two, and oncology pharmacists should build in verification steps to prevent the two products from being mixed up.
For related HED coverage on the broader denosumab biosimilar landscape and the access dynamics in the Prolia biosimilar market, see our earlier post on PONLIMSI (denosumab-adet), the 19th denosumab biosimilar and Teva’s biosimilar to Prolia, and why U.S. denosumab biosimilar savings have been more modest than European markets.
For patients
If you are receiving Xgeva (denosumab 120 mg every 4 weeks) for bone protection during cancer treatment or for giant cell tumor of bone, Degevma is the same active drug from a different manufacturer. Your oncologist or oncology team may eventually offer a transition to Degevma based on your insurance formulary or availability. The clinical effect should be the same.
The dental and calcium supplementation requirements described above apply equally to Degevma as to Xgeva. Before starting or continuing any denosumab therapy, inform your dentist, maintain adequate calcium and vitamin D intake unless otherwise directed, and report any new jaw pain, thigh pain, or signs of infection to your oncology team.
The Bone Health and Osteoporosis Foundation and the American Cancer Society maintain current resources on bone protection during cancer treatment and managing bone metastases.
Sources
Teva FDA approval press release: Teva Continues Biosimilar Momentum with U.S. FDA Approval of DEGEVMA (denosumab-adet), a Biosimilar to Xgeva (denosumab). ir.tevapharm.com. September 28, 2026.
Drugs.com approval news: FDA Approves Degevma (denosumab-adet), a Biosimilar to Xgeva. drugs.com. September 28, 2026.
Center for Biosimilars (Teva completes denosumab pair, full indication coverage, Sandoz first-mover context): Teva Completes Denosumab Biosimilar Pair With FDA Nod for Degevma. centerforbiosimilars.com. September 2026.
BioPharm International (totality of evidence standard, analytical and clinical data package, all four indications): Teva’s Denosumab-Adet (Degevma) Approved as Xgeva Biosimilar. biopharminternational.com. September 2026.
Clinical Trial Vanguard (Sandoz first-mover, pathway inclusion critical, EU approval November 2025): FDA Approves Teva’s DEGEVMA Biosimilar to Xgeva for Cancer Bone Complications. clinicaltrialvanguard.com. September 2026.
Endocrinology Advisor (RANKL mechanism, bioequivalence confirmation, dosing): Teva’s Xgeva Biosimilar Degevma Gets FDA Nod. endocrinologyadvisor.com. September 2026.
BioPharmWatch (Teva Pivot to Growth context, comprehensive denosumab portfolio framing): FDA Approves Teva’s DEGEVMA Biosimilar to Xgeva for Cancer Bone Complications. biopharmawatch.com. September 2026.
Bone metastases overview: Bone Metastases. StatPearls. NCBI.
HED companion post (PONLIMSI, Prolia biosimilar, denosumab market dynamics): Prolia Costs $2,500 a Dose. There Are Now 19 Biosimilar Competitors. healthevidencedigest.com.
Degevma prescribing information: DEGEVMA (denosumab-adet) Prescribing Information. Teva Pharmaceutical Industries. 2026.
Degevma approval history: Degevma FDA Approval History. drugs.com.
Patient resources: Bone Health and Osteoporosis Foundation | American Cancer Society bone health resources | Teva Degevma patient information
| Disclaimer: Health Evidence Digest provides general information about FDA approvals and health research for educational purposes. This content is not a substitute for professional medical advice. Degevma (denosumab-adet) is a biosimilar to Xgeva (denosumab 120 mg) and is not interchangeable with PONLIMSI (denosumab-adet, biosimilar to Prolia 60 mg); prescribers and pharmacists must clearly distinguish between these two products with the same biosimilar suffix. Degevma has not been designated as interchangeable with Xgeva and requires prescriber authorization for substitution in most U.S. states. All denosumab therapy decisions should be made in consultation with a qualified oncologist or appropriate specialist. |
|---|
Leave a Reply