Author: Melina Rodriguez, CST/CMA/CCA

  • Tudriqev (Vusolimogene Oderparepvec) Receives FDA Accelerated Approval in Combination With Nivolumab for Unresectable Advanced Cutaneous Melanoma After Progression on Anti-PD-1 Therapy

    Tudriqev (Vusolimogene Oderparepvec) Receives FDA Accelerated Approval in Combination With Nivolumab for Unresectable Advanced Cutaneous Melanoma After Progression on Anti-PD-1 Therapy

    The essentials: On August 6, 2026, the FDA granted accelerated approval to Tudriqev (vusolimogene oderparepvec-wtpg, Replimune Group) in combination with nivolumab for adult patients with unresectable advanced cutaneous melanoma who experienced disease progression on a programmed death receptor-1 (PD-1)-blocking antibody-based regimen. Tudriqev is a genetically modified herpes simplex virus type 1 (HSV-1) oncolytic viral therapy, injected directly into accessible tumors. It is the first oncolytic viral immunotherapy approved in the United States since talimogene laherparepvec (Imlygic) in 2015, and the first approved specifically for patients who have already progressed on anti-PD-1 therapy, one of the most poorly served populations in advanced melanoma. The regulatory path: the application received two Complete Response Letters before this approval: CRL 1 in July 2025 and CRL 2 in April 2026. The trial design did not change across submissions. On July 30, 2026, the FDA’s Cellular, Tissue, and Gene Therapies Advisory Committee voted 10 to 3 that the efficacy data were evaluable and clinically meaningful. Accelerated approval followed one week later. The clinical basis: IGNYTE trial (single-arm, open-label, n=140 enrolled; 91-patient efficacy-evaluable population comprising those with at least one non-injected lesion). Objective response rate: 24.2%. Median duration of response: 14.1 months. The efficacy-evaluable population included 80% with Stage IV disease and 13% with prior anti-PD-1 treatment plus ipilimumab. Approval is based on ORR and DOR as surrogate endpoints. Continued approval may be contingent on verification of clinical benefit in the confirmatory Phase 3 IGNYTE-3 trial (NCT06264180), which is ongoing and randomizes patients to Tudriqev plus nivolumab versus physician’s choice (nivolumab plus relatlimab, anti-PD-1 rechallenge, or single-agent chemotherapy), with overall survival as the primary endpoint. What the drug is: an HSV-1 oncolytic virus engineered with three genetic modifications: deletion of ICP34.5 (reduces neurovirulence and promotes tumor-selective replication); deletion of ICP47 (restores antigen presentation to immune cells); insertion of GALV-GP-R minus (a fusogenic glycoprotein that enhances tumor killing through cell-to-cell fusion and immunogenic death); and insertion of GM-CSF (a cytokine that recruits dendritic cells and macrophages to the tumor site to amplify the systemic immune response). Administration: intratumoral injection at accessible lesions every 2 weeks for 8 doses. First dose at lower concentration; subsequent 7 doses at higher concentration. Volume per injection determined by lesion size. Regulatory designations: Breakthrough Therapy Designation; Priority Review. Adverse reactions: mild; included fatigue, pyrexia, infections, chills, musculoskeletal pain, nausea, and diarrhea. No treatment-related deaths in IGNYTE. IGNYTE-3 for confirmatory OS data is the key post-approval milestone.

    Anti-PD-1 therapy, the checkpoint inhibitor approach that transformed advanced melanoma over the past decade, does not work for everyone. The patients it does not work for, those who progress despite pembrolizumab or nivolumab, face a clinical situation where options narrow sharply. Ipilimumab can provide benefit in some, as can BRAF/MEK inhibition for patients with BRAF-mutant disease. But the population that has progressed on PD-1 blockade and exhausted or is ineligible for these alternatives has historically had few good options, and the available data on clinical outcomes in this setting are sobering.

    Anti-PD-1 refractory melanoma is a type of advanced skin cancer that no longer responds to immune checkpoint blockade, which is a common component of standard-of-care treatment. Despite ongoing therapy, tumors in this population can continue to grow through mechanisms that help them evade immune detection, leaving clinicians with few effective options.

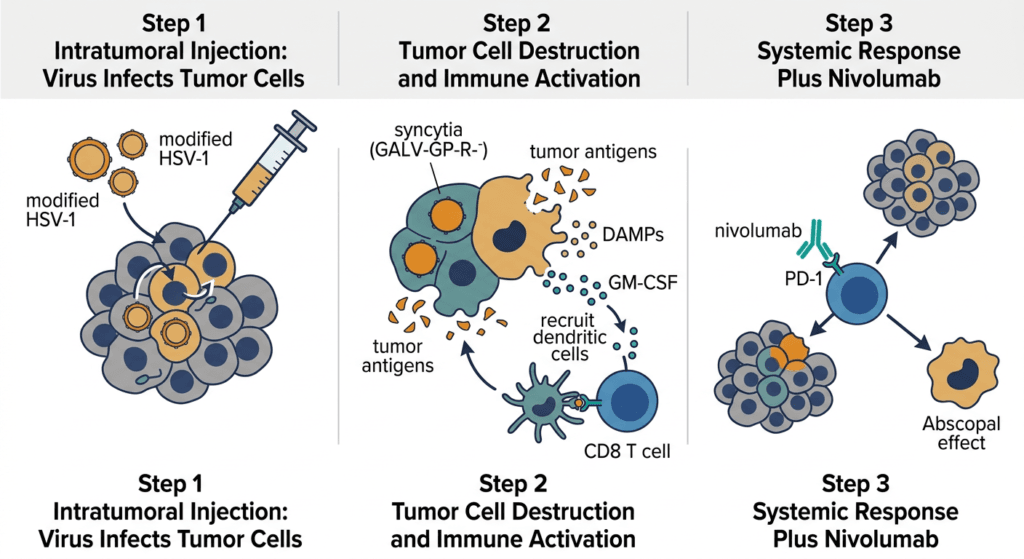
    Tudriqev (vusolimogene oderparepvec-wtpg, Replimune) is a genetically engineered herpes simplex virus injected directly into accessible melanoma tumors. It does not travel to the tumor through the bloodstream. It is placed there by a physician. Once there, it selectively infects and destroys tumor cells, triggers immunogenic cell death, and activates a systemic immune response against tumor antigens that the dying cells release. Combined with nivolumab, it aims to reactivate the anti-PD-1 mechanism in a tumor microenvironment that had previously become resistant to it.

    The approval arrived after a genuinely unusual regulatory journey: two complete response letters spanning 13 months, a third resubmission using the same underlying trial data, a 10 to 3 advisory committee vote supporting the clinical meaningfulness of the evidence, and accelerated approval one week after that vote. The trial design never changed. What changed was how the reviewing agency chose to treat the same evidence.

    The result is a drug with a 24.2% objective response rate and 14.1-month median duration of response in patients who had already failed PD-1 blockade, the primary framework on which modern advanced melanoma care is built, delivering an approval whose clinical significance and whose regulatory sustainability through the confirmatory IGNYTE-3 trial will both become clearer over the next two to three years.


    What Advanced Cutaneous Melanoma Is and Why Post-PD-1 Failure Is So Difficult

    Cutaneous melanoma arises from the melanocytes of the skin and is the most dangerous form of skin cancer. In 2026, approximately 100,640 Americans will be diagnosed with melanoma and approximately 8,290 will die from it. The vast majority of early-stage melanomas are cured with surgical excision. The challenge is metastatic disease.

    The treatment of advanced melanoma has been transformed twice in the past 15 years: first by BRAF/MEK inhibitor combinations (for the approximately 40 to 50% of melanomas with BRAF V600 mutations), and then by immune checkpoint inhibitors targeting PD-1 and CTLA-4. Anti-PD-1 agents (pembrolizumab, nivolumab) produce durable responses in approximately 30 to 40% of patients with advanced melanoma, and the combination of nivolumab plus ipilimumab achieves even higher response rates. For patients who respond, the responses can be remarkably durable, lasting years.

    But a meaningful proportion of patients either do not respond to anti-PD-1 therapy at all (primary resistance) or respond initially and then progress (acquired resistance). The mechanisms of PD-1 resistance in melanoma involve tumor cell-intrinsic immune evasion strategies including downregulation of MHC class I antigen presentation (making tumor cells invisible to CD8 T cells), upregulation of alternative immune checkpoints (LAG-3, TIM-3, TIGIT), and creation of an immunosuppressive tumor microenvironment that physically excludes T cells or neutralizes their function.

    For this population, which represents a substantial unmet need, subsequent options include:

    • Nivolumab plus relatlimab (LAG-3 plus PD-1 dual blockade) in patients not previously treated with this combination
    • BRAF/MEK inhibitors for BRAF-mutant disease not previously treated with targeted therapy
    • Ipilimumab as a CTLA-4 checkpoint alternative
    • Cytotoxic chemotherapy (dacarbazine, carboplatin/paclitaxel) with modest and typically brief responses
    • Clinical trials

    Tudriqev in combination with nivolumab is now the first FDA-approved regimen specifically for patients who have progressed on anti-PD-1 therapy, representing a new mechanistic approach to overcoming PD-1 resistance through intratumoral oncolytic viral therapy.


    What Vusolimogene Oderparepvec Is: The Engineered HSV-1 Mechanism

    Tudriqev is a genetically modified herpes simplex virus type 1 (HSV-1) engineered for selective tumor-killing and immune activation. HSV-1 was chosen as the oncolytic backbone because of its natural tropism for actively dividing cells, its well-characterized biology, and the decades of experience with HSV-1-based oncolytic agents including the predecessor talimogene laherparepvec (Imlygic, approved 2015).

    The four genetic modifications incorporated into vusolimogene oderparepvec are:

    Deletion of ICP34.5 (neurovirulence factor): ICP34.5 is a HSV-1 protein that prevents the antiviral PKR pathway from shutting down viral replication in infected cells. Its deletion makes the virus unable to replicate efficiently in normal, non-dividing cells that have intact antiviral defenses, while allowing replication in tumor cells where antiviral pathways are often defective. This creates the tumor selectivity that distinguishes oncolytic viruses from unmodified pathogens.

    Deletion of ICP47 (antigen presentation inhibitor): ICP47 normally helps HSV-1 evade immune detection by blocking MHC class I antigen presentation, the mechanism by which infected cells display viral (and tumor) antigens to CD8 T cells. Deleting ICP47 allows tumor cells infected by vusolimogene oderparepvec to present both viral antigens and tumor-associated neoantigens to the immune system, enhancing the adaptive immune response against the tumor.

    Insertion of GALV-GP-R minus (fusogenic glycoprotein): This is the most mechanistically distinctive modification in Tudriqev compared to Imlygic. GALV-GP-R minus is a modified gibbon ape leukemia virus envelope glycoprotein that promotes cell-to-cell fusion: infected tumor cells expressing this protein fuse with adjacent tumor cells, creating large multinucleated syncytia that die through a particularly immunogenic form of cell death. This syncytial killing increases the release of tumor antigens and damage-associated molecular patterns (DAMPs) that amplify the immune response, and allows the killing effect to spread beyond directly infected cells.

    Insertion of GM-CSF (granulocyte-macrophage colony-stimulating factor): GM-CSF expressed by the infected tumor cells recruits dendritic cells and macrophages to the tumor site, promoting antigen uptake, processing, and presentation to T cells in the tumor-draining lymph nodes. This bridges the innate response (tumor cell killing) to the adaptive response (systemic T cell activation against tumor neoantigens).

    The combination of these four modifications is intended to produce a multi-mechanism immune activation: direct lysis of injected tumor cells, spreading syncytial killing to adjacent cells, release of tumor antigens in a highly immunogenic context, and recruitment of the immune cells needed to generate a systemic anti-tumor response that can attack both the injected tumor and non-injected metastatic lesions elsewhere in the body.

    The rationale for combining vusolimogene oderparepvec with nivolumab is precisely this systemic response: the oncolytic virus generates the tumor-reactive T cells, and nivolumab removes the PD-1 brake that would otherwise prevent those T cells from remaining active at tumor sites. Together, they aim to create the immune response that PD-1 blockade alone could not sustain in a resistant tumor.

    The IGNYTE Trial: The Pivotal Evidence

    Design

    The IGNYTE trial was a single-arm, open-label, multicenter study enrolling 140 adults with unresectable advanced cutaneous melanoma who had experienced disease progression on a PD-1-blocking antibody-based regimen. Patients received vusolimogene oderparepvec via intratumoral injection every 2 weeks for 8 doses, combined with nivolumab 480 mg intravenously every 4 weeks.

    The administration protocol for Tudriqev: the first injection is given at a lower concentration, and all subsequent 7 injections are given at the higher concentration. Injection volume is determined by the size of the lesion being injected, with larger lesions receiving larger volumes, according to the prescribing information table.

    Efficacy population and results

    The FDA’s efficacy analysis was conducted in the 91-patient subset of the 140 enrolled who had at least one non-injected lesion. This subset is clinically and analytically important: it specifically captures patients in whom a systemic response can be assessed, meaning the virus and immune activation at the injected site produced a response in lesions that never received the virus. This “abscopal” or “bystander” effect is the central clinical claim of oncolytic viral immunotherapy, and restricting the efficacy analysis to patients with measurable non-injected disease allows it to be evaluated rigorously.

    EndpointResult
    Efficacy-evaluable population91 patients with at least one non-injected lesion
    Objective response rate (ORR)24.2%
    Median duration of response (DOR)14.1 months
    Stage IV disease80% of evaluable population
    Prior anti-PD-1 treatment plus ipilimumab13% of evaluable population

    Sources: FDA accelerated approval announcement. FDA.gov. August 6, 2026. Replimune press release. August 6, 2026. BioPharm International IGNYTE analysis. IGNYTE trial.

    A 24.2% response rate in a post-anti-PD-1 population with predominantly Stage IV disease is a meaningful finding in a setting where most available options produce response rates in the 10 to 15% range and typically shorter durations. The 14.1-month median duration of response compares favorably with chemotherapy-based alternatives and is consistent with the immunological basis of the response: T cell-mediated responses, once established, can be more durable than cytotoxic responses.

    The single-arm design, without a concurrent control arm, is the most significant analytical limitation of the IGNYTE trial and is the underlying reason the FDA issued two CRLs before this approval. In a single-arm trial, it is not possible to determine how much of the observed response represents the benefit of the treatment versus the natural selection of patients who remain healthy enough to enroll and complete the trial. The advisory committee’s 10 to 3 vote in favor of clinical meaningfulness reflected a majority view that the ORR and DOR data, in a population with documented prior PD-1 failure, were sufficient to support accelerated approval despite this limitation. The 3 dissenting votes reflected skepticism about whether a single-arm study with a selected efficacy-evaluable subpopulation provides adequate evidence of clinical benefit.


    The Regulatory Path: Two CRLs, Three Submissions, One Approval

    The history of this approval is worth understanding specifically because it illustrates how the FDA’s evaluation of the same underlying evidence can shift, and because it defines the post-approval expectations for Replimune.

    July 2025: CRL 1. The FDA issued the first complete response letter, citing concerns with the submitted trial design and the evidence of effectiveness.

    April 2026: CRL 2. Following resubmission, the FDA issued a second complete response letter raising similar concerns about the evidence base. The trial design had not changed between submissions.

    July 30, 2026: Advisory committee. The FDA convened the Cellular, Tissue, and Gene Therapies Advisory Committee to review the third submission. The committee voted 10 to 3 that the data were evaluable and clinically meaningful.

    August 6, 2026: Accelerated approval. One week after the advisory committee vote, the FDA granted accelerated approval. The IGNYTE trial data, the same data that had generated two CRLs over 13 months, supported this approval.

    The trial design never changed. What changed was how the reviewing agency chose to treat the same evidence. This is an unusual regulatory outcome, and it creates an interpretive question about what threshold the FDA is now applying to single-arm trials in post-checkpoint refractory settings. It also underscores that the accelerated approval framework places significant weight on post-approval confirmation: the drug’s continued marketing authorization is explicitly contingent on IGNYTE-3 demonstrating clinical benefit.


    The Confirmatory Commitment: IGNYTE-3

    IGNYTE-3 (NCT06264180) is a Phase 3, randomized, open-label trial enrolling approximately 400 patients with advanced melanoma who have progressed on anti-PD-1 therapy, randomized 1:1 to vusolimogene oderparepvec plus nivolumab versus physician’s choice (nivolumab plus relatlimab, anti-PD-1 rechallenge, or single-agent chemotherapy). The primary endpoint is overall survival. This trial is the regulatory commitment that must be met to convert accelerated approval to full traditional approval. As with all accelerated approvals, continued marketing authorization may be contingent on this confirmatory data.

    The OS endpoint in IGNYTE-3 will be the definitive clinical answer to the mechanistic promise of Tudriqev. If the survival curves separate meaningfully in favor of the combination, it will establish that the oncolytic viral immunotherapy approach produces real and lasting clinical benefit for patients who have few other options. If they do not, the accelerated approval will face the same withdrawal pressure that has been applied to other drugs where confirmatory trials failed to verify clinical benefit.


    Safety: What the IGNYTE Data and Prescribing Information Cover

    The safety profile of Tudriqev in combination with nivolumab was generally favorable in IGNYTE, with adverse events predominantly mild and consistent with the known profiles of both the oncolytic virus and nivolumab.

    Most common adverse reactions (from the prescribing information and IGNYTE safety data): fatigue, pyrexia (fever), infections, chills, musculoskeletal pain, nausea, and diarrhea. Adverse reactions reported with use of Tudriqev were mild and included fatigue, fever (pyrexia), infections, chills, musculoskeletal pain, nausea, and diarrhea. No treatment-related deaths were reported in IGNYTE.

    The fever, chills, and fatigue pattern is characteristic of oncolytic viral therapy: the immune activation triggered by the intratumoral injection produces a systemic inflammatory response in many patients, typically in the hours to days following each injection. This is expected and generally manageable with supportive care.

    Injection site reactions: Local reactions at the injection site, including pain, erythema, and swelling, are expected with intratumoral administration and were reported in the IGNYTE trial.

    Biosafety considerations: Because Tudriqev is an HSV-1-based therapy, there are specific requirements around handling and potential viral transmission. Healthcare providers administering Tudriqev should wear appropriate protective equipment. Patients should be counseled about the potential for viral shedding at the injection site and surrounding area, and about wound care to minimize exposure risk to immunocompromised household contacts or individuals who have not been previously exposed to HSV-1.

    Nivolumab immune-mediated adverse events: The combination regimen carries all the immune-mediated adverse event risks associated with nivolumab: pneumonitis, colitis, hepatitis, endocrinopathies, nephritis, and other immune-related reactions. Standard pembrolizumab and nivolumab immune-related adverse event monitoring and management protocols apply.


    What This Means for Oncologists and Patients

    For melanoma specialists and oncologists

    Tudriqev fills a specific and poorly served clinical niche: patients with unresectable advanced cutaneous melanoma who have progressed on PD-1 blockade and have accessible lesions for intratumoral injection. For this population, a 24.2% ORR with 14.1-month median DOR represents a meaningful clinical signal in a setting where most available options produce shorter and less durable responses.

    The practical requirement is the accessibility of injectable lesions. Tudriqev is administered directly into cutaneous, subcutaneous, or nodal lesions accessible by direct injection or ultrasound guidance. Patients with disease exclusively in visceral or deep anatomic sites that are not accessible for injection are not candidates for this treatment. The systemic bystander response that Tudriqev is intended to generate against non-injected lesions requires the intratumoral administration of the virus into at least one accessible site.

    The combination with nivolumab is built into the approved regimen. Patients who progress on PD-1 therapy and then receive Tudriqev are continuing nivolumab as part of the approved combination, which represents a continued PD-1 re-challenge alongside the oncolytic viral therapy. This is a recognized and studied approach to PD-1 resistance: providing an immune activation event (oncolytic virus) to sensitize the tumor microenvironment to continued checkpoint inhibition.

    The accelerated approval status and the pending IGNYTE-3 OS data are relevant context for shared decision-making. Patients starting Tudriqev under accelerated approval should understand that continued marketing authorization depends on confirmatory survival data, and that the clinical benefit demonstrated in IGNYTE, while promising, is based on single-arm ORR and DOR data.

    For patients with advanced melanoma

    If you have unresectable advanced cutaneous melanoma that has progressed on pembrolizumab or nivolumab and you have accessible tumors that can be injected, Tudriqev in combination with nivolumab is now an FDA-approved option. It is administered at qualified treatment centers with experience in intratumoral injection and oncolytic viral therapy.

    Replimune has launched a patient support program called ReplimuneConnect Plus, covering access, reimbursement navigation, and financial assistance for eligible patients. Information is available through the Tudriqev website.

    For patients interested in clinical trial participation as an alternative or in addition to approved therapy, ClinicalTrials.gov is the most current source for open enrollment studies. Searching “melanoma nivolumab oncolytic” or “IGNYTE-3” will return active trial listings.

    For related HED coverage on melanoma and immunotherapy, see our post on Keytruda (pembrolizumab) and Keytruda Qlex receiving their new first-line TNBC combination indications with Trodelvy, which covers the checkpoint inhibitor mechanism in detail, and our post on Jideytro (zidesamtinib) for ROS1-positive NSCLC for context on other targeted oncology approvals in August 2026.

    The Melanoma Research Foundation (melanoma.org; 1-800-673-1290) and the Melanoma Research Alliance (curemelanoma.org) maintain current patient resources on treatment options, clinical trials, and financial assistance for patients with advanced melanoma.


    Sources

    FDA accelerated approval announcement: FDA grants accelerated approval to vusolimogene oderparepvec-wtpg in combination with nivolumab for melanoma. FDA.gov. August 6, 2026.

    Replimune approval press release: Replimune Announces FDA Accelerated Approval of TUDRIQEV in Combination with Nivolumab for Unresectable Advanced Cutaneous Melanoma After Progression on an anti-PD-1 Based Regimen. ir.replimune.com. August 6, 2026.

    FDA/GlobeNewswire approval announcement: FDA Approves New Engineered Viral Immunotherapy for Patients with Treatment-Resistant Advanced Melanoma. GlobeNewswire. August 6, 2026.

    Drugs.com approval news: FDA Grants Accelerated Approval to Tudriqev in Combination with Nivolumab for Unresectable Advanced Cutaneous Melanoma. drugs.com. August 6, 2026.

    Pharmacy Times (two CRL history, advisory committee vote, complete molecular description): After 2 CRLs, FDA Approves Vusolimogene Oderparepvec With Nivolumab for Advanced Melanoma. pharmacytimes.com. August 2026.

    BioPharm International (ORR 24.2%, DOR 14.1 months, 91-patient efficacy population, IGNYTE-3 description): FDA Grants Accelerated Approval to Replimune’s Tudriqev Plus Nivolumab for Advanced Melanoma. biopharminternational.com. August 2026.

    Healio (two prior rejections context, regulatory timeline): FDA OKs accelerated approval to twice-rejected Tudriqev with Opdivo for advanced melanoma. healio.com. August 2026.

    Morning Glory Sciences analytical deep-dive (regulatory trajectory analysis, advisory committee vote, IGNYTE-3 OS primary): Oncology Drug Approval News Flash: FDA Approves Vusolimogene Oderparepvec Plus Nivolumab for Anti-PD-1-Refractory Advanced Melanoma. morningglorysciences.com. August 2026.

    PharmTech (Breakthrough Therapy Designation, advisory committee meeting, safety profile): The FDA Gives Accelerated Approval to Melanoma Treatment. pharmtech.com. August 2026.

    VJ Neurology (second oncolytic virus approval since Imlygic 2015, patient support program): FDA approves vusolimogene oderparepvec for the treatment of advanced melanoma. vjneurology.com. August 2026.

    IGNYTE-3 trial registration: NCT06264180. ClinicalTrials.gov.

    Cutaneous melanoma overview: Melanoma, Cutaneous. StatPearls. NCBI.

    Tudriqev prescribing information: TUDRIQEV (vusolimogene oderparepvec-wtpg) Prescribing Information. Replimune Group Inc. 2026.

    Tudriqev approval history: Tudriqev FDA Approval History. drugs.com.

    Patient resources: Melanoma Research Foundation: 1-800-673-1290 | Melanoma Research Alliance | AIM at Melanoma Foundation | ReplimuneConnect Plus patient support | ClinicalTrials.gov: search melanoma nivolumab oncolytic

    Disclaimer: Health Evidence Digest provides general information about FDA approvals and health research for educational purposes. This content is not a substitute for professional medical advice. Tudriqev (vusolimogene oderparepvec-wtpg) received accelerated approval based on objective response rate and duration of response; continued approval may be contingent on verification of clinical benefit in the confirmatory IGNYTE-3 Phase 3 trial. Tudriqev requires intratumoral injection by a qualified healthcare provider at a facility equipped for oncolytic viral therapy administration. All treatment decisions for advanced cutaneous melanoma should be made in close collaboration with a board-certified medical oncologist or dermatologic oncologist experienced in the management of advanced melanoma and immunotherapy.
  • Orzeyful (Oveporexton) Receives FDA Approval as the First and Only OX2R Agonist for Narcolepsy Type 1, Targeting the Orexin Deficiency That Drives the Disease Rather Than Its Individual Symptoms

    Orzeyful (Oveporexton) Receives FDA Approval as the First and Only OX2R Agonist for Narcolepsy Type 1, Targeting the Orexin Deficiency That Drives the Disease Rather Than Its Individual Symptoms

    The essentials: On August 5, 2026, the FDA approved Orzeyful (oveporexton, Takeda) for the treatment of narcolepsy type 1 (NT1, narcolepsy with cataplexy) in adults. Orzeyful is the first and only orexin receptor 2 (OX2R)-selective agonist approved for any indication and the first therapy designed to directly restore the orexin signaling that is lost in NT1, rather than treating individual symptoms through other neurotransmitter systems. What narcolepsy type 1 is: a rare, lifelong autoimmune neurological disorder caused by the selective destruction of hypothalamic neurons that produce orexin (also called hypocretin), a neuropeptide that stabilizes wakefulness and suppresses REM sleep. NT1 affects approximately 1 in 2,000 people in the United States. The core symptoms are excessive daytime sleepiness and cataplexy (sudden muscle weakness triggered by emotion), along with sleep paralysis, hypnagogic and hypnopompic hallucinations, and disrupted nocturnal sleep. All five are direct consequences of orexin deficiency. What oveporexton does: it selectively binds to and activates OX2R, the receptor normally activated by orexin in the hypothalamus and throughout wake-promoting neural circuits. By restoring OX2R signaling, oveporexton mimics the wake-stabilizing and REM-suppressing effects of the orexin the patient’s own neurons no longer produce. The clinical basis: two Phase 3 randomized, double-blind, placebo-controlled 12-week trials in 273 adults with NT1. FirstLight (NCT06470828, n=168; 19 countries): high dose (2 mg twice daily), low dose (1 mg twice daily), and placebo. RadiantLight (NCT06505031, n=105): high dose (2 mg twice daily) and placebo. Primary endpoint (both trials): change from baseline in mean sleep latency on the Maintenance of Wakefulness Test (MWT) at week 12. Both trials met the primary endpoint: statistically significant improvement in MWT versus placebo at 2 mg twice daily (p less than 0.001). Most patients treated with 2 mg twice daily achieved MWT wakefulness levels within the normal range (at or above 20 minutes). Nearly 85% achieved Epworth Sleepiness Scale (ESS) scores at or below 10 (within the healthy reference range). Weekly cataplexy rate reduction: incidence rate ratio 0.25 (95% CI 0.15 to 0.42; p less than 0.001) in RadiantLight. ESS improvement LS mean minus 9.53 (95% CI minus 11.10 to minus 7.97; p less than 0.001) in RadiantLight. NSS-CT (Narcolepsy Severity Scale for Clinical Trials) improvement LS mean minus 18.11 (p less than 0.001). SF-36 MCS improvement 9.32 (p less than 0.001); PCS 5.01 (p less than 0.001). Phase 2b NEJM publication (NCT05687903): dose-dependent MWT gains of 12.5 to 25.4 minutes versus minus 1.2 minutes for placebo. Regulatory designations: Priority Review. DEA scheduling: pending (required before commercial launch; Takeda expects to make Orzeyful available via specialty pharmacy following completion of DEA scheduling). Most common adverse reactions (greater than 15% in trials): insomnia (57.1% in RadiantLight 2 mg arm), urinary frequency (61.4%), urinary urgency (14.3%), and hypersalivation. Key drug interaction contraindication: strong CYP3A inhibitors. Dosing: 2 mg orally twice daily, taken at least 3 hours apart. Pediatric: efficacy not established in patients under 16.

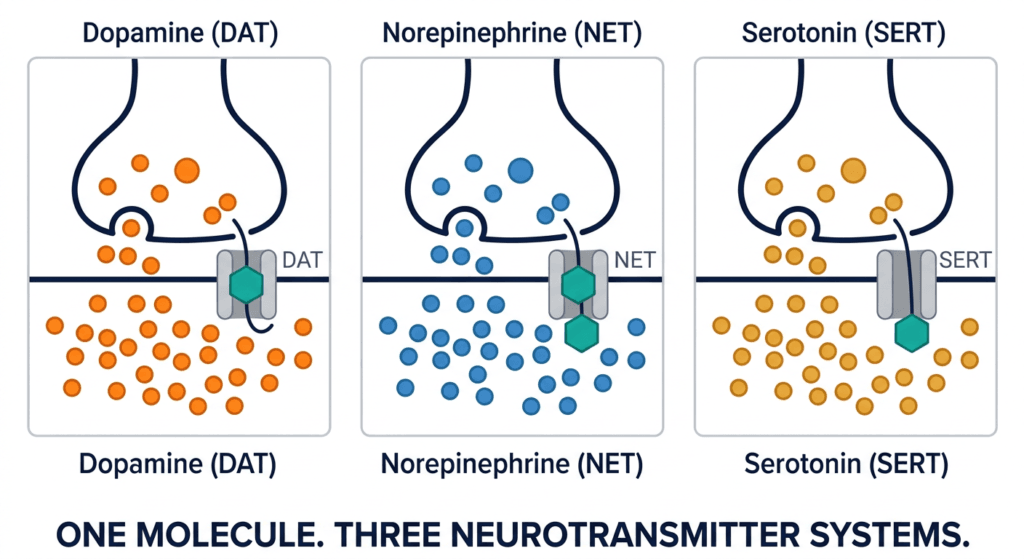
    Every existing treatment for narcolepsy type 1 is a workaround. Stimulants increase dopamine and norepinephrine to drive wakefulness. Sodium oxybate consolidates nocturnal sleep and suppresses cataplexy through GABA mechanisms. Pitolisant blocks histamine H3 autoreceptors to increase histamine release. Each addresses one or more of the downstream consequences of the disease, and each helps meaningfully, but none of them replaces what NT1 has actually destroyed: the orexin-producing neurons of the hypothalamus, and the wake-stabilizing signal those neurons maintained across every hour of every day.

    The mechanism behind Orzeyful is the first attempt to fill that gap directly. Rather than routing around the missing orexin signal through other neurotransmitter systems, oveporexton activates the OX2R receptor that orexin normally activates, in the same neural circuits, with the same downstream effects on wakefulness and REM suppression. It does not restore the neurons. It restores the signal those neurons were providing.

    The Phase 3 FirstLight and RadiantLight trials enrolled 273 adults with NT1 across 19 countries and demonstrated that oveporexton produces clinically meaningful improvements not just in excessive daytime sleepiness and cataplexy, but across the full symptom range of the disease: hallucinations, sleep paralysis, disrupted nocturnal sleep, cognition, and quality of life. Most patients treated with the approved 2 mg twice-daily dose achieved wakefulness levels within the normal range on the Maintenance of Wakefulness Test. Nearly 85% achieved ESS scores in the healthy reference range.

    The drug awaits DEA controlled substance scheduling before it can be dispensed commercially. That scheduling decision, expected within months of the August 5 FDA approval, will determine how it is prescribed and accessed in clinical practice.


    What Narcolepsy Type 1 Is: The Immunological Destruction of Wake Circuitry

    Narcolepsy type 1 is a rare, lifelong neurological disorder affecting approximately 1 in 2,000 people in the United States, with an estimated 200,000 affected Americans. It is classified as a hypersomnia disorder, but it is more accurately a disorder of wake-sleep state instability: the circuitry that keeps wakefulness stable during the day and prevents REM sleep from intruding at inappropriate times is selectively destroyed.

    The disease is caused by the autoimmune destruction of orexin-producing neurons in the lateral hypothalamus, a discrete population of approximately 70,000 neurons in the human brain whose axons project throughout the CNS to reinforce wakefulness and maintain REM sleep suppression during the day. Patients with NT1 lose 85 to 95% of these neurons, resulting in cerebrospinal fluid (CSF) orexin levels at or below 110 pg/mL, the diagnostic threshold.

    The trigger for this autoimmune attack is not fully understood but involves genetic susceptibility (the HLA-DQB1*06:02 allele is present in more than 90% of NT1 patients), environmental exposures, and possible molecular mimicry between certain influenza strains or vaccines and orexin neurons. The neuronal loss is permanent: orexin levels in NT1 do not recover over time.

    The five symptoms and their shared biological origin

    All five major symptoms of NT1 arise directly from orexin deficiency and can be understood as consequences of two core physiological failures:

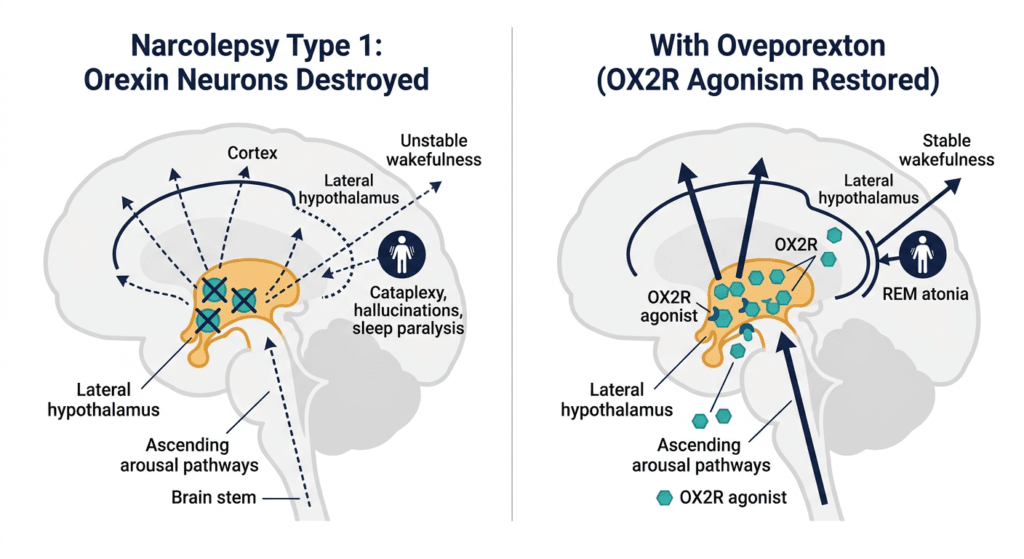
    Excessive daytime sleepiness (EDS): Without orexin reinforcing the ascending arousal pathways from the brainstem to the cortex, wakefulness becomes unstable. Patients experience an overwhelming, persistent urge to sleep throughout the day, sleep attacks that cannot be resisted, and cognitive fog that accompanies even awake periods. EDS is present in 100% of NT1 patients and is typically the most disabling symptom.

    Cataplexy: The most pathognomonic symptom of NT1, cataplexy involves sudden, brief episodes of bilateral muscle weakness triggered by strong positive emotions, most commonly laughter, excitement, or surprise. During a cataplectic attack, which typically lasts seconds to a few minutes, the patient remains conscious but cannot move, due to the same atonic state that normally prevents acting out dreams during REM sleep. Cataplexy occurs because, without orexin suppressing the REM atonia circuitry, strong emotional signals can accidentally trigger the REM atonia mechanism during wakefulness.

    Hypnagogic and hypnopompic hallucinations: Dream-like hallucinations occurring at sleep onset (hypnagogic) or awakening (hypnopompic), caused by REM dreaming intruding into transitional states between sleep and wakefulness.

    Sleep paralysis: Brief inability to move or speak at sleep onset or awakening, again caused by REM atonia crossing into the wake state.

    Disrupted nocturnal sleep: Despite overwhelming daytime sleepiness, most NT1 patients also have fragmented nighttime sleep, with frequent awakenings, vivid dreams, and difficulty maintaining sleep stages. Orexin normally stabilizes sleep architecture in addition to promoting wakefulness.

    The first-line treatments that have existed for NT1, stimulants for EDS and sodium oxybate for cataplexy and nocturnal sleep, typically require separate medications to address the different symptom domains and do not correct the underlying orexin deficiency. Current pharmacological approaches for NT1 primarily focus on symptom management, including improving wakefulness and reducing cataplexy. However, these treatments do not directly address the underlying pathophysiology of orexin deficiency.


    The Orexin System and Why OX2R Agonism Is the Right Target

    Orexin (also called hypocretin) exists as two neuropeptides, orexin A and orexin B, both cleaved from the precursor prepro-orexin. They bind to two G-protein-coupled receptors: OX1R (orexin receptor 1) and OX2R (orexin receptor 2). Orexin A binds both receptors with approximately equal affinity. Orexin B binds preferentially to OX2R.

    The two receptors have distinct but overlapping distributions and functions. OX1R is more prominent in the locus coeruleus (norepinephrine pathways) and dorsal raphe. OX2R is more prominent in the histaminergic tuberomammillary nucleus, the lateral hypothalamus itself, and the pontine reticular formation, the regions most directly responsible for the integrated wake-stabilization function of orexin. OX2R signaling is considered the dominant contributor to orexin’s wake-promoting and REM-suppression effects.

    Oveporexton is selective for OX2R over OX1R, a design choice that concentrates its pharmacological activity on the receptor most responsible for the physiological functions lost in NT1, while reducing activity at OX1R, which is more associated with sympathetic arousal and stress responses that could contribute to cardiovascular or anxiety-related adverse effects.

    The biological effect of OX2R agonism with oveporexton: it activates the wake-stabilizing neural circuits that orexin normally maintains, reinforcing the ascending arousal pathways from the brainstem, suppressing inappropriate REM intrusion, and stabilizing the boundary between wakefulness and sleep. For NT1 patients, this is pharmacologically equivalent to restoring a portion of the orexin signal their own neurons no longer produce.

    This represents a conceptual shift from the existing treatment paradigm. Existing NT1 treatments work despite the absence of orexin; oveporexton works because it mimics orexin’s action at the relevant receptor.


    The Phase 3 Trials: FirstLight and RadiantLight

    Design

    FirstLight (NCT06470828) enrolled 168 adults with NT1 (diagnosis per ICSD-3 or ICSD-3-TR, supported by polysomnography, multiple sleep latency testing, or CSF orexin at or below 110 pg/mL; ESS at or above 11; at or above 4 partial or complete cataplexy episodes per week) randomized to one of three dosing arms: oveporexton 2 mg twice daily (high dose), oveporexton 1 mg twice daily (low dose), or placebo. RadiantLight (NCT06505031) enrolled 105 adults with the same eligibility criteria randomized 2:1 to oveporexton 2 mg twice daily or placebo. Both were double-blind, placebo-controlled, 12-week trials conducted across 19 countries, with enrollment completed within 6 months.

    The primary endpoint in both trials was change from baseline in mean sleep latency on the Maintenance of Wakefulness Test (MWT) at week 12. The MWT measures how long a person can stay awake in a quiet, dimly lit room during a series of 40-minute test periods; a longer latency indicates better ability to maintain wakefulness. Normal MWT sleep latency is generally considered at or above 20 minutes; NT1 patients typically have severely reduced MWT latencies at baseline.

    Key secondary endpoints included change from baseline in ESS total score, weekly cataplexy rate (WCR), Narcolepsy Severity Scale for Clinical Trials (NSS-CT) total score, and SF-36 quality-of-life measures.

    Results at week 12

    Both trials met their primary endpoints with statistically significant improvement in MWT versus placebo at 2 mg twice daily (p less than 0.001 in both). The clinical magnitude of the benefit is captured across both the primary and secondary endpoints:

    EndpointOveporexton 2 mg (RadiantLight)PlaceboResult
    MWT mean sleep latency (primary)Statistically significant improvementReferencep less than 0.001; most patients reached normal range (at or above 20 min)
    ESS change from baseline (key secondary)LS mean minus 9.53 (95% CI minus 11.10 to minus 7.97)Referencep less than 0.001
    Weekly cataplexy rate (key secondary)Incidence rate ratio 0.25 (95% CI 0.15 to 0.42)Referencep less than 0.001; 75% reduction
    NSS-CT total score (key secondary)LS mean minus 18.11 (95% CI minus 21.25 to minus 14.96)Referencep less than 0.001
    SF-36 Mental Component SummaryLS mean plus 9.32Referencep less than 0.001
    SF-36 Physical Component SummaryLS mean plus 5.01Referencep less than 0.001
    Patients achieving ESS at or below 10 (healthy range)Approximately 85%—First-class drug to bring most patients into healthy reference range
    Improvements in hallucinations and sleep paralysisSignificantReferenceBroad multidimensional disease control

    Sources: RadiantLight ATS 2026 abstract. AJRCCM. 2026;212(Supplement 1). NeurologyLive Phase 3 data summary. FirstLight NCT06470828. RadiantLight NCT06505031.

    The headline finding from the perspective of clinical practice: the 75% reduction in weekly cataplexy rate (incidence rate ratio 0.25) and the near-normalization of MWT sleep latency together demonstrate that oveporexton addresses both of NT1’s defining symptom domains from a single mechanistic intervention, something that has not been achievable from any prior NT1 therapy without combining multiple medications.

    The 85% of patients reaching ESS at or below 10 by week 12 is striking because it means the majority of trial participants, starting from ESS scores at or above 11 (a threshold indicating pathological sleepiness), achieved subjective sleepiness levels within the normal healthy reference range after 12 weeks of treatment. The NSS-CT and SF-36 data confirm that this symptom improvement translated into meaningful improvements in narcolepsy-specific functioning and health-related quality of life.

    Phase 2b NEJM data: the dose-finding foundation

    The Phase 3 program was preceded by Phase 2b (NCT05687903), published in the New England Journal of Medicine, which enrolled 112 adults with NT1 randomized to one of four dosing arms or placebo for 8 weeks. The trial showed dose-dependent improvement across patients, with mean MWT changes ranging from 12.5 to 25.4 minutes across active arms compared with minus 1.2 minutes for placebo (adjusted p at or below 0.001 for all comparisons). This dose-dependent pharmacodynamic gradient confirmed the mechanistic connection between OX2R agonism and wakefulness promotion and guided the 2 mg twice-daily dose selection for the pivotal Phase 3 program.


    Safety: What Prescribers and Patients Need to Know

    The safety profile of oveporexton across the FirstLight and RadiantLight trials reflects the pharmacological consequences of OX2R agonism, with the most distinctive adverse events being those that are directly mechanistically related to activation of wake-promoting and autonomic neural circuits.

    Most common adverse events

    Adverse events were most commonly insomnia, urinary frequency/urgency, and hypersalivation. Rates from RadiantLight:

    Adverse eventOveporexton 2 mg (n=70)Placebo (n=35)
    Any TEAE85.7% (60 patients)42.9% (15 patients)
    Urinary frequency61.4%Not reported at this rate
    Insomnia57.1%—
    Urinary urgency14.3%—
    Serious TEAEsNoneNone

    The high rates of urinary frequency (61.4%) and insomnia (57.1%) with oveporexton 2 mg are pharmacologically expected. OX2R activation has effects on smooth muscle and autonomic nervous system function that explain the urinary symptoms. Insomnia reflects the wakepromoting mechanism extending into the night: OX2R agonism that keeps patients awake during the day may maintain alertness at bedtime, particularly if the last dose is taken too close to sleep time. The prescribing information specifies that doses should be taken at least 3 hours apart, with the second dose taken several hours before bedtime.

    Hypersalivation (excessive salivation) is a less mechanistically obvious but consistently reported adverse event with OX2R agonists and is thought to reflect autonomic OX2R expression in salivary gland-related neural circuits.

    No serious TEAEs occurred in either trial. The adverse events were predominantly mild and related to the mechanism, not to systemic toxicity.

    Key safety considerations

    CYP3A inhibitors (contraindication): Oveporexton is metabolized primarily through CYP3A4. Concomitant strong CYP3A inhibitors (ketoconazole, itraconazole, clarithromycin, ritonavir, and others) substantially increase oveporexton plasma exposure, which would amplify both efficacy and adverse effects. Strong CYP3A inhibitors are contraindicated with Orzeyful. Patients on these agents should not receive oveporexton without discussion of alternative therapies.

    CYP3A inducers: Strong CYP3A inducers (rifampin, carbamazepine, phenytoin, St. John’s wort) reduce oveporexton exposure and may reduce efficacy. The clinical significance should be evaluated for each patient.

    Pediatric use: Efficacy has not been established in patients under 16 years of age, and the approval covers adults only. Narcolepsy type 1 commonly begins in adolescence and childhood, and the unmet need in pediatric patients is significant; this remains an area for ongoing investigation.

    DEA scheduling: Orzeyful is a CNS-active drug and requires DEA controlled substance scheduling before it can be dispensed commercially. The DEA scheduling process following FDA approval typically takes several weeks to months. Takeda expects to make Orzeyful available via specialty pharmacy following completion of the DEA scheduling process. How the DEA classifies it, and whether it receives a lower schedule than traditional stimulants given its distinct mechanism and adverse event profile, will affect prescribing logistics.


    How Orzeyful Fits in the Current NT1 Treatment Landscape

    NT1 has several approved treatments, none of which previously addressed the underlying orexin deficiency:

    DrugMechanismAddressesRouteSchedule
    Amphetamines, methylphenidateDAT/NET reuptake inhibition and releaseEDS onlyOralSchedule II
    Sodium oxybate (Xyrem, Lumryz)GABA-B agonismCataplexy and nocturnal sleep (and EDS with Lumryz)Oral (taken at night)Schedule III
    Pitolisant (Wakix)H3 receptor antagonist/inverse agonistEDS and cataplexyOralNon-scheduled
    Solriamfetol (Sunosi)DAT/NET reuptake inhibitionEDSOralSchedule IV
    Modafinil/armodafinilUnknown (dopaminergic and histaminergic)EDSOralSchedule IV
    Orzeyful (oveporexton)OX2R selective agonistEDS, cataplexy, hallucinations, sleep paralysis, disrupted nocturnal sleep — full symptom rangeOralPending DEA scheduling

    The most important clinical distinction in the table is the last column under “Addresses”: Orzeyful is the first NT1 therapy with clinical evidence supporting improvement across the full range of NT1 symptoms from a single mechanism, rather than targeting individual symptom domains. Whether this translates into clinical superiority over well-optimized combinations of existing agents in individual patients will emerge from clinical experience and post-marketing studies. But as a first approved disease-mechanism-targeting therapy, it changes the conceptual framework of NT1 treatment.

    As Dr. Emmanuel Mignot of Stanford University, principal investigator for FirstLight, described: oveporexton brings us a major step closer to having the first orexin therapy that addresses the underlying cause of narcolepsy type 1.


    What This Means for Sleep Medicine Clinicians and Patients

    For sleep medicine clinicians and neurologists

    Orzeyful adds a mechanistically unique option to NT1 management that was not previously available. Its OX2R-selective mechanism is distinct from stimulants, sodium oxybate, pitolisant, and all other existing agents. The clinical profile, strong improvement in both wakefulness and cataplexy simultaneously, with additional benefits across hallucinations, sleep paralysis, and nocturnal sleep, addresses a longstanding limitation of NT1 pharmacotherapy that required separate agents for separate symptom domains.

    The practical challenges to navigate before prescribing: the DEA scheduling outcome and the specialty pharmacy distribution model will shape the workflow. The CYP3A inhibitor contraindication will require medication review in what is often a polypharmacy patient population. The high rates of insomnia and urinary frequency need to be proactively discussed with patients as likely early adverse effects related to the mechanism, not unexpected toxicity, and dosing timing guidance (at least 3 hours between doses, second dose well before bedtime) should be emphasized.

    The 85% of trial patients reaching ESS at or below 10 by week 12 is an efficacy benchmark that exceeds what most existing NT1 therapies produce as monotherapy in real-world practice. For patients who have not achieved adequate sleepiness control on existing regimens, or whose cataplexy has remained poorly controlled alongside EDS treatment, Orzeyful represents a genuinely new option.

    For patients with NT1

    If you have narcolepsy type 1 and your current treatment leaves residual sleepiness, cataplexy, hallucinations, sleep paralysis, or disrupted nighttime sleep, Orzeyful may be worth discussing with your sleep specialist or neurologist after it becomes commercially available following DEA scheduling.

    Orzeyful will be available through specialty pharmacy rather than standard retail pharmacy channels. Your clinician will need to submit a prescription through the specialty pharmacy network once the DEA scheduling and commercial launch are complete. Takeda has announced that patients and providers can sign up for availability updates through the Orzeyful website.

    The Narcolepsy Network (narcolepsynetwork.org; 1-888-292-6522) and the Wake Up Narcolepsy patient advocacy organization maintain current information on NT1 treatment options, clinical trials, and peer community support.


    Sources

    FDA approval announcement: FDA approves oveporexton for narcolepsy type 1. FDA.gov. August 5, 2026.

    Takeda FDA approval press release: U.S. FDA Approves Takeda’s ORZEYFUL (oveporexton), the First and Only Medicine to Treat the Underlying Cause of Narcolepsy Type 1. BusinessWire. August 5, 2026.

    Takeda newsroom announcement: FDA Approves ORZEYFUL for Adults With Narcolepsy Type 1. takeda.com. August 5, 2026.

    Drugs.com approval news: FDA Approves Orzeyful (oveporexton) to Treat the Underlying Cause of Narcolepsy Type 1. drugs.com. August 5, 2026.

    NeurologyLive (full Phase 3 design, phase 2b NEJM data, mechanism, DEA scheduling context): FDA Approves Orexin Agonist Oveporexton for Narcolepsy Type 1. neurologylive.com. August 2026.

    HCPLive (full endpoint data, 85% ESS normalization, broad symptom improvement): FDA Approves Oveporexton (Orzeyful) for Narcolepsy Type 1. hcplive.com. August 2026.

    Pharmacy Times (CYP3A contraindication, pediatric limitation, specialty pharmacy distribution): FDA Approves Oveporexton for Narcolepsy Type 1. pharmacytimes.com. August 2026.

    PharmExec (OX2R selectivity rationale, commercial context): FDA Approves Orzeyful for Narcolepsy Type 1 in Adults. pharmexec.com. August 2026.

    Drug Topics (specialty pharmacy distribution, first disease-mechanism-targeting drug): FDA Approves Orzeyful, First Drug Targeting Underlying Cause of Narcolepsy. drugtopics.com. August 2026.

    VJ Neurology (full multidimensional symptom improvement including hallucinations and sleep paralysis): FDA approves oveporexton for the treatment of narcolepsy type 1 in adults. vjneurology.com. August 2026.

    NeurologyLive Phase 3 topline results (July 2025): Orexin-Targeting Agent TAK-861 Meets All End Points in Phase 3 FirstLight and RadiantLight Studies. neurologylive.com.

    Takeda Phase 3 positive results press release: Takeda Announces Positive Results from Two Pivotal Phase 3 Studies of Oveporexton (TAK-861) in Narcolepsy Type 1. takeda.com. July 14, 2025.

    Takeda World Sleep 2025 data presentation: Takeda Presents Orexin Data from Landmark Oveporexton Phase 3 Program at World Sleep 2025. takeda.com. September 8, 2025.

    RadiantLight ATS 2026 abstract (exact ESS, WCR, NSS-CT, SF-36 data): C21-01 Efficacy and Safety of Oveporexton (TAK-861) for NT1: Results From the Phase 3 RadiantLight Study. AJRCCM. 2026;212(Supplement 1).

    Neurology Advisor (trial enrollment criteria, 85% ESS data): FDA Grants Priority Review to Oveporexton for Narcolepsy Type 1. neurologyadvisor.com.

    Phase 2b trial registration: NCT05687903. ClinicalTrials.gov.

    FirstLight trial registration: NCT06470828. ClinicalTrials.gov.

    RadiantLight trial registration: NCT06505031. ClinicalTrials.gov.

    Narcolepsy type 1 overview: Narcolepsy. StatPearls. NCBI.

    Orzeyful prescribing information: ORZEYFUL (oveporexton) Prescribing Information. Takeda Pharmaceuticals America Inc. 2026.

    Orzeyful approval history: Orzeyful FDA Approval History. drugs.com.

    Patient resources: Narcolepsy Network: 1-888-292-6522 | Wake Up Narcolepsy | Project Sleep | Takeda Orzeyful patient sign-up for availability updates | American Academy of Sleep Medicine: sleepeducation.org

    Disclaimer: Health Evidence Digest provides general information about FDA approvals and health research for educational purposes. This content is not a substitute for professional medical advice. Orzeyful (oveporexton) is not yet commercially available pending DEA controlled substance scheduling, which is expected to complete within months of the August 5, 2026 FDA approval. Strong CYP3A inhibitors are contraindicated with oveporexton. The efficacy of Orzeyful in patients under 16 years of age has not been established. Treatment decisions for narcolepsy type 1 should be made in close collaboration with a board-certified sleep medicine physician or neurologist experienced in the diagnosis and management of central hypersomnia disorders.
  • Pluvicto Receives FDA Approval for Metastatic Hormone-Sensitive Prostate Cancer, Adding a Third Indication for the Only PSMA-Targeted Radioligand Therapy Approved Across Metastatic Prostate Cancer Disease Stages

    Pluvicto Receives FDA Approval for Metastatic Hormone-Sensitive Prostate Cancer, Adding a Third Indication for the Only PSMA-Targeted Radioligand Therapy Approved Across Metastatic Prostate Cancer Disease Stages

    The essentials: On July 31, 2026, the FDA approved Pluvicto (lutetium Lu 177 vipivotide tetraxetan, Novartis) in combination with androgen receptor pathway inhibitor (ARPI) therapy for adults with prostate-specific membrane antigen (PSMA)-positive metastatic androgen pathway modulation-naïve or -sensitive (mAPMN/S) prostate cancer, previously known as metastatic hormone-sensitive prostate cancer (mHSPC). This is the first approval of a radioligand therapy (RLT) in the hormone-sensitive metastatic setting. It is earlier in the disease course than Pluvicto’s two existing indications, which cover PSMA-positive metastatic castration-resistant prostate cancer (mCRPC). PSMA-positive selection required: Patients must be selected for Pluvicto using Locametz (gallium Ga 68 gozetotide) or another approved PSMA PET product confirming PSMA expression. The clinical basis: Phase 3 PSMAddition (NCT04720157), 1,144 patients with PSMA-positive mHSPC, randomized 1:1 to Pluvicto 7.4 GBq (200 mCi) intravenously every 6 weeks for 6 cycles plus ADT plus ARPI versus ADT plus ARPI alone. Presented at ESMO 2025 Presidential Symposium. Primary endpoint (rPFS by BIRC at interim analysis, data cutoff January 13, 2025, median follow-up 23.6 months): HR 0.72 (95% CI 0.58 to 0.90); p=0.002. Median rPFS: not reached in either arm. Overall survival (key secondary): HR 0.84 (95% CI 0.63 to 1.13); p=0.125 — trend toward benefit; not statistically significant. ORR: 85.3% (Pluvicto) versus 80.8% (standard of care). Complete response: 57.1% versus 42.3%. PSA below 0.2 ng/mL at 48 weeks: 87.4% versus 74.9%. Time to mCRPC: HR 0.70 (95% CI 0.58 to 0.84). Time to PSA progression: HR 0.42 (95% CI 0.30 to 0.59). Grade 3 or higher adverse events: 50.7% (Pluvicto arm) versus 43.0% (control). Dry mouth: 41% grade 1 and 5% grade 2 with Pluvicto versus 3.8% total in control. Quality of life: no meaningful difference in FACT-P or EQ-5D between arms. No treatment-related deaths. Important context: an expert at ESMO 2025 raised public concerns about patient selection, overtreatment, and toxicity, noting that no OS improvement was demonstrated and that QoL was numerically lower in the Pluvicto arm. This debate is included in this post because patients and clinicians deserve to know it exists when making treatment decisions. Pluvicto is now the only PSMA-targeted agent approved across both hormone-sensitive and castration-resistant metastatic prostate cancer.

    Prostate cancer does not kill most men who have it. But for the approximately 35,000 men who die from it annually in the United States, the disease follows a predictable and devastating trajectory: local disease, rising PSA, eventual metastasis, response to androgen deprivation, progression to castration resistance, and death. Every line of therapy that extends the disease-sensitive phase adds time before that trajectory reaches its endpoint.

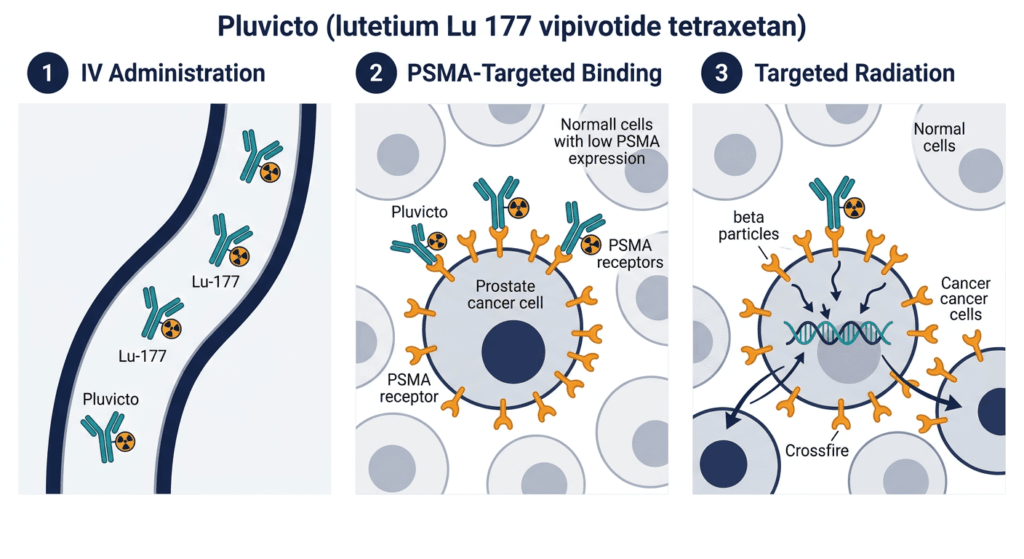
    Pluvicto (lutetium Lu 177 vipivotide tetraxetan) is a radioligand therapy: a molecule designed to seek out prostate cancer cells wherever they have spread in the body, bind to a protein on their surface called PSMA, and deliver a targeted dose of beta-particle radiation that kills the cell and its neighbors. When the FDA approved it in March 2022 for metastatic castration-resistant prostate cancer, the VISION trial data showed it reduced the risk of death by 38% and the risk of radiographic progression by 60% in a population that had exhausted nearly all other options.

    The July 31, 2026 approval moves Pluvicto upstream into an earlier phase of metastatic disease: hormone-sensitive prostate cancer, where androgen deprivation therapy and ARPIs still have meaningful activity and where the goal is to delay as long as possible the progression to castration resistance and the sharply worse prognosis that follows.

    The PSMAddition trial that supported this approval met its primary endpoint. The 28% reduction in risk of radiographic progression is statistically significant and consistent across patient subgroups. Response rates and depth of PSA suppression were meaningfully better with the addition of Pluvicto. And the safety profile was consistent with prior Pluvicto experience.

    But there is a clinical debate attached to this approval that a responsible post cannot omit. Overall survival, the endpoint that ultimately matters most, showed a trend toward benefit that did not reach statistical significance (HR 0.84; p=0.125). Grade 3 or higher adverse events were 50.7% with Pluvicto versus 43.0% with standard of care. An expert commentator at the ESMO 2025 Presidential Symposium where the PSMAddition data were presented publicly stated that he would not recommend widespread use of lutetium PSMA in mHSPC given the lack of OS benefit and quality-of-life concerns.

    This post covers both sides of that conversation accurately.


    What Metastatic Hormone-Sensitive Prostate Cancer Is and Why It Matters

    Prostate cancer arises from the prostate gland’s epithelial cells and is the most common non-skin cancer in American men, with approximately 300,000 new diagnoses and 35,000 deaths annually. The vast majority of these diagnoses are localized disease treated with surgery or radiation. But approximately 10 to 15% of men present with or develop distant metastatic disease.

    Metastatic hormone-sensitive prostate cancer (the historical term; the FDA’s new terminology is metastatic androgen pathway modulation-naïve or -sensitive, mAPMN/S) is defined by prostate cancer that has spread to distant sites (typically bone, lymph nodes, lung, and liver) in a patient whose cancer still responds to androgen deprivation. The cancer cells require androgen signaling for growth and survival; removing androgen stimulation (through chemical or surgical castration) causes tumor regression and disease control.

    Despite this initial responsiveness, the disease is incurable in the metastatic setting. Most patients progress to mCRPC, typically within 20 months. Progression to mCRPC is associated with significantly worse outcomes, including increased patient burden, worse quality of life, and life expectancy of less than two years. Delaying the transition from hormone-sensitive to castration-resistant disease is therefore a meaningful clinical goal.

    The modern standard of care in mHSPC

    The treatment of mHSPC has evolved substantially over the past decade. Androgen deprivation therapy (ADT, typically LHRH agonist or antagonist) is the backbone. Added to ADT, androgen receptor pathway inhibitors (ARPIs) including abiraterone acetate plus prednisone, enzalutamide, apalutamide, and darolutamide have each demonstrated overall survival benefits in randomized Phase 3 trials and are now considered standard of care as doublet therapy. In high-volume disease, docetaxel chemotherapy plus ADT plus ARPI (triplet therapy) is supported by data from the ARASENS and ENZAMET trials.

    The modern first-line standard in mHSPC already produces strong responses: median rPFS of more than 24 months and overall survival benefits of 20 to 40% versus ADT alone in the pivotal ARPI trials. PSMAddition asked whether adding Pluvicto to this already-effective doublet standard provides additional, meaningful benefit.


    What PSMA Is and How Radioligand Therapy Works

    Prostate-specific membrane antigen (PSMA) is a transmembrane protein expressed on the surface of prostate epithelial cells. In normal prostate tissue, PSMA expression is moderate. In prostate cancer cells, expression is dramatically upregulated, typically 100 to 1,000 times higher than in normal tissue. More than 80% of patients with prostate cancer highly express the PSMA biomarker, making it a promising therapeutic target. Oncodaily

    Lutetium Lu 177 vipivotide tetraxetan (Pluvicto) combines two components: a targeting ligand (vipivotide tetraxetan, which binds with high affinity to PSMA) and a radioactive payload (lutetium-177, a beta-particle emitter). After intravenous administration, the targeting ligand circulates through the bloodstream, binds to PSMA-expressing prostate cancer cells wherever they are located in the body, and the lutetium-177 delivers a localized radiation dose that damages DNA in the bound cancer cell and in adjacent cells through the crossfire effect of beta particles.

    This “seek and destroy” mechanism is fundamentally different from traditional external beam radiation (which treats a defined anatomic field) or systemic chemotherapy (which damages all rapidly dividing cells). Radioligand therapy delivers radiation specifically to cells expressing the target protein, producing cytotoxic effects at metastatic sites throughout the body while sparing PSMA-negative normal tissues. The primary off-target organs that express PSMA at lower levels, including the salivary glands, lacrimal glands, and kidneys, receive the most significant off-target radiation, explaining the characteristic adverse effects of dry mouth (xerostomia), dry eyes, and the requirement for renal monitoring.

    PSMA PET imaging: required for patient selection

    Because the therapeutic benefit of Pluvicto depends on PSMA expression in the tumor, PSMA PET/CT imaging is required before treatment to confirm that the patient’s metastatic lesions express PSMA at adequate levels. The FDA-approved imaging agents for this purpose include Locametz (gallium Ga 68 gozetotide) and Pylarify (piflufolastat F 18), among others. Patients whose tumors do not adequately express PSMA on PET imaging are not appropriate candidates for Pluvicto, as the radioligand would have insufficient target for effective delivery.


    Pluvicto’s Clinical Development: The Evidence That Preceded PSMAddition

    Understanding the PSMAddition approval requires context from the trials that established Pluvicto’s foundational efficacy in mCRPC.

    VISION: The pivotal mCRPC trial (2022 approval)

    VISION (NCT03511664) enrolled 831 patients with PSMA-positive mCRPC who had received prior taxane chemotherapy and at least one ARPI. Randomized 2:1 to Pluvicto plus standard of care or standard of care alone. Median OS 15.3 months (Pluvicto) versus 11.3 months (SoC); HR 0.62 (95% CI 0.52 to 0.74). Median rPFS 8.7 months versus 3.4 months; HR 0.40. These results established Pluvicto as a meaningful survival-extending treatment in post-ARPI, post-taxane mCRPC.

    PSMAfore: The taxane-naïve mCRPC indication (September 2024 approval)

    PSMAfore (NCT04689594) randomized 468 patients with taxane-naïve mCRPC after one prior ARPI to Pluvicto versus a change in ARPI. The primary rPFS HR was 0.41 (95% CI 0.29 to 0.56), more than doubling rPFS. The crossover-adjusted OS HR was 0.80 (95% CI 0.48 to 1.33). This supported the September 2024 approval for the pre-taxane mCRPC setting.

    PSMAddition: The mHSPC indication (July 2026 approval)

    PSMAddition moves Pluvicto further upstream, before castration resistance develops.


    The PSMAddition Trial: Complete Data

    Design

    PSMAddition (NCT04720157) is a Phase 3, open-label, prospective, multicenter, randomized trial. In total, the PSMAddition trial enrolled 1,144 patients who were randomly assigned to receive 7.4 GBq plus or minus 10% of 177Lu-PSMA-617 for 6 cycles plus ADT and ARPI (n=572) or to ADT and ARPI alone (n=572). Patients were eligible for enrollment if they had untreated or minimally treated mHSPC, an ECOG performance status of 0 to 2, at least 1 PSMA-positive metastatic lesion per 68Ga-PSMA-11 PET/CT imaging, and were appropriate for ADT plus ARPI. Urology Times

    The ARPI was selected by the investigator and could include abiraterone, apalutamide, enzalutamide, darolutamide, or another approved ARPI. Patients also received ongoing medical castration or had undergone bilateral orchiectomy.

    The primary endpoint was rPFS by blinded independent radiological central review (BIRC), defined as time to radiographic progression by PCWG3-modified RECIST 1.1 or death. OS was the key secondary endpoint.

    The data presented here are from the interim analysis with a data cutoff of January 13, 2025, and a median follow-up of 23.6 months. The trial was presented by Dr. Scott Tagawa of Weill Cornell Medicine at the ESMO 2025 Presidential Symposium in Berlin.

    Primary and key secondary results

    EndpointPluvicto plus ADT plus ARPIADT plus ARPIResult
    Median rPFS (primary, BIRC)Not reachedNot reachedHR 0.72 (95% CI 0.58 to 0.90); p=0.002
    rPFS risk reduction28%Reference—
    OS (key secondary)Not reachedNot reachedHR 0.84 (95% CI 0.63 to 1.13); p=0.125
    ORR per RECIST 1.185.3% (95% CI 79.9% to 89.6%)80.8% (95% CI 74.8% to 85.8%)Favors Pluvicto
    Complete response57.1%42.3%Substantially higher with Pluvicto
    PSA below 0.2 ng/mL at 48 weeks87.4% (95% CI 83.6% to 90.6%)74.9% (95% CI 70.3% to 79.1%)Favors Pluvicto
    Time to mCRPC——HR 0.70 (95% CI 0.58 to 0.84)
    Time to PSA progression——HR 0.42 (95% CI 0.30 to 0.59)
    rPFS benefit consistencyConsistent across high/low disease volume, de novo/recurrent disease—All subgroups favored Pluvicto

    Sources: UroToday ESMO 2025 coverage. Urology Times PSMAddition full data. OncoDaily PSMAddition summary. NCT04720157.

    Safety

    Safety endpointPluvicto armControl arm
    Any adverse event98.4%96.6%
    Grade 3 or higher adverse events50.7%43.0%
    Main grade 3 or higher eventsCytopenias (14%), driven by radioligand myelosuppression—
    Dry mouth (xerostomia)Grade 1: 41%; grade 2: 5%3.8% total
    Treatment-related deathsNoneNone
    Quality of life (FACT-P, EQ-5D)No meaningful difference between armsNo meaningful difference between arms

    The Clinical Debate: What the ESMO Commentary Said and Why It Matters

    Presenting at the ESMO 2025 Presidential Symposium alongside the PSMAddition data, invited discussant Dr. Neeraj Azad of Johns Hopkins University raised pointed concerns about the PSMAddition results that warrant inclusion in any clinical summary of this approval.

    Dr. Azad stated: “There is a significant rPFS benefit from treatment, but no improvement in overall survival, and quality of life is numerically lower. The goal of any anticancer treatment ideally should be to make patients live longer and live better. This goal has not been achieved in PSMAddition.” He added that although he would consider using the regimen for certain patients, he “would not recommend widespread use of lutetium PSMA in mHSPC at this stage, particularly as I have concerns about patient selection, overtreatment, and toxicity.” Targeted Oncology

    The concerns Dr. Azad raised are legitimate and specific:

    No OS benefit demonstrated: The OS hazard ratio of 0.84 (p=0.125) represents a trend in the right direction, but it did not reach statistical significance at the interim analysis. OS is the endpoint that unambiguously demonstrates that patients live longer. In mHSPC, where modern ARPI-based doublet therapy already provides meaningful OS benefit over ADT alone, the bar for adding another agent to that doublet is whether it extends life. PSMAddition has not yet established that it does.

    Overtreatment concern: The modern ARPI-based doublet standard of care in mHSPC already produces deep responses in a majority of patients. Adding a radioligand therapy to an already-effective regimen raises the question of whether the added complexity, toxicity, and cost of Pluvicto is justified by the incremental benefit, particularly in patients who might achieve excellent outcomes on doublet therapy alone.

    Toxicity: Grade 3 or higher adverse events were higher in the Pluvicto arm (50.7% versus 43.0%), driven primarily by cytopenias from myelosuppression. Dry mouth, a persistent and quality-of-life-affecting toxicity from PSMA expression in salivary glands, affected 46% of Pluvicto-treated patients (41% grade 1, 5% grade 2) versus only 3.8% of control arm patients.

    The counterarguments:

    These concerns are real, but the full picture is more nuanced. The rPFS benefit (HR 0.72) was statistically significant and consistent across all subgroups including both high- and low-volume disease and de novo and recurrent mHSPC. The complete response rate improvement (57.1% versus 42.3%) and PSA suppression data (87.4% versus 74.9% achieving PSA below 0.2 ng/mL at 48 weeks) suggest meaningfully deeper disease control with the addition of Pluvicto. The time to mCRPC HR of 0.70 means the drug is delaying the transition to the most dangerous phase of the disease. And the OS data are immature: with median OS not yet reached in either arm at 23.6 months of follow-up, there is insufficient data to conclude that Pluvicto does not extend overall survival.

    The FDA’s approval reflects a judgment that the rPFS benefit, the consistency of secondary endpoints, and the absence of OS detriment together establish a benefit-risk profile that supports use in selected patients. The expert concerns reflect a judgment that for a disease setting where current standard of care already works well, the evidence of added benefit should include OS to support broad use.

    Both positions are reasonable given the available data. This is genuinely an ongoing scientific conversation, not a settled matter.


    Pluvicto’s Complete Indication Picture After July 2026

    Pluvicto is now the only PSMA-targeted agent approved across the full spectrum of metastatic prostate cancer:

    IndicationSettingApproval dateTrial support
    PSMA-positive mCRPC, after taxane and ARPIPost-ARPI, post-taxane mCRPCMarch 23, 2022VISION
    PSMA-positive mCRPC, before taxanePost-ARPI, taxane-naïve mCRPCSeptember 2024PSMAfore
    PSMA-positive mAPMN/S (mHSPC), plus ARPIHormone-sensitive metastatic diseaseJuly 31, 2026PSMAddition

    The trajectory across all three approvals represents a systematic movement upstream in the disease course: from post-ARPI post-taxane last resort, to pre-taxane ARPI-failed disease, to hormone-sensitive first-line metastatic disease. Novartis is also investigating Pluvicto in the oligometastatic setting (PSMA-DC, NCT05939414), potentially extending its use even earlier.


    Safety, Dosing, and Administration Requirements

    Pluvicto’s administration in the mHSPC setting uses the same dose and schedule as in mCRPC: 7.4 GBq (200 mCi) intravenously every 6 weeks for 6 cycles.

    Warnings (unchanged from prior approvals):

    Radiation exposure: Pluvicto is a radioactive therapeutic. Healthcare providers must follow institutional radiation safety protocols. Patients emit radiation after each dose and must limit close contact with others, particularly children and pregnant women, for several days post-treatment. Providers and clinical staff should use appropriate radiation protection measures.

    Myelosuppression: Beta-particle radiation from lutetium-177 affects bone marrow function. Grade 3 or higher cytopenias occurred in 14% of PSMAddition Pluvicto-treated patients. CBC monitoring before each cycle is required. Dose modification for clinically significant myelosuppression follows the prescribing information.

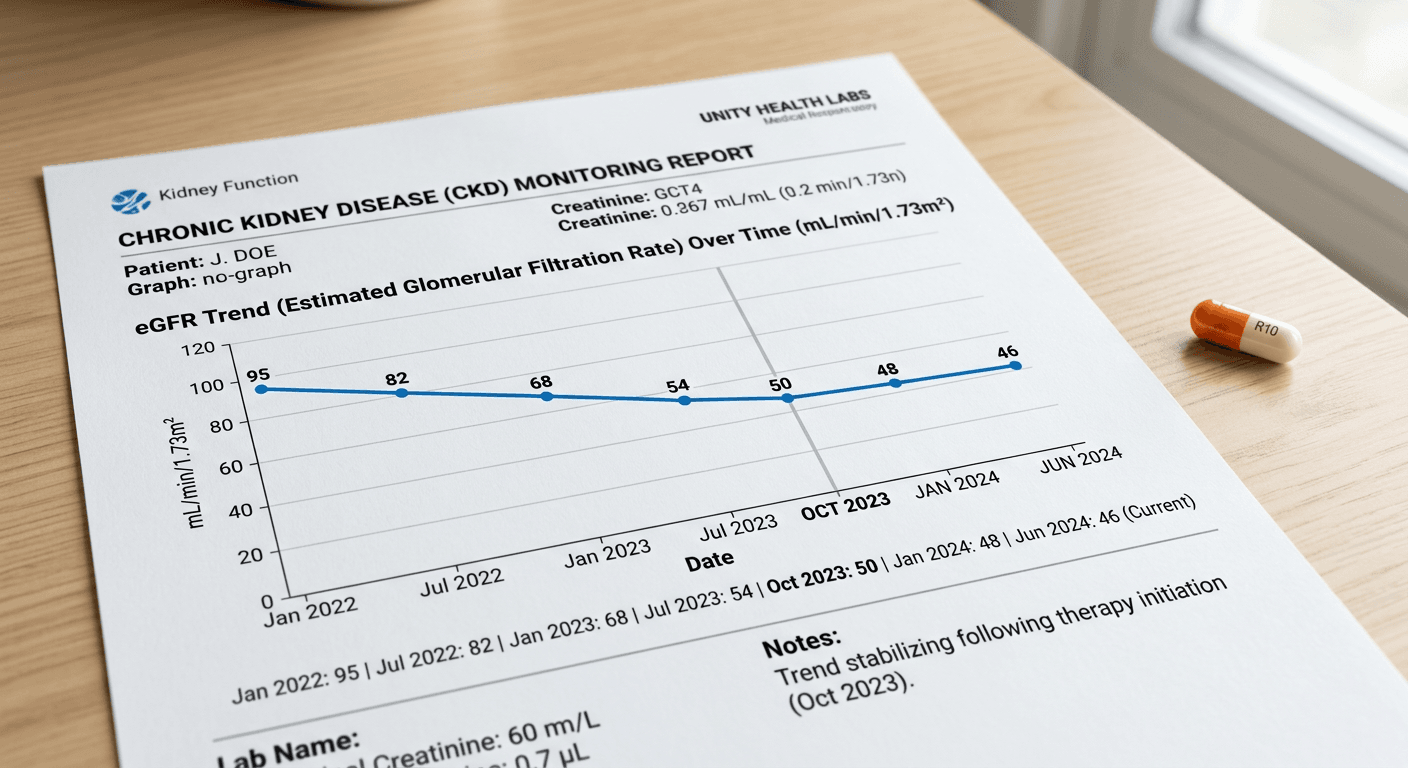
    Renal toxicity: Kidneys express PSMA at lower levels than prostate cancer cells and receive some radiation dose from Pluvicto. Renal function monitoring (creatinine, eGFR) before and during treatment is required.

    Embryo-fetal toxicity and infertility: Radioligand therapy can cause radiation-induced fetal harm and may reduce fertility. Effective contraception is required during treatment and for a specified time after the last dose.

    Administration setting: Pluvicto must be prepared and administered at authorized nuclear medicine or radiation oncology facilities with appropriate radiation handling infrastructure. It cannot be administered in a standard oncology infusion center without radiation safety certification.

    The PSMA PET imaging requirement before each new course should be incorporated into the patient pathway. Patients must confirm PSMA expression before initiating mHSPC treatment with Pluvicto.


    What This Means for Urologic Oncologists and Patients

    For urologic oncologists and medical oncologists

    The PSMAddition approval provides a new approved option for PSMA-positive mHSPC added to ARPI-based doublet therapy. The treatment decision should incorporate the full data picture, including both the statistically significant rPFS benefit and the absence of statistically significant OS benefit at the interim analysis.

    Patient selection will be central to appropriate use. Patients with high PSMA expression on PET, high-volume disease, and tolerance for the added toxicity of a radioligand therapy may be the population for whom adding Pluvicto to doublet therapy is most likely to provide meaningful benefit. The subgroup analyses showed consistent rPFS benefit across disease volume and disease presentation subgroups, which does not clearly identify a subset where benefit is substantially larger.

    The requirement for PSMA PET imaging, nuclear medicine administration infrastructure, and radiation safety protocols means this regimen is not operationally straightforward for all practices. Referral to centers experienced with radioligand therapy is appropriate for patients being considered for Pluvicto in the mHSPC setting.

    The ongoing OS data from PSMAddition will be a critical piece of evidence as treatment guidelines evolve. Updated analyses with longer follow-up will clarify whether the rPFS benefit translates into survival benefit, which will significantly affect how broadly this approval is incorporated into standard practice.

    For patients with newly diagnosed or minimally treated mHSPC

    If you have been recently diagnosed with metastatic prostate cancer and your cancer has been confirmed to express PSMA on PET imaging, the July 2026 approval means that adding Pluvicto to your standard doublet therapy is now an FDA-approved option. This is a meaningful expansion of what is available to you.

    The conversation with your urologist or medical oncologist should include: your PSMA PET imaging results and the degree of PSMA expression; the overall response your cancer shows to ADT plus ARPI; your performance status and tolerance for the added treatment burden and potential side effects, particularly xerostomia and myelosuppression; the logistics of receiving radioligand therapy at a certified nuclear medicine facility; and the honest acknowledgment that this approval is based on delay of radiographic progression and that overall survival benefit has not yet been statistically confirmed.

    For patients who prefer to weigh these considerations carefully before proceeding, waiting for updated OS data from PSMAddition in 2027 or 2028 while receiving effective doublet therapy is a legitimate approach, and the ESMO expert commentary supports this individualized decision-making.

    For related HED coverage on prostate cancer and radioligand therapy, see our broader oncology post series, and for context on the PSMA imaging requirement, the Urology Care Foundation (urologyhealth.org; 1-800-828-7866) and the Prostate Cancer Foundation (pcf.org) maintain current patient resources on PSMA-targeted therapy, PSMA PET imaging access, and prostate cancer treatment decision-making.


    Sources

    FDA approval announcement: FDA approves lutetium Lu 177 vipivotide tetraxetan with androgen receptor pathway inhibitor therapy for metastatic androgen pathway modulation-naïve or -sensitive prostate cancer. FDA.gov. July 31, 2026.

    Novartis FDA approval press release: FDA approves Pluvicto for PSMA+ metastatic hormone-sensitive prostate cancer (mHSPC), advancing potential new standard of care across metastatic disease. GlobeNewswire. July 31, 2026.

    Novartis US press release: FDA approves Pluvicto for PSMA+ metastatic hormone-sensitive prostate cancer. Novartis US. July 31, 2026.

    Drugs.com approval news: FDA Approves Pluvicto for PSMA+ Metastatic Hormone-Sensitive Prostate Cancer (mHSPC). drugs.com. July 31, 2026.

    Urology Times (full PSMAddition data including all secondary endpoints, complete safety table): FDA approves lutetium Lu 177 vipivotide tetraxetan for PSMA-positive mHSPC. urologytimes.com. July 2026. and PSMAddition: Adding 177Lu-PSMA-617 to ADT plus ARPI extends rPFS in mHSPC.

    UroToday (ESMO 2025 Presidential Symposium, complete endpoint table, QoL data): ESMO 2025: Phase III Trial of PSMAddition. urotoday.com. October 2025.

    OncoDaily (full PSMAddition data summary including ARPI options, AUO meeting PSA data): FDA Approved Pluvicto Plus ARPI for PSMA-Positive mAPMN/S Prostate Cancer. oncodaily.com. July 2026.

    Oncology News Central (Dr. Azad ESMO 2025 commentary and full concern statement): Despite Positive Data From the PSMAddition Trial, Expert at ESMO 2025 Raises Concerns. oncologynewscentral.com. October 2025.

    OncoDaily PSMAddition clinical summary (HR, CI, all secondary endpoint data): PSMAddition: 177Lu-PSMA-617 Extends PFS in mHSPC. oncodaily.com.

    Targeted Oncology (benefit consistency, positioning as potential new standard): 177Lu PSMA-617 Improves rPFS in mHSPC: PSMAddition Trial. targetedonc.com.

    PSMAddition trial registration: NCT04720157. ClinicalTrials.gov.

    Novartis PSMAddition positive announcement (May 2026 PSA analysis): PSMAddition data show Novartis Pluvicto delays progression to end-stage prostate cancer. novartis.com.

    PSMAfore data (prior PSMAfore approval context): Novartis Pluvicto shows clinically meaningful and highly statistically significant rPFS benefit in taxane-naive mCRPC. novartis.com.

    Prostate cancer overview: Prostate Cancer. StatPearls. NCBI.

    Pluvicto prescribing information: PLUVICTO (lutetium Lu 177 vipivotide tetraxetan) Prescribing Information. Novartis Pharmaceuticals Corporation. 2026.

    Pluvicto approval history: Pluvicto FDA Approval History. drugs.com.

    Patient resources: Prostate Cancer Foundation | Urology Care Foundation: 1-800-828-7866 | ZERO Prostate Cancer | Novartis Pluvicto patient support | ClinicalTrials.gov: search lutetium prostate cancer

    Disclaimer: Health Evidence Digest provides general information about FDA approvals and health research for educational purposes. This content is not a substitute for professional medical advice. The PSMAddition trial met its primary endpoint of radiographic progression-free survival; overall survival data were immature at the interim analysis and showed a trend toward benefit that did not reach statistical significance. Expert debate exists about the appropriate patient selection for Pluvicto in the mHSPC setting given the absence of a statistically significant OS benefit and higher grade 3 or higher adverse event rates versus standard of care alone. Pluvicto is a radioactive therapeutic requiring administration at certified nuclear medicine facilities with appropriate radiation safety infrastructure. PSMA PET imaging confirmation of PSMA expression is required before initiating treatment. All treatment decisions for metastatic prostate cancer should be made in close collaboration with a board-certified urologic oncologist or medical oncologist with expertise in advanced prostate cancer and radioligand therapy.

  • Fabhalta Received Accelerated Approval for IgA Nephropathy in 2024 Based on Proteinuria Reduction. On July 16, 2026, the FDA Confirmed That Reduction Actually Preserved Kidney Function. Here Is Why That Distinction Matters.

    Fabhalta Received Accelerated Approval for IgA Nephropathy in 2024 Based on Proteinuria Reduction. On July 16, 2026, the FDA Confirmed That Reduction Actually Preserved Kidney Function. Here Is Why That Distinction Matters.

    The essentials: On July 16, 2026, the FDA granted traditional (full) approval to Fabhalta (iptacopan, Novartis) to slow kidney function decline in adults with primary IgA nephropathy (IgAN) at risk of disease progression. This is a regulatory conversion from accelerated approval (granted August 2024 for reduction of proteinuria) to traditional approval based on confirmatory eGFR data from the Phase 3 APPLAUSE-IgAN study. Fabhalta is now the first and only complement inhibitor with traditional FDA approval for IgAN, and the first drug in any IgAN indication to demonstrate preservation of kidney function through a statistically significant and clinically meaningful reduction in eGFR decline over two years. The APPLAUSE-IgAN primary endpoint (published NEJM 2025): annualized mean change from baseline in eGFR over 24 months: minus 3.0 mL/min/1.73 m2/year (iptacopan) versus minus 5.7 mL/min/1.73 m2/year (placebo). Absolute difference: 2.7 mL/min/1.73 m2/year benefit. 48% slowing of eGFR decline versus placebo. UPCR at month 24: consistent with the interim analysis data that supported accelerated approval (38% reduction versus placebo at 9 months). UPCR onset: clinically meaningful reduction as early as 2 weeks. Composite kidney failure endpoint: kidney failure event in 21.4% (iptacopan) versus 33.5% (placebo); HR 0.6 (95% CI 0.4 to 0.8); p=0.0015. Sustained 30% or greater decline in eGFR from baseline: 21% (iptacopan) versus 33.1% (placebo). Primary NEJM publication: Perkovic V, Barratt J, Rovin B et al. Alternative complement pathway inhibition with iptacopan in IgA nephropathy. NEJM. 2025;392:531-543. doi:10.1056/NEJMoa2410316. The full APPLAUSE-IgAN indication now reads: to slow the decline in kidney function in adults with primary IgAN at risk of rapid disease progression, generally a UPCR at or above 0.75 g/g. The prior accelerated approval language (to reduce proteinuria) was superseded by the traditional approval language (to slow decline in kidney function). Key safety: boxed warning for serious and life-threatening infections caused by encapsulated bacteria (Streptococcus pneumoniae, Neisseria meningitidis, Haemophilus influenzae type b), requiring vaccination before treatment initiation and ongoing vigilance. REMS program remains in effect. Most common adverse reactions in IgAN: abdominal pain, dizziness, nausea. Fabhalta’s other two indications (PNH and C3G) are not affected by this action.

    In the post on Trutakna earlier in HED’s coverage of the 2026 IgAN approval wave, we explained what accelerated approval means and what it does not. The short version: a drug that receives accelerated approval for reducing proteinuria has demonstrated that it lowers a surrogate marker that predicts kidney health. It has not yet demonstrated that it actually preserves kidney function over the years of treatment that matter to patients.

    Fabhalta received its accelerated approval in August 2024 precisely because of this distinction. The APPLAUSE-IgAN interim analysis at 9 months showed a 38% reduction in UPCR compared to placebo, statistically significant and clinically meaningful. The FDA and Novartis were explicit in the accelerated approval label: it had not been established whether Fabhalta slows kidney function decline. The continued approval was contingent on verifying that the proteinuria reduction translated into preserved eGFR.

    On October 16, 2025, Novartis announced that APPLAUSE-IgAN met its primary endpoint: over 24 months, iptacopan slowed eGFR decline by 48% versus placebo (minus 3.0 versus minus 5.7 mL/min/1.73 m2/year). The eGFR story confirmed what the proteinuria surrogate had predicted. The conversion to traditional approval, completed July 16, 2026, reflects the FDA’s formal conclusion that the clinical benefit is real and established.

    This post covers what IgAN is and what happens to kidneys when it progresses, how iptacopan’s complement Factor B inhibition mechanism targets a key driver of that progression, what the complete APPLAUSE-IgAN data shows, what the accelerated-to-traditional conversion means for the IgAN treatment landscape, and where Fabhalta now sits relative to the growing number of approved IgAN therapies.


    What IgA Nephropathy Is and Why the eGFR Endpoint Matters

    IgA nephropathy is the most common primary glomerulonephritis worldwide, occurring when galactose-deficient IgA1 antibodies and their immune complexes deposit in the mesangium of the kidney’s glomeruli. The deposited immune complexes trigger complement activation, inflammatory cell recruitment, mesangial cell proliferation, and progressive fibrosis of the glomerular architecture. The clinical consequence is an inexorable decline in the kidney’s filtering capacity, measured by the fall in estimated glomerular filtration rate (eGFR) over years.

    The disease burden of IgAN is substantial. Up to 50% of IgAN patients with persistent proteinuria progress to kidney failure within 10 to 20 years of diagnosis, often requiring dialysis and kidney transplantation. This statistic is the reason why the distinction between proteinuria reduction and eGFR preservation is not a regulatory technicality. It is the difference between demonstrating that a drug affects a biomarker that predicts kidney failure and demonstrating that it actually reduces the risk of kidney failure. HCP Live

    Why eGFR is the endpoint that matters most

    Estimated glomerular filtration rate (eGFR) is calculated from serum creatinine (and increasingly cystatin C) using validated equations and serves as the best clinically accessible measure of how well the kidneys are filtering blood. Normal eGFR in a healthy young adult is approximately 90 to 120 mL/min/1.73 m2. As glomerular damage accumulates in IgAN, eGFR falls progressively. Below 15 mL/min/1.73 m2, kidney failure requiring dialysis or transplantation typically occurs.

    The rate of eGFR decline is directly predictive of time to kidney failure. A patient with IgAN losing 5.7 mL/min/1.73 m2 per year (the placebo rate in APPLAUSE-IgAN) will reach kidney failure thresholds approximately twice as fast as a patient losing 3.0 mL/min/1.73 m2 per year (the iptacopan rate). Over a decade, this difference compounds into years of kidney function preserved.

    Proteinuria (measured by UPCR) is an important and validated surrogate: higher proteinuria predicts faster eGFR decline, and reducing proteinuria predicts slowing eGFR decline. But it is a prediction, not a demonstration. The regulatory value of the APPLAUSE-IgAN eGFR data is that it converts the prediction into clinical evidence.


    How Iptacopan Works: Factor B Inhibition of the Alternative Complement Pathway

    Complement is a system of proteins that form a critical arm of innate immunity, capable of directly lysing pathogens, marking them for phagocytosis, and triggering inflammation. The system operates through three pathways (classical, lectin, and alternative) that converge on a common lytic mechanism. In IgAN, the alternative complement pathway (ACP) plays a central role in amplifying the inflammatory injury triggered by IgA immune complex deposition in the mesangium.

    The alternative complement pathway is constitutively activated at low levels under normal conditions through spontaneous hydrolysis of C3. When immune complexes or other activating surfaces are present, this spontaneous activation is dramatically amplified through a positive feedback loop: C3b deposits on activating surfaces, recruits Factor B, which is cleaved by Factor D to form the alternative pathway C3 convertase (C3bBb). This convertase cleaves more C3, generating more C3b and amplifying the loop. The downstream consequence in IgAN is glomerular inflammation, mesangial cell activation, and progressive injury.

    Iptacopan is an oral, once-daily, small-molecule inhibitor of complement Factor B, the key amplification enzyme of the alternative pathway. By blocking Factor B, iptacopan prevents the formation and activity of the alternative pathway C3 convertase, selectively inhibiting ACP amplification without globally suppressing all complement pathways. This selectivity is pharmacologically important: the classical pathway (which handles routine immune complex clearance) and the lectin pathway (which handles certain pathogen recognition) are not directly inhibited, preserving aspects of innate immunity while specifically targeting the amplification loop responsible for the complement-driven injury in IgAN.

    Iptacopan was discovered by Novartis and is the first approved oral Factor B inhibitor. The oral small-molecule format (twice daily, 200 mg capsules) is clinically significant in a nephrology population that commonly takes multiple medications daily and for whom an intravenous or subcutaneous dosing requirement would add meaningful burden.


    The APPLAUSE-IgAN Study: Complete Data

    Design

    APPLAUSE-IgAN (NCT04578834) was a Phase 3, multicenter, randomized, double-blind, placebo-controlled trial enrolling adults with biopsy-confirmed primary IgAN who had eGFR of 30 to 90 mL/min/1.73 m2 at baseline and UPCR at or above 0.75 g/g despite optimized background therapy (maximally tolerated RAAS blockade). Patients were randomized 1:1 to iptacopan 200 mg twice daily or placebo for 24 months.

    The trial had two pre-specified analysis timepoints: a 9-month interim analysis for proteinuria (which supported accelerated approval in August 2024) and a 24-month final analysis for eGFR (which supported the traditional approval in July 2026).

    The primary endpoint for the traditional approval was the annualized mean change from baseline in eGFR over 24 months, assessed by the slope of eGFR over time using a linear mixed-effects model.

    APPLAUSE-IgAN complete results

    EndpointIptacopanPlaceboResult
    Annualized mean eGFR change from baseline (24 months, primary)Minus 3.0 mL/min/1.73 m2/yearMinus 5.7 mL/min/1.73 m2/year2.7 mL/min/1.73 m2/year benefit; 48% slowing; p less than 0.001
    Sustained 30% or greater eGFR decline from baseline21.0%33.1%Substantially lower with iptacopan
    Composite kidney failure event21.4%33.5%HR 0.6 (95% CI 0.4 to 0.8); p=0.0015
    UPCR at month 9 (accelerated approval interim)Minus 44% from baselineMinus 9% from baseline38% reduction versus placebo; p less than 0.0001
    UPCR at month 24 (consistent with interim)SustainedSustainedConsistent with 9-month data
    Onset of proteinuria reductionAs early as 2 weeks—Clinically meaningful early onset
    Consistent treatment effect across subgroupsYes—Including baseline eGFR, proteinuria, SGLT2i use

    Source: Perkovic V, Barratt J, Rovin B et al. Alternative complement pathway inhibition with iptacopan in IgA nephropathy. NEJM. 2025;392:531-543. doi:10.1056/NEJMoa2410316. NCT04578834.

    The composite kidney failure endpoint result, a 40% relative reduction in kidney failure events (HR 0.6), is among the most clinically meaningful findings in the APPLAUSE-IgAN dataset. The absolute difference (21.4% versus 33.5%) means that approximately 1 in 8 patients avoided a kidney failure event over the 24-month period by receiving iptacopan. In a disease where kidney failure means dialysis or transplantation, this is a meaningful difference in outcomes.

    The consistency of treatment effect across subgroups, including patients already on SGLT2 inhibitors (which also reduce proteinuria and are increasingly used in IgAN), is clinically relevant. The benefit of iptacopan appears additive to SGLT2 inhibitor background therapy rather than redundant, supporting its use in patients already on other IgAN-active agents.


    The Regulatory Conversion: What It Means in the IgAN Context

    This is the second accelerated-to-traditional approval conversion in IgAN following the post I covered for Retevmo in the broader precision oncology space, but here the conversion is specifically meaningful for nephrology practice.

    The August 2024 accelerated approval for Fabhalta came with explicit language that was required in the label and in clinical communication: it has not been established whether Fabhalta slows kidney function decline. For patients, this meant starting a treatment whose long-term kidney benefit had not been proven. For payers, it meant coverage decisions made on surrogate data. For clinicians, it meant uncertainty about whether the drug would ultimately demonstrate what the surrogate predicted.

    The July 2026 traditional approval resolves each of these tensions. The eGFR data are the clinical outcome that patients, payers, and clinicians were waiting for. The 48% slowing of eGFR decline over two years is not a surrogate. It is a direct measure of kidney function preserved. The HR 0.6 for the composite kidney failure endpoint is a direct measure of clinical events prevented. These data change the nature of the clinical conversation about iptacopan from “we believe this is likely to help your kidneys” to “we have demonstrated that this helps your kidneys.”

    The practical implications for prescribing are modest because the indication, dosing, and patient population are unchanged. But the traditional approval removes the post-marketing uncertainty and strengthens the evidence base for formulary coverage and guideline integration.


    Fabhalta’s Complete Indication Picture After July 2026

    Iptacopan is the only drug currently approved across three distinct complement-mediated rare diseases:

    IndicationApproval typeDateBasis
    Paroxysmal nocturnal hemoglobinuria (PNH): increase hemoglobin and reduce need for transfusions without eculizumab/ravulizumabTraditionalDecember 5, 2023APPLY-PNH Phase 3
    Primary IgAN: reduce proteinuriaAccelerated (now superseded)August 8, 2024APPLAUSE-IgAN 9-month interim
    Primary IgAN: slow decline in kidney functionTraditionalJuly 16, 2026APPLAUSE-IgAN 24-month final
    Complement 3 glomerulopathy (C3G): reduce proteinuriaAcceleratedNovember 2025APPEAR-C3G Phase 3

    The PNH indication, the original approval, demonstrated that iptacopan could be given as a standalone therapy to patients previously dependent on IV terminal complement inhibitors (eculizumab, ravulizumab), providing a fully oral alternative for a disease that had been managed exclusively with biweekly or monthly IV infusions. The C3G indication reflects the same Factor B mechanism applied to a different complement-driven kidney disease.


    Where Fabhalta Fits in the IgAN Treatment Landscape After July 2026

    The IgAN treatment landscape, covered in detail in our earlier post on Trutakna (atacicept-vymj, Vera Therapeutics), now includes six approved therapies targeting different mechanisms. Fabhalta’s traditional approval for eGFR preservation makes it the only drug in the IgAN space with full FDA approval based on a kidney function outcome endpoint rather than the proteinuria surrogate.

    DrugMechanismFDA status in IgANPrimary endpoint achieved
    Tarpeyo (budesonide EC)Gut mucosal IgA reductionFull approval (2023)Proteinuria (UPCR)
    Filspari (sparsentan)Dual endothelin A and AT1 antagonistFull approval (2024)eGFR slope (PROTECT trial)
    Fabhalta (iptacopan)Complement Factor B inhibitorFull approval (July 2026)eGFR slope (APPLAUSE-IgAN)
    Vanrafia (atrasentan)Selective endothelin A antagonistFull approval (August 2024)Composite kidney endpoint (ALIGN)
    Trutakna (atacicept)Dual BAFF/APRIL inhibitorAccelerated approval (July 2026)Proteinuria (UPCR)

    Fabhalta is the only drug targeting complement in this landscape. Its mechanism is entirely distinct from the RAAS-adjacent approaches (sparsentan, atrasentan), the mucosal IgA approach (budesonide EC), and the B-cell cytokine approaches (atacicept). This mechanistic diversity is relevant for clinical decision-making: patients who are on one of the other approved agents and still progressing have a mechanistically distinct alternative available in iptacopan.

    The question of whether combination therapy across multiple mechanistic targets is safe and additive is one that ongoing clinical research is beginning to address but that is outside the current approved labels for any of these agents. Clinicians combining agents should do so with full awareness that combination safety and efficacy data are limited.


    Safety: The Boxed Warning and What It Means in Practice

    Boxed warning: serious infections from encapsulated bacteria

    Factor B inhibition selectively suppresses the alternative complement pathway. While this selectivity preserves classical and lectin pathway function, the alternative pathway plays an important amplification role in the defense against encapsulated bacteria, particularly Neisseria meningitidis, Streptococcus pneumoniae, and Haemophilus influenzae type b. Inhibition of the alternative pathway therefore increases susceptibility to infections from these organisms, which can be rapidly fatal.

    The Fabhalta prescribing information includes a boxed warning regarding an increased risk for serious and life-threatening infections caused by encapsulated bacteria, including Streptococcus pneumoniae, Neisseria meningitidis, and Haemophilus influenzae type b.

    Required vaccination before treatment initiation: Patients must be vaccinated against Neisseria meningitis (serogroups A, C, W, Y, and B; two separate meningococcal vaccines are required), Streptococcus pneumoniae, and Haemophilus influenzae type b before starting iptacopan, unless the urgency of treatment outweighs the risk of not being vaccinated. Vaccination must precede the first dose by at least 2 weeks whenever possible.

    REMS program: Fabhalta is available only through a Risk Evaluation and Mitigation Strategy (REMS) program. Prescribers must enroll in the REMS, patients must receive a medication guide, and pharmacies must be certified. The REMS exists to ensure patients are vaccinated before starting therapy and are educated about infection risk.

    Ongoing vigilance: Patients receiving iptacopan should be counseled to seek immediate medical attention for any signs of meningococcal infection: sudden onset of fever, headache, stiff neck, nausea, vomiting, sensitivity to light, or altered mental status. These can progress to life-threatening illness within hours.

    Common adverse reactions in IgAN

    The most common adverse reactions reported with iptacopan in adults with IgAN were abdominal pain, dizziness, and nausea. These were generally mild to moderate in severity. The adverse reaction profile in IgAN is consistent with the established safety experience from the PNH program, where iptacopan was generally well tolerated with the encapsulated bacteria infection risk being the dominant safety concern.

    Dosing

    Fabhalta is administered as 200 mg (two 100 mg capsules) orally twice daily, with or without food. This is the same dose and schedule as used in the PNH and C3G indications. No dose adjustments are required for mild to moderate renal impairment; guidance for severe impairment should be reviewed in the prescribing information.


    What This Means for Nephrologists and Patients

    For nephrologists managing primary IgAN

    The traditional approval of Fabhalta for eGFR preservation establishes the first complement inhibitor with a kidney function outcome in IgAN. This is a meaningful clinical milestone beyond regulatory classification: the APPLAUSE-IgAN data demonstrate that blocking the alternative complement pathway at Factor B translates into preserved kidney function over two years, not just reduced protein in the urine.

    The 2.7 mL/min/1.73 m2/year absolute benefit in eGFR slope may appear modest in isolation, but in the context of IgAN’s decades-long progression, it represents a meaningful delay in time to kidney failure. The composite kidney failure event data (HR 0.6; 21.4% versus 33.5%) provides the most direct clinical outcome evidence for iptacopan’s benefit.

    For patients already on Tarpeyo, sparsentan, or SGLT2 inhibitors: the consistent treatment effect of iptacopan across subgroups including SGLT2 inhibitor users supports its use as an add-on to background therapy. Whether it is additive to sparsentan or budesonide EC specifically is not established in the current trial data.

    The vaccination requirement and REMS program add administrative steps to prescribing that should be built into practice workflows. Patients should be identified for vaccination at the time the treatment decision is made, not after, to avoid treatment delays.

    For patients with primary IgAN

    The traditional approval means that iptacopan has proven, in a two-year randomized controlled trial, that it slows the loss of kidney function. For patients who have been told they are at risk of progressing to kidney failure, this is the most directly relevant clinical evidence for any IgAN therapy approved to date alongside sparsentan (which also demonstrated eGFR benefit in the PROTECT trial).

    The oral twice-daily dosing means no clinic visits for infusions or injections. The required vaccinations before starting are a one-time pre-treatment requirement, not an ongoing burden. The primary ongoing considerations are the infection monitoring, the twice-daily capsule regimen, and the management of GI adverse effects if they occur.

    For related HED coverage on the expanding IgAN treatment landscape, see our earlier post on Trutakna (atacicept-vymj), the first dual BAFF/APRIL inhibitor approved for IgAN, which received accelerated approval on July 7, 2026, and for broader complement biology context, our post on Tregzi (marnetegragene autotemcel), which covers complement system biology in the context of LAD-I gene therapy.

    For patients and families navigating an IgAN diagnosis, the IgA Nephropathy Foundation and the National Kidney Foundation (kidney.org; 1-800-622-9010) maintain current resources on treatment options, clinical trials, and patient support.


    Sources

    Novartis traditional approval press release: Novartis Fabhalta (iptacopan) receives FDA traditional approval as first and only complement inhibitor to significantly slow kidney function decline in primary IgAN. GlobeNewswire. July 16 to 17, 2026. Full press release.

    Drugs.com approval news: Novartis Fabhalta receives FDA traditional approval as first and only complement inhibitor to significantly slow kidney function decline in primary IgAN. drugs.com. July 2026.

    Renal and Urology News (composite kidney failure endpoint data, eGFR subgroup, adverse reactions): Fabhalta Earns Full FDA Approval to Slow Kidney Decline in Primary IgAN. renalandurologynews.com. July 2026.

    HCPLive (eGFR slope data, conversion context, complementary mechanisms in IgAN landscape): FDA Grants Full Approval to Iptacopan (Fabhalta) in IgAN. hcplive.com. July 2026.

    PharmExec (accelerated to traditional conversion narrative, REMS, Factor B mechanism): FDA Approves Fabhalta to Slow Kidney Function Decline in Primary IgAN. pharmexec.com. July 2026.

    APPLAUSE-IgAN primary NEJM publication: Perkovic V, Barratt J, Rovin B et al. Alternative complement pathway inhibition with iptacopan in IgA nephropathy. NEJM. 2025;392:531-543. doi:10.1056/NEJMoa2410316.

    APPLAUSE-IgAN primary endpoint announcement (Novartis, October 2025): Novartis Fabhalta meets Phase III primary endpoint, slows kidney function decline in patients with IgA nephropathy. novartis.com. October 16, 2025.

    APPLAUSE-IgAN accelerated approval press release (August 2024): Novartis receives FDA accelerated approval for Fabhalta for reduction of proteinuria in primary IgAN. novartis.com. August 8, 2024.

    APPLAUSE-IgAN trial registration: NCT04578834. ClinicalTrials.gov.

    IgA nephropathy overview: IgA Nephropathy (Berger Disease). StatPearls. NCBI.

    Complement system biology: Complement Pathway. PMC7234620.

    Iptacopan mechanism review: Olezarsen/Iptacopan complement mechanism reference. PMC12700839.

    Fabhalta prescribing information: FABHALTA (iptacopan) Prescribing Information. Novartis Pharmaceuticals Corp. July 2026.

    Fabhalta approval history: Fabhalta FDA Approval History. drugs.com.

    Patient resources: IgA Nephropathy Foundation | National Kidney Foundation: 1-800-622-9010 | American Kidney Fund | Novartis Fabhalta patient support

    Disclaimer: Health Evidence Digest provides general information about FDA approvals and health research for educational purposes. This content is not a substitute for professional medical advice. Fabhalta (iptacopan) carries a boxed warning for serious and life-threatening infections caused by encapsulated bacteria, including Neisseria meningitidis, Streptococcus pneumoniae, and Haemophilus influenzae type b. Vaccination against these pathogens is required before initiating treatment. Fabhalta is available only through a REMS program. Prescribing and monitoring should be carried out by a board-certified nephrologist or physician experienced in the management of primary IgA nephropathy and complement-mediated kidney disease.
  • The Contraceptive Patch Has Always Used More Estrogen Than Most Pills. Gwyn Lo Is the First Patch With a Dose That Matches the Low-Estrogen Standard of Modern Oral Contraceptives.

    The Contraceptive Patch Has Always Used More Estrogen Than Most Pills. Gwyn Lo Is the First Patch With a Dose That Matches the Low-Estrogen Standard of Modern Oral Contraceptives.

    The essentials: On July 28 to 29, 2026, the FDA approved Gwyn Lo (norelgestromin and ethinyl estradiol transdermal system, Viatris Inc.) as a once-weekly combined hormonal contraceptive (CHC) patch for the prevention of pregnancy in women of childbearing potential with a body mass index (BMI) below 30 kg/m² who are appropriate candidates for combined hormonal contraception. Gwyn Lo delivers norelgestromin 220 mcg/day and ethinyl estradiol (EE) 20 mcg/day. This is the lowest estrogen dose ever approved in an FDA-approved contraceptive patch. The comparison: currently marketed Xulane (norelgestromin and EE, Viatris) delivers 150 mcg/day norelgestromin and 35 mcg/day EE. Twirla (levonorgestrel and EE, Agile Therapeutics) delivers 120 mcg/day levonorgestrel and 30 mcg/day EE. Gwyn Lo delivers nearly half the estrogen of Xulane. What else changed: the progestin dose increased from 150 mcg/day (Xulane) to 220 mcg/day. The lower estrogen is compensated for with higher progestin in the matrix formulation. The regulatory pathway: 505(b)(2), referencing the approved Xulane safety and efficacy database. The clinical basis: Phase 3 Luminous Study (NCT05139121), a single-arm, open-label, multicenter study in approximately 1,200 healthy women aged 18 to 40 years across up to 13 cycles of treatment. Pearl Index in women aged 18 to 35 years (efficacy-evaluable population): 4.14 (95% CI 2.77 to 5.95). Patch adhesion: complete detachment occurred in only 1.3% of 39,790 patches applied. Efficacy was specifically demonstrated in women with BMI 25 to less than 30 kg/m², with no BMI-based limitation in that range. Application sites: abdomen, buttocks, and upper arm studied across four Phase 1 pharmacokinetic studies. Delivery maintained under sauna, whirlpool, treadmill exercise, and cold-water bathing conditions. Common adverse reactions (at or above 2%): application site irritation (4.8%), application site erythema (3.7%), application site pruritus (3.7%), intercycle bleeding (3.9%), heavy withdrawal bleeding (2.0%), and nausea (2.0%). Unscheduled bleeding improved substantially over time: 34.5% of women had unscheduled bleeding or spotting in Cycle 1, declining to 20.0% by Cycle 13. Commercial availability: expected in the United States later in 2026. The BMI limit is the most consequential label detail: Gwyn Lo is contraindicated in women with BMI at or above 30 kg/m². Approximately 40% of U.S. women of reproductive age have a BMI in that excluded range.

    The contraceptive patch has a specific place in the birth control landscape: it is for patients who want the hormonal efficacy of a combined oral contraceptive without the daily pill routine. Apply it once a week for three weeks, take a week off, repeat. It does not require refrigeration, does not require a daily alarm reminder, and has the same active ingredients as pills, just delivered through the skin.

    What the patch has always had that pills have not is a higher estrogen exposure. The first contraceptive patch, Ortho Evra, approved in 2001, delivered 20 mcg/day of ethinyl estradiol transdermally, which produces systemic estrogen exposure comparable to a pill delivering 35 to 50 mcg/day orally. Xulane, the generic-branded version that followed, delivers 35 mcg/day EE transdermally. As oral contraceptive formulations evolved toward lower and lower estrogen doses over the past 30 years, with 20 mcg/day pills now widely used, the patch stayed at the higher end of the hormonal range. For patients with estrogen sensitivity, or for those who prefer a formulation that matches the lower-dose standard of modern oral contraceptives, this has been a limitation of the patch format.

    Gwyn Lo (norelgestromin and ethinyl estradiol, Viatris), approved July 28, 2026, delivers 20 mcg/day EE, matching the estrogen level of the lowest-dose combined oral contraceptives. It does not change the hormones. It does not change the application schedule. What it changes is the estrogen dose, and for the patients for whom that dose matters, it provides the first patch option that delivers contraceptive protection at the low-estrogen tier.

    The other thing it does not change: the BMI restriction. Gwyn Lo is approved only for women with BMI below 30 kg/m². This is the most consequential restriction in the label, and it excludes approximately 40% of U.S. women of reproductive age. This post covers what that restriction means, why the contraceptive patch works the way it does, what Gwyn Lo’s specific dose profile is, what the Luminous Study showed, and how it fits alongside the existing contraceptive patch options.


    How Combined Hormonal Contraception Works

    Combined hormonal contraceptives (CHCs) contain two synthetic hormones: an estrogen (in all currently approved U.S. products, this is ethinyl estradiol) and a progestin (one of many synthetic progesterone analogs). The two hormones work together through several complementary mechanisms:

    Ovulation suppression: The primary mechanism. Exogenous estrogen and progestin suppress the pituitary’s release of follicle-stimulating hormone (FSH) and luteinizing hormone (LH) through negative feedback on the hypothalamic-pituitary-ovarian (HPO) axis. Without the LH surge, ovulation does not occur. Without ovulation, there is no egg to fertilize.

    Cervical mucus thickening: Progestins thicken the cervical mucus, making it harder for sperm to penetrate into the uterus. This provides a secondary contraceptive effect that operates even on days when ovulation suppression may be incomplete.

    Endometrial changes: Combined hormones alter the endometrial lining, making it less receptive to implantation if fertilization were to occur. This represents a tertiary mechanism.

    The relative contributions of these mechanisms vary based on the formulation. The higher the dose of progestin relative to estrogen, the more reliably ovulation is suppressed throughout the cycle. The estrogen component primarily provides cycle control (regular withdrawal bleeding) and enhances the ovulation-suppressive effect of the progestin.

    What transdermal delivery adds and changes

    Transdermal drug delivery avoids first-pass hepatic metabolism, which has two meaningful clinical consequences for hormonal contraceptives. First, the estrogen delivered transdermally does not undergo hepatic first-pass metabolism, meaning that its systemic bioavailability is higher per mcg applied than the same dose taken orally. Second, transdermal delivery bypasses the estrogen-driven hepatic protein synthesis that occurs with oral estrogen, specifically the hepatic production of sex hormone-binding globulin (SHBG), coagulation factors, and other proteins that are stimulated by oral estrogen passing through the liver.

    This hepatic protein synthesis differential is the basis for the FDA’s class-level concern about thromboembolism with higher-dose transdermal estrogen. Higher hepatic exposure to estrogen (from oral administration) more robustly stimulates coagulation factor production, but higher systemic exposure to estrogen (from transdermal administration of a higher dose) also affects coagulation biology through other mechanisms. The clinical data on VTE risk with transdermal versus oral contraceptives are complex and not fully resolved across all dosing levels, but the pharmacological rationale for minimizing transdermal estrogen dose is sound.


    The Contraceptive Patch Landscape and Where Gwyn Lo Fits

    Three combined hormonal contraceptive patches are now available or approved for use in the United States:

    ProductCompanyProgestin (mcg/day)Estrogen EE (mcg/day)BMI limitApproval
    Xulane (norelgestromin and EE)Viatris15035Caution above 90 kg; efficacy data strongest below 90 kgNovember 2014
    Twirla (levonorgestrel and EE)Agile Therapeutics12030Contraindicated at or above 30 kg/m2February 2020
    Gwyn Lo (norelgestromin and EE)Viatris22020Contraindicated at or above 30 kg/m2July 28, 2026

    Gwyn Lo delivers the lowest EE dose of any approved contraceptive patch, at 20 mcg/day, which matches the EE dose of the lowest available combined oral contraceptive pills. The increase in norelgestromin (from 150 mcg/day in Xulane to 220 mcg/day in Gwyn Lo) compensates for the lower estrogen by providing stronger progestin-driven ovulation suppression and cycle control.

    The progestin in Gwyn Lo is the same as in Xulane: norelgestromin, which is the active metabolite of norgestimate (the progestin in many combined oral contraceptive pills, including ortho cyclen and related formulations). Norelgestromin has a favorable receptor selectivity profile with relatively high progestogenic activity and low androgenic activity compared with older progestins.


    The Luminous Study: What the Clinical Data Shows

    Design

    Luminous Study (NCT05139121) was a Phase 3, single-arm, open-label, multicenter clinical study evaluating the contraceptive efficacy, safety, and patch adhesion of Gwyn Lo in approximately 1,200 healthy women aged 18 to 40 years across up to 13 28-day cycles of treatment (approximately one year). This design, a single-arm open-label study with Pearl Index as the primary efficacy measure, is the standard approach for contraceptive efficacy trials, where a placebo-controlled design would be unethical.

    The 505(b)(2) regulatory pathway used for Gwyn Lo allowed Viatris to reference the established safety database from Xulane (approved 2014) rather than conducting an entirely new safety program from scratch, while requiring the Luminous Study as the new clinical evidence for the specific Gwyn Lo formulation.

    Four Phase 1 pharmacokinetic studies evaluated drug delivery consistency across application sites (abdomen, buttocks, upper arm) and under conditions of sauna exposure, whirlpool use, treadmill exercise, and cold-water bathing, confirming that delivery was maintained across these real-world exposures.

    Contraceptive efficacy

    The primary efficacy measure in contraceptive trials is the Pearl Index, defined as the number of pregnancies per 100 woman-years of exposure. A lower Pearl Index indicates better contraceptive efficacy. Pearl Index values are not directly comparable across different trials because of differences in study design, population characteristics, and analytical approaches.

    Efficacy endpointGwyn Lo (Luminous Study)
    Pearl Index, women aged 18 to 35 (efficacy-evaluable population)4.14 (95% CI 2.77 to 5.95)
    Specific efficacy in BMI 25 to less than 30 subgroupDemonstrated; no BMI limitation in this range per label

    A Pearl Index of 4.14 in women aged 18 to 35 means approximately 4 pregnancies per 100 women using the patch for a year. This is within the typical range for combined hormonal contraceptives used in real-world studies (Pearl Indices of 3 to 9 in typical use), though it is somewhat higher than the less-than-1 figures reported in perfect-use clinical trials. The Luminous Study’s Pearl Index reflects real-world conditions including patch detachments, missed applications, and typical user behavior rather than controlled ideal use.

    The efficacy results in women with BMI 25 to less than 30 kg/m² were specifically demonstrated and are cited in the label as showing no BMI-based limitation in this range. This is a meaningful statement for clinicians managing patients in the higher end of the BMI below 30 group: the data support efficacy without qualification for this subgroup.

    Patch adhesion

    Patch detachment has historically been one of the practical concerns with transdermal contraceptive systems, as incomplete adhesion can compromise drug delivery and contraceptive efficacy.

    Adhesion endpointGwyn Lo (Luminous Study)
    Complete patch detachment1.3% of 39,790 patches applied
    Delivery maintained under sauna conditionsYes (Phase 1 data)
    Delivery maintained under whirlpool conditionsYes (Phase 1 data)
    Delivery maintained under treadmill exercise conditionsYes (Phase 1 data)
    Delivery maintained under cold-water bathing conditionsYes (Phase 1 data)

    A complete detachment rate of 1.3% across nearly 40,000 patch applications in real conditions is a favorable adhesion profile. The Phase 1 studies confirming maintained delivery during physical activities and water exposures are important for patient counseling: the patch can be worn during exercise and bathing without compromising drug delivery.

    Cycle control

    Unscheduled bleeding and spotting is a common early concern with combined hormonal contraceptive formulations, reflecting the time required for the endometrium to stabilize under the new hormonal regimen.

    Cycle control endpointCycle 1Cycle 13
    Unscheduled bleeding or spotting (any)34.5% of women; mean 3.2 days20.0% of women; mean 2.4 days

    The decline from 34.5% of women experiencing unscheduled bleeding in the first cycle to 20% by the 13th cycle is consistent with the typical pattern observed with combined hormonal contraceptives. This improvement trajectory is useful for patient counseling: early unscheduled bleeding is common and expected to improve substantially over the first several cycles. Clinicians should counsel patients to continue the method through initial cycle irregularity before assessing whether the formulation is appropriate for them.


    The BMI Restriction: The Most Important Label Detail

    The Gwyn Lo indication is restricted to women of childbearing potential with a BMI below 30 kg/m². This is a contraindication, not a caution: women with BMI at or above 30 kg/m² are not approved candidates for Gwyn Lo.

    The basis for this restriction is pharmacokinetic: higher body weight and higher BMI are associated with increased volume of distribution for transdermally delivered hormones, potentially producing lower steady-state plasma concentrations and reducing contraceptive efficacy. Transdermal contraceptive patches, unlike oral pills where dose can be adjusted, deliver a fixed drug flux through a fixed surface area, and this delivery rate does not increase proportionally with body weight.

    The clinical significance: roughly four in ten U.S. women have a BMI in the range the label excludes. This is not a minor restriction. It means Gwyn Lo is not an option for approximately 40% of U.S. women of reproductive age, including a disproportionate share of women from racial and ethnic groups with higher average BMI. Clinicians must confirm BMI below 30 kg/m² before prescribing.

    For comparison, Xulane’s label does not impose a BMI contraindication but notes that efficacy data were strongest in women below approximately 90 kg. Twirla carries the same BMI-30 contraindication as Gwyn Lo. The result is that the weight/BMI restriction in contraceptive patches is a persistent limitation of the format, and clinicians managing patients above BMI 30 should consider combined oral contraceptives or other methods.


    Safety: What Prescribers and Patients Need to Know

    The safety profile of Gwyn Lo is informed both by the Luminous Study and by the reference safety database from Xulane established over a decade of post-marketing experience. The 505(b)(2) regulatory pathway allowed this reference database to support the new product’s safety assessment.

    Boxed warning: cigarette smoking and cardiovascular risks

    All combined hormonal contraceptives carry a boxed warning for the increased risk of serious cardiovascular events from cigarette smoking. Specifically: cigarette smoking increases the risk of serious cardiovascular events from combination oral contraceptive use. This risk increases with age and with the number of cigarettes smoked. Women who are over 35 years of age and smoke should not use combined hormonal contraceptives, including Gwyn Lo.

    Contraindications

    Gwyn Lo shares the class-level contraindications of all combined hormonal contraceptives:

    • History of or current thrombophlebitis or thromboembolic disorders
    • History of or current cerebrovascular disease or coronary artery disease
    • Valvular or rhythm disorders of the heart that may increase risk of blood clots
    • Uncontrolled hypertension or hypertension with vascular disease
    • History of migraine with aura (at any age)
    • Current or past breast cancer
    • Hepatic tumors, benign or malignant, or active liver disease
    • Undiagnosed abnormal uterine bleeding
    • Diabetes with vascular involvement
    • Prolonged immobilization after surgery (relative contraindication requiring evaluation)
    • Hypersensitivity to any component
    • Women over 35 who smoke
    • BMI at or above 30 kg/m² (Gwyn Lo-specific)

    Serious risks

    Venous thromboembolism (VTE): Combined hormonal contraceptives increase the risk of VTE, including deep vein thrombosis and pulmonary embolism. The absolute risk in healthy young women is low, but the relative risk is 3 to 4 times higher than in non-users. The risk is highest in the first year of use and in women with underlying thrombophilias. Discontinue Gwyn Lo in the event of suspected VTE.

    Arterial thromboembolism: Stroke and myocardial infarction risk is increased, particularly in women who smoke, have hypertension, or have other cardiovascular risk factors. The absolute risk in healthy young non-smoking women is very low.

    Liver disease: Combined hormonal contraceptives are associated with rare cases of hepatic adenoma and cholestasis. Liver enzyme elevations can occur; discontinue if jaundice develops.

    Hypertension: Monitor blood pressure regularly. Discontinue if significant hypertension develops.

    Common adverse reactions (occurring in at least 2% of patients in the Luminous Study)

    Common adverse reactions included application site irritation (4.8%), application site erythema (3.7%), application site pruritus (3.7%), intercycle bleeding (3.9%), heavy withdrawal bleeding (2.0%), and nausea (2.0%).

    Application site reactions reflect the transdermal delivery mechanism and are the most distinguishing adverse reaction type compared with oral contraceptives. Most are mild and localized. Rotating application sites (abdomen, buttocks, upper arm) and avoiding applying to irritated or damaged skin reduces these reactions. Patients should not apply Gwyn Lo to the breast or to skin that is red, irritated, or cut.


    How to Use Gwyn Lo: The Application Schedule and Key Instructions

    Gwyn Lo is used in the same 4-week cycle as all currently approved contraceptive patches:

    Week 1: Apply one patch to the skin. The patch is applied to the lower abdomen, buttocks, or upper arm. Avoid the breast.

    Week 2: Remove the first patch and apply a new patch to the same or a different approved site.

    Week 3: Remove the second patch and apply a third patch.

    Week 4 (patch-free week): Remove the third patch. No patch is worn during this week. Withdrawal bleeding typically occurs during this week.

    Cycle restart: Apply a new patch on the same day of the week that the first patch was applied in the previous cycle.

    Starting Gwyn Lo: If starting on Day 1 of the menstrual cycle, contraceptive protection begins immediately. If starting on any other day, use a non-hormonal backup contraceptive method for 7 days.

    Missed or detached patches: If the patch has been on for less than 24 hours and detaches, reapply it or apply a new patch immediately, with no need for backup contraception. If detached for 24 hours or more or if detachment time is unknown, apply a new patch and use backup contraception for 7 days.

    Concurrent medications: Drugs that induce hepatic enzymes (rifampin, certain anticonvulsants, St. John’s wort) can reduce the efficacy of hormonal contraceptives. These interactions apply to Gwyn Lo as they do to other combined hormonal contraceptives.


    Where Gwyn Lo Fits in Contraceptive Counseling

    For clinicians counseling patients about contraceptive options, Gwyn Lo represents a genuinely new option within the patch category: the same weekly application schedule and same progestin molecule as Xulane, with an estrogen dose that matches the low-estrogen standard of modern combined oral contraceptive pills.

    For patients who want the convenience of once-weekly application and prefer it to a daily pill or a longer-acting method, and who have BMI below 30 kg/m², Gwyn Lo is the first patch option that provides 20 mcg/day EE.

    For patients who are specifically concerned about estrogen-related side effects (breast tenderness, nausea, mood changes) or who prefer a lower-estrogen formulation for personal or clinician-guided reasons, and who cannot tolerate or do not want oral contraceptives, Gwyn Lo provides a formulation option that was not previously available in the patch format.

    For patients with BMI at or above 30 kg/m²: Gwyn Lo is contraindicated. The appropriate alternatives include combined oral contraceptives (at appropriate doses; some evidence suggests the efficacy of low-dose oral EE is maintained in women with higher BMI, though this varies by formulation and individual pharmacokinetics), progestin-only methods, intrauterine devices (hormonal or copper), implants, or other long-acting reversible contraceptives.

    The American College of Obstetricians and Gynecologists (ACOG) and the Society of Family Planning maintain current evidence-based guidelines on contraceptive method selection and counseling.


    Sources

    Viatris FDA approval press release: Viatris Receives U.S. FDA Approval for Gwyn Lo, a Once-Weekly Contraceptive Patch. PRNewswire. July 29, 2026.

    BioSpace press release: Viatris Receives U.S. FDA Approval for Gwyn Lo, a Once-Weekly Contraceptive Patch. biospace.com. July 29, 2026.

    Drugs.com approval news: FDA Approves Gwyn Lo (norelgestromin and ethinyl estradiol) Once-Weekly Contraceptive Patch. drugs.com. July 29, 2026.

    Contemporary OB/GYN (Luminous Study NCT number, 505(b)(2) pathway, clinical summary): FDA approves norelgestromin and ethinyl estradiol transdermal patch for contraception. contemporaryobgyn.net. July 2026.

    Medical Daily (BMI restriction 40% exclusion, Xulane dose comparison, Pearl Index, detachment rate, full context): FDA Approves Gwyn Lo, a Once Weekly Contraceptive Patch with a Lower Estrogen Dose. medicaldaily.com. July 2026.

    StockTitan (full adverse reaction table, cycle control data, Pearl Index CI, Phase 1 conditions): Viatris Receives FDA Approval for Once-Weekly Gwyn Lo. stocktitan.net. July 2026.

    Healio (Philippe Martin quote, BMI 25 to 30 specific efficacy language): FDA approves Gwyn Lo hormonal contraceptive patch with low-dose estrogen. healio.com. July 2026.

    MDSpire (Phase 1 pharmacokinetic sites and conditions detail): FDA Approves Low-Estrogen Contraceptive Patch. news.mdspire.com. July 2026.

    Luminous Study trial registration: NCT05139121. ClinicalTrials.gov.

    Combined hormonal contraceptives overview: Contraception: Hormonal Contraceptives. StatPearls. NCBI.

    ACOG contraceptive counseling guidelines: ACOG Practice Bulletin: Combined Hormonal Contraceptives. acog.org.

    Gwyn Lo prescribing information: GWYN LO (norelgestromin and ethinyl estradiol) Transdermal System Prescribing Information. Viatris Inc. 2026.

    Gwyn Lo approval history: Gwyn Lo FDA Approval History. drugs.com.

    Patient resources: Planned Parenthood contraception information | American College of Obstetricians and Gynecologists patient resources | Bedsider (contraceptive method guide) | Viatris Gwyn Lo patient information

    Disclaimer: Health Evidence Digest provides general information about FDA approvals and health research for educational purposes. This content is not a substitute for professional medical advice. Gwyn Lo (norelgestromin and ethinyl estradiol) is contraindicated in women with BMI at or above 30 kg/m² and in women who smoke and are over 35 years of age. Combined hormonal contraceptives carry class-level risks including venous thromboembolism, arterial thromboembolism, and serious cardiovascular events. Contraceptive method selection should be individualized in consultation with a qualified healthcare provider who can evaluate the patient’s complete medical history, BMI, smoking status, contraindications, and personal preferences.
  • Bevacizumab Has Been Injected Into Millions of Eyes for Wet AMD for 20 Years Without FDA Approval for That Use. It Just Got Approved.

    Bevacizumab Has Been Injected Into Millions of Eyes for Wet AMD for 20 Years Without FDA Approval for That Use. It Just Got Approved.

    The essentials: On July 24, 2026, the FDA approved Lytenava (bevacizumab-vikg, Outlook Therapeutics) for the treatment of patients with neovascular (wet) age-related macular degeneration (nAMD). Lytenava is the first and only FDA-approved ophthalmic formulation of bevacizumab in the United States. It is administered as a 1.25 mg intravitreal injection once monthly. What bevacizumab is: a recombinant humanized monoclonal antibody that selectively binds with high affinity to all isoforms of VEGF-A, blocking VEGF from binding to its receptors on endothelial cells, preventing choroidal neovascularization and vascular leakage. Bevacizumab (Avastin) has been FDA-approved for cancer since 2004 and has been compounded and injected off-label into the eyes of patients with wet AMD by retina specialists for approximately 20 years. It has never, until now, been approved for ophthalmic use. What Lytenava is: bevacizumab reformulated specifically for ophthalmic intravitreal use, with a dedicated manufacturing process, sterility testing, FDA-approved labeling, and batch-to-batch consistency requirements. It is not Avastin repackaged in smaller vials. It is a distinct pharmaceutical product developed and validated specifically for intraocular administration. The regulatory story: the path to approval involved multiple CRLs, a Formal Dispute Resolution (FDR) with the FDA’s Office of New Drugs, and a Final Dispute Resolution process that concluded substantial evidence of effectiveness had been established. This is among the more complex regulatory histories for any approved ophthalmic product. The clinical basis: NORSE TWO (NCT03834753), a Phase 3 randomized, controlled, masked trial in 228 adults with nAMD; bevacizumab-vikg 1.25 mg monthly for 12 months versus ranibizumab 0.5 mg monthly for 3 months then every 3 months. Primary endpoint (proportion of patients gaining at least 15 BCVA letters at month 11): 41.7% (bevacizumab-vikg) versus 23% (ranibizumab); p=0.0052. Mean BCVA change: plus 11.2 letters (bevacizumab-vikg) versus plus 5.8 letters (ranibizumab); p=0.0043. NORSE EIGHT (NCT06190093), a confirmatory Phase 3 non-inferiority trial: at week 8, primary non-inferiority endpoint not met (difference minus 2.257 BCVA letters vs minus 3.5 letter NI margin); at week 12, non-inferiority to ranibizumab was demonstrated (BCVA difference minus 1.009 letters). The FDA, following FDR, concluded that NORSE TWO plus confirmatory mechanistic and natural history data established substantial evidence of effectiveness. Lytenava already holds marketing authorization in the European Union and the United Kingdom. Commercial launch in the United States expected before year-end 2026. For readers of prior HED posts: the wet AMD treatment landscape now includes Lytenava alongside ranibizumab (Lucentis, biosimilars), aflibercept (Eylea, Eylea HD, biosimilars), brolucizumab (Beovu), faricimab (Vabysmo), and port delivery system faricimab; for the related condition of geographic atrophy (dry AMD progression), see our earlier post on Izervay (avacincaptad pegol) for the treatment of geographic atrophy secondary to age-related macular degeneration.

    For approximately 20 years, one of the most widely used treatments for wet age-related macular degeneration in the United States has been a drug called bevacizumab, sold under the brand name Avastin, that the FDA approved in 2004 for colorectal cancer.

    This is not a secret. It is not an underground practice. It is an open and well-documented aspect of retinal care that has been sanctioned by professional ophthalmology societies, studied in large head-to-head trials, recommended in clinical guidelines, and reimbursed by Medicare and commercial payers. Retina specialists across the country compounded or had pharmacies compound Avastin into small-volume intravitreal doses and injected it into eyes to block the abnormal blood vessel growth that destroys central vision in wet AMD, because it worked, it cost a fraction of approved alternatives, and there was no FDA-approved bevacizumab formulation for the eye.

    That last fact changed on July 24, 2026.

    Lytenava (bevacizumab-vikg, Outlook Therapeutics) is the first bevacizumab product ever approved by the FDA for ophthalmic use. The molecule is the same. The mechanism is the same. What changed, and what took a winding, four-year regulatory path with multiple rejections and a formal dispute resolution process to establish, is that an ophthalmic formulation developed specifically for intraocular administration, with dedicated manufacturing, sterility validation, FDA-approved labeling, and ongoing regulatory oversight, finally has the regulatory standing to back it.


    What Wet AMD Is and Why VEGF Inhibition Is the Standard of Care

    Age-related macular degeneration (AMD) is the leading cause of irreversible vision loss in adults over 60 in developed countries. The macula, the central portion of the retina responsible for high-resolution central vision, degenerates in two distinct forms.

    Dry AMD, or atrophic AMD, is the more common form (approximately 85 to 90% of AMD cases) and involves the gradual degeneration of photoreceptors and the retinal pigment epithelium. It progresses slowly in most patients but can advance to geographic atrophy, in which large areas of retinal cells are lost permanently. For coverage of the first FDA-approved treatments for geographic atrophy, see our earlier HED post on Izervay (avacincaptad pegol), which covers the complement pathway and the first approved therapy to slow GA progression.

    Wet AMD (neovascular AMD) is the less common but more rapidly vision-threatening form. In wet AMD, abnormal blood vessels grow beneath the retina (choroidal neovascularization, CNV) in response to elevated vascular endothelial growth factor (VEGF) expression. These abnormal vessels are fragile and leaky: they allow fluid to accumulate beneath and within the retina, distorting and ultimately destroying the photoreceptors of the macula. Without treatment, wet AMD can cause severe central vision loss within weeks to months.

    Approximately 200,000 Americans are diagnosed with wet AMD each year. The condition is bilateral in approximately half of patients within five years of the first eye being affected. Its impact on quality of life is profound: the loss of central vision affects reading, driving, facial recognition, and independence, with consequences that extend well beyond visual function to depression, social isolation, and loss of daily living skills.

    The VEGF-A mechanism of wet AMD

    VEGF-A (vascular endothelial growth factor A) is a signaling protein produced by retinal pigment epithelial cells, Müller cells, and other retinal cells under conditions of hypoxia or oxidative stress. VEGF-A binds to VEGFR-1 and VEGFR-2 on the surface of endothelial cells, stimulating their proliferation, migration, and survival, which drives the formation of new blood vessels (angiogenesis). In the retinal context, VEGF-A also increases vascular permeability, contributing to the leakage of fluid and proteins from the abnormal choroidal vessels.

    Anti-VEGF therapy, delivered directly into the vitreous cavity of the eye as an intravitreal injection, blocks VEGF-A from binding to its endothelial cell receptors, suppressing both the growth of new abnormal vessels and the leakage from existing ones. Regular anti-VEGF injections have transformed wet AMD from a condition that reliably caused severe vision loss within one to two years to one that can be managed with sustained vision preservation or improvement for years in most treated patients.


    The Off-Label Bevacizumab Story: 20 Years of Using the Wrong Label

    The off-label use of bevacizumab for wet AMD is one of the most consequential chapters in modern ophthalmic pharmacology, and understanding it is essential context for understanding why Lytenava’s approval matters even to the retina specialists who have been giving bevacizumab intravitreal injections for years.

    Bevacizumab (Avastin, Roche/Genentech) was approved by the FDA in 2004 for first-line colorectal cancer as an intravenous anti-VEGF antibody. Ophthalmologists quickly recognized that its mechanism of blocking all VEGF-A isoforms was precisely what wet AMD treatment needed, and that the molecule was small enough to be injected into the eye in minute doses. By 2005, retinal specialists were compounding Avastin from its cancer-dose vials into small-volume ophthalmic doses and injecting it into eyes. By 2010, bevacizumab was the most commonly used anti-VEGF agent for wet AMD in the United States, despite never having been approved for this use.

    The reasons for this widespread off-label adoption were straightforward:

    Efficacy: Large randomized trials, including the landmark CATT (Comparison of AMD Treatments Trials) study, showed that intravitreal bevacizumab was non-inferior to ranibizumab (the approved anti-VEGF agent at the time) for vision outcomes in wet AMD.

    Cost: Compounded bevacizumab cost approximately $50 to $80 per injection, compared with $2,000 or more per injection for ranibizumab (Lucentis). At a treatment frequency of 8 to 12 injections per year, the cost difference was $15,000 to $20,000 per eye per year versus $200 to $600 per eye per year.

    Access: The cost advantage made bevacizumab accessible to patients who could not afford or were not adequately covered for branded anti-VEGF agents.

    The off-label use was not without controversy. Compounded bevacizumab is not subject to the same manufacturing controls, sterility standards, or batch-to-batch consistency requirements as FDA-approved products. Several clusters of serious ocular infections (endophthalmitis) and inflammation events were reported in association with specific compounding pharmacy lots. The lack of FDA-approved labeling meant that prescribing information, dosing, and safety monitoring were not standardized across practices.

    It is precisely this gap that Lytenava fills. Not by providing a drug that retina specialists could not already access, but by providing one with the standardized manufacturing, validated sterility, FDA-approved labeling, and regulatory oversight that compounded Avastin could never offer.


    How Bevacizumab Works: The Full-Isoform VEGF-A Blockade

    Lytenava’s active molecule, bevacizumab, is a recombinant humanized monoclonal antibody that binds with high affinity to all isoforms of human VEGF-A, including VEGF-A121, VEGF-A165, VEGF-A189, and VEGF-A206. By binding to the VEGF-A molecule itself rather than its receptors, bevacizumab prevents VEGF-A from engaging VEGFR-1 and VEGFR-2 on endothelial cells, blocking both receptor activation pathways simultaneously.

    This pan-isoform VEGF-A blockade distinguishes bevacizumab from some other anti-VEGF agents in the wet AMD arsenal:

    • Ranibizumab (Lucentis): an anti-VEGF-A Fab fragment (lacking the Fc region of full antibody)
    • Aflibercept (Eylea): a VEGF trap that also captures VEGF-B and placental growth factor
    • Brolucizumab (Beovu): a single-chain antibody fragment with high potency and penetration
    • Faricimab (Vabysmo): a bispecific antibody targeting both VEGF-A and angiopoietin-2

    Bevacizumab is the largest molecule among the intravitreal anti-VEGF agents (molecular weight approximately 149 kDa), which has historically been cited as a theoretical reason it might not penetrate the retina as effectively as smaller fragments. Clinical trial evidence has not supported this as a meaningful efficacy limitation in practice.


    The NORSE Clinical Trial Program: What the Data Shows

    The Lytenava approval is based on the NORSE (Non-Inferiority and Ophthalmic Randomized Study of Efficacy and Safety) clinical trial program, specifically NORSE TWO as the primary pivotal trial and NORSE EIGHT as the confirmatory study, together with mechanistic and natural history data.

    NORSE TWO (NCT03834753): The pivotal efficacy trial

    NORSE TWO was a Phase 3, randomized, controlled, parallel-group, masked trial enrolling 228 adults with newly diagnosed wet AMD at 39 sites across the United States. The median patient age was 79 years. Patients were randomized to:

    • Bevacizumab-vikg 1.25 mg intravitreal injection once monthly for 12 months (n=113)
    • Ranibizumab 0.5 mg intravitreal injection monthly for 3 months (days 0, 30, 60) then every 3 months (days 150 and 240) for 12 months (n=115)

    The primary endpoint was the proportion of patients gaining at least 15 ETDRS letters of best corrected visual acuity (BCVA) from baseline at month 11.

    EndpointBevacizumab-vikg (n=113)Ranibizumab (n=115)Result
    Patients gaining at least 15 BCVA letters at month 11 (primary)41.7%23%p=0.0052
    Patients gaining at least 15 BCVA letters at month 11 (per protocol)41%24%p=0.04
    Mean BCVA change from baseline at month 11 (ITT, key secondary)Plus 11.2 lettersPlus 5.8 lettersp=0.0043
    Mean BCVA change from baseline at month 11 (per protocol)Plus 11.1 lettersPlus 7.0 lettersp=0.05
    Any adverse event75.2%73.9%Similar
    Serious adverse events12.4%13.9%Similar
    Ocular serious adverse events0.9%0.0%Numerically higher with bevacizumab-vikg

    Source: NORSE TWO top-line data. Outlook Therapeutics. 2021. NCT03834753.

    The NORSE TWO primary endpoint result, 41.7% of bevacizumab-vikg patients gaining 15 or more letters at month 11 versus 23% of ranibizumab patients (p=0.0052), is statistically significant and clinically meaningful. Gaining 15 or more ETDRS letters (3 lines on a standard eye chart) represents a substantial vision improvement in a disease where the natural history without treatment typically involves significant vision loss. The mean BCVA improvement of 11.2 letters with bevacizumab-vikg versus 5.8 letters with ranibizumab is a similarly substantial difference in the key secondary endpoint.

    An important contextual note on the comparator design: ranibizumab in the control arm was given monthly for the first 3 months and then shifted to quarterly dosing. Ranibizumab given quarterly rather than monthly produces somewhat less vision gain than ranibizumab given monthly, which is how it performs in its own pivotal trials. The NORSE TWO comparator arm was based on a common real-world pro re nata approach rather than the optimal fixed monthly ranibizumab dosing used in MARINA and ANCHOR. This comparison design has been acknowledged as a limitation of interpreting the magnitude of difference between arms.

    NORSE EIGHT (NCT06190093): The confirmatory trial

    NORSE EIGHT was a Phase 3, randomized, controlled, masked, non-inferiority trial required by the FDA as a second adequate and well-controlled trial. Newly diagnosed wet AMD patients were randomized 1:1 to bevacizumab-vikg 1.25 mg or ranibizumab 0.5 mg at weeks 0, 4, and 8. The primary endpoint was mean change in BCVA from baseline to week 8, with a pre-specified non-inferiority margin of minus 3.5 letters.

    NORSE EIGHT did not meet its pre-specified primary non-inferiority endpoint at week 8. The BCVA difference between arms was minus 2.257 letters (95% CI minus 4.044 to minus 0.470), and the lower bound of the confidence interval fell outside the minus 3.5 letter non-inferiority margin (p greater than 0.025).

    However, at week 12 (3 injections per arm), bevacizumab-vikg was non-inferior to ranibizumab: the BCVA difference was minus 1.009 letters (95% CI within the non-inferiority bounds), demonstrating that by the third injection cycle, the drug produced outcomes comparable to ranibizumab.

    The FDA’s Office of New Drugs initially issued a second CRL in December 2025, concluding that the NORSE EIGHT data did not establish a second adequate and well-controlled trial. Outlook Therapeutics pursued a Formal Dispute Resolution (FDR) with the Office of New Drugs. Following the FDR, the OND concluded that the totality of evidence, including NORSE TWO (which met its primary endpoint), the week 12 NORSE EIGHT data, and additional mechanistic and natural history data, collectively established substantial evidence of effectiveness for bevacizumab-vikg in nAMD. The BLA was resubmitted in June 2026 and approved five days before the PDUFA date of July 29, 2026.


    The Regulatory Path: What Multiple CRLs and a Formal Dispute Resolution Mean

    The Lytenava approval arrived after a regulatory journey that spanned several years and included:

    • March 2022: Initial BLA submission
    • May 2022: Voluntary BLA withdrawal to provide additional CMC information
    • August 2022: BLA resubmission
    • August 2023: First CRL, citing CMC issues, pre-approval inspection observations, and lack of substantial evidence of effectiveness
    • NORSE EIGHT trial conducted under FDA-agreed Special Protocol Assessment (SPA)
    • December 2025: Second CRL, citing NORSE EIGHT’s failure to meet primary non-inferiority endpoint at week 8
    • Formal Dispute Resolution with Office of New Drugs
    • June 2026: BLA resubmission following FDR conclusion supporting substantial evidence
    • July 24, 2026: FDA approval

    The FDR process is an administrative mechanism that allows sponsors to escalate a disagreement about scientific or regulatory standards to a higher level within the FDA hierarchy. The process involves submitting a formal written appeal with supporting scientific arguments, followed by FDA internal review and response. The fact that the FDR concluded in favor of approval, overriding the December 2025 CRL, reflects the FDA ultimately agreeing that the combination of NORSE TWO, NORSE EIGHT week 12 data, and mechanistic evidence was sufficient to establish effectiveness.

    For prescribers and patients: this complicated regulatory history does not undermine the drug’s efficacy. NORSE TWO’s primary endpoint was statistically significant and clinically meaningful. The FDA approved the drug because the evidence supports its effectiveness in wet AMD. What the complex path illustrates is the regulatory challenge of applying standard two-trial efficacy requirements to a drug whose mechanism is molecularly identical to a product that has been used effectively in millions of eyes for two decades.


    Where Lytenava Fits in the Current Wet AMD Treatment Landscape

    Wet AMD now has multiple approved intravitreal anti-VEGF agents, each with distinct dosing regimens, administration frequency, and molecular targets. Lytenava joins a landscape that includes:

    DrugCompanyMolecule typeStandard dosingApproval
    Lucentis (ranibizumab) and biosimilarsGenentech/Novartis; multipleAnti-VEGF-A Fab fragmentMonthly or PRNJune 2006
    Eylea (aflibercept 2 mg) and biosimilarsRegeneron; multipleVEGF trapMonthly x 3, then every 2 monthsNovember 2011
    Beovu (brolucizumab)NovartisAnti-VEGF-A scFvMonthly x 3, then every 2 to 3 monthsOctober 2019
    Eylea HD (aflibercept 8 mg)RegeneronVEGF trap (higher dose)Monthly x 3, then every 3 to 4 monthsAugust 2023
    Vabysmo (faricimab)Roche/GenentechAnti-VEGF-A and anti-Ang-2 bispecificMonthly x 4, then up to every 4 monthsJanuary 2022
    Lytenava (bevacizumab-vikg)Outlook TherapeuticsAnti-VEGF-A full antibodyMonthlyJuly 24, 2026

    Lytenava’s distinctive position in this landscape is not superior efficacy over the newest high-dose or extended-interval agents. It is the provision of an FDA-approved, standardized, ophthalmic bevacizumab for the first time, with the regulatory infrastructure that compounded Avastin cannot provide: approved labeling, batch consistency, sterility validation, pharmacovigilance reporting, and liability clarity for prescribers.


    The Compounded Avastin Question: What This Approval Does and Does Not Change

    The most practically complex question surrounding Lytenava’s approval is its relationship to the continued off-label use of compounded Avastin. In purely clinical terms, the molecules are identical. Compounded bevacizumab at 1.25 mg intravitreal is mechanistically the same as Lytenava at 1.25 mg intravitreal.

    What Lytenava provides that compounded Avastin does not:

    Standardized manufacturing: Lytenava is produced under cGMP conditions with lot-to-lot consistency requirements. Compounded bevacizumab is repackaged from cancer-dose vials by pharmacy compounders whose quality standards vary substantially.

    Sterility validation: Lytenava’s sterility is validated to the FDA’s standards for ophthalmic injectables. Sterility failures in compounded bevacizumab have been associated with clusters of endophthalmitis and severe inflammation.

    FDA-approved labeling: Lytenava has prescribing information approved by the FDA for ophthalmic use. Compounded Avastin is used under off-label conditions without a formally approved ophthalmic label.

    Pharmacovigilance: Adverse events with Lytenava will be captured in the FDA’s MedWatch system with mandatory reporting requirements, building the post-marketing safety evidence base.

    Regulatory clarity for prescribers: Prescribing an FDA-approved ophthalmic product is categorically different from the liability considerations of prescribing an off-label compounded cancer drug for an ophthalmic indication.

    Whether Lytenava’s approval translates into a shift in prescribing patterns away from compounded bevacizumab will depend heavily on pricing and coverage. Outlook Therapeutics has not disclosed a list price at the time of writing. If Lytenava is priced significantly above compounded bevacizumab (which costs $50 to $80 per injection), payers who have historically covered compounded bevacizumab may face formulary decisions, and patient out-of-pocket considerations will differ depending on coverage structures. These commercial dynamics will determine whether the approval translates into meaningful uptake.


    Safety: What the NORSE Program Shows

    The safety profile of Lytenava in NORSE TWO was consistent with the established safety experience of intravitreal anti-VEGF injections in wet AMD. The most important safety considerations are those associated with the intravitreal injection procedure and with anti-VEGF pharmacology more broadly.

    Procedure-related risks: All intravitreal injections carry risks of endophthalmitis (serious eye infection), retinal detachment, vitreous hemorrhage, and increased intraocular pressure. These risks are associated with the injection procedure rather than the specific anti-VEGF drug and occur at rates of approximately 1 in 1,000 to 1 in 3,000 injections in experienced hands.

    Anti-VEGF class effects: Systemic absorption of bevacizumab following intravitreal injection is detectable but small. The systemic VEGF-A inhibition at the doses used intravitreally is substantially lower than at cancer-treatment doses. Arterial thromboembolic events (stroke, myocardial infarction) are a class-level concern for all anti-VEGF agents, with higher absolute risk in the older AMD patient population. Patients with recent arterial thromboembolic events should be evaluated carefully before initiating any intravitreal anti-VEGF therapy.

    Ocular adverse events in NORSE TWO: The rate of any adverse event was similar between bevacizumab-vikg (75.2%) and ranibizumab (73.9%) arms. Serious adverse event rates were similar (12.4% versus 13.9%). One ocular serious adverse event was reported in the bevacizumab-vikg arm (0.9%) versus none in the ranibizumab arm. No cases of retinal vasculitis were reported in the NORSE EIGHT trial in either arm.


    What This Means for Retina Specialists, Optometrists, and Patients

    For retina specialists

    Lytenava gives retina specialists who have been using compounded bevacizumab an FDA-approved, standardized option for the same molecular treatment they have been providing for decades. For practices that have moved away from compounded bevacizumab due to quality concerns, liability considerations, or payer requirements, Lytenava provides a path back to the bevacizumab molecule with the regulatory backing those decisions require.

    The NORSE TWO data supporting Lytenava’s efficacy show robust vision gains: 41.7% of patients gaining 15 or more letters at month 11, and a mean BCVA gain of 11.2 letters. These are clinically meaningful outcomes, and the monthly dosing schedule provides a straightforward administration framework.

    The NORSE TWO comparator design (ranibizumab given quarterly after the loading phase rather than monthly) means the NORSE TWO superiority over ranibizumab cannot be directly interpreted as superiority over monthly ranibizumab or over the newer high-dose or extended-interval agents. Clinical comparison to faricimab, high-dose aflibercept, or brolucizumab awaits real-world experience and potential future head-to-head trials.

    For patients with wet AMD

    Lytenava offers the first FDA-approved ophthalmic bevacizumab option. For patients whose retina specialists have been using compounded bevacizumab, this approval introduces an alternative backed by FDA-approved manufacturing standards. For patients who are newly diagnosed with wet AMD, Lytenava joins the range of intravitreal anti-VEGF options to discuss with a retina specialist.

    The monthly dosing schedule (12 injections per year) is more frequent than the extended-interval options now available with faricimab and high-dose aflibercept, which can extend to every 3 to 4 months in patients with an adequate treatment response. Injection frequency is a meaningful quality-of-life consideration for patients who must arrange transportation to and from retina clinic visits.

    For patients with geographic atrophy (dry AMD progression) who have been told there are now treatments available for that stage of the disease, see our earlier post on Izervay (avacincaptad pegol), which covered the first complement-targeting therapy approved to slow GA progression.


    Sources

    Outlook Therapeutics FDA approval press release: Outlook Therapeutics Announces LYTENAVA FDA Approval as the First and Only FDA-Approved Ophthalmic Bevacizumab for the Treatment of Wet AMD. GlobeNewswire. July 24, 2026.

    Drugs.com approval news: FDA Approves Lytenava (bevacizumab-vikg) for the Treatment of Wet Age-Related Macular Degeneration. drugs.com. July 24, 2026.

    Endocrinology Advisor (NORSE TWO comparator design, full trial summary): FDA Approves First Ophthalmic Bevacizumab Formulation for Wet AMD. endocrinologyadvisor.com. July 2026. Full article.

    Optometry Times (FDR regulatory path, EC and MHRA approval, commercial launch timeline): FDA approves Outlook Therapeutics’ Lytenava for wet AMD. optometrytimes.com. July 2026.

    Ophthalmology Times (BLA resubmission context, OND FDR conclusion): Outlook Therapeutics resubmits BLA for bevacizumab-vikg (ONS-5010/LYTENAVA). ophthalmologytimes.com.

    Ophthalmology Advisor (NORSE EIGHT primary endpoint miss, week 12 non-inferiority): Ophthalmic Bevacizumab Denied Approval for Wet AMD Again. ophthalmologyadvisor.com. September 2025.

    AJMC (CRL context, NORSE EIGHT data, exact BCVA numbers): FDA Issues CRL for Bevacizumab Used for Wet AMD. ajmc.com.

    NORSE TWO top-line data (Outlook Therapeutics press release): Outlook Therapeutics Reports Positive Efficacy and Safety Data from Pivotal Phase 3 NORSE TWO Trial. 2021.

    HCPLive NORSE TWO full data (11.2 vs 5.8 BCVA letters, statistical significance by month): Bevacizumab Formulation Significantly Improves wAMD Vision Versus Ranibizumab in NORSE 2. hcplive.com.

    NORSE EIGHT preliminary topline (exact CI, NI margin): Outlook Therapeutics Announces Preliminary Topline Results of NORSE EIGHT Clinical Trial. ir.outlooktherapeutics.com.

    Medscape (EU approval, 41.7% vs 23% primary endpoint in NORSE TWO): EMA Approves Ocular Formulation of Bevacizumab for Macular Degeneration. medscape.com.

    NORSE TWO trial registration: NCT03834753. ClinicalTrials.gov.

    NORSE EIGHT trial registration: NCT06190093. ClinicalTrials.gov.

    CATT trial (off-label bevacizumab non-inferiority to ranibizumab): Martin DF et al. Ranibizumab and Bevacizumab for Neovascular Age-Related Macular Degeneration. NEJM. 2011;364(20):1897-1908.

    AMD overview: Age-Related Macular Degeneration. StatPearls. NCBI.

    Lytenava prescribing information: LYTENAVA (bevacizumab-vikg) Prescribing Information. Outlook Therapeutics. 2026.

    Lytenava approval history: Lytenava FDA Approval History. drugs.com.

    Patient resources: American Academy of Ophthalmology: aao.org | BrightFocus Foundation AMD resources | American Macular Degeneration Foundation | Outlook Therapeutics Lytenava patient support | Prevent Blindness: preventblindness.org

    Disclaimer: Health Evidence Digest provides general information about FDA approvals and health research for educational purposes. This content is not a substitute for professional medical advice. Lytenava (bevacizumab-vikg) requires intravitreal injection by a qualified retina specialist in a clinical setting. Intravitreal injections carry procedural risks including infection, retinal detachment, and increased intraocular pressure. All treatment decisions for wet AMD, including the choice among available anti-VEGF agents, should be made in consultation with a board-certified ophthalmologist or retina specialist experienced in the management of neovascular age-related macular degeneration.
  • Stimulants and Atomoxetine Have Defined ADHD Treatment for Decades. Simtriyo Is the First Drug Approved That Simultaneously Targets All Three Monoamine Neurotransmitter Systems. Here Is Why That Matters.

    Stimulants and Atomoxetine Have Defined ADHD Treatment for Decades. Simtriyo Is the First Drug Approved That Simultaneously Targets All Three Monoamine Neurotransmitter Systems. Here Is Why That Matters.

    The essentials: On July 24, 2026, the FDA approved Simtriyo (centanafadine, Otsuka Pharmaceutical) extended-release capsules for the treatment of ADHD in adults and pediatric patients aged 6 years and older weighing at least 20 kg (approximately 44 pounds). Simtriyo is the first and only approved norepinephrine, dopamine, and serotonin reuptake inhibitor (NDSRI) for any indication. This is a first-in-class mechanism that distinguishes centanafadine from every currently approved ADHD medication. What centanafadine is: an oral once-daily extended-release capsule that inhibits the reuptake of norepinephrine, dopamine, and serotonin simultaneously, increasing the availability of all three monoamines in the brain pathways involved in attention, executive function, and emotional regulation. Stimulants (amphetamines, methylphenidate) primarily increase dopamine and norepinephrine through reuptake inhibition and release. Atomoxetine (Strattera) is a selective norepinephrine reuptake inhibitor. Centanafadine is the first approved agent to add serotonin to the dopamine and norepinephrine target profile. The serotonin component is what differentiates Simtriyo from prior dual-mechanism ADHD drugs and is responsible for the emotional dysregulation and comorbid anxiety benefits observed in clinical data. The clinical basis: four Phase 3 trials across three age groups. Two adult trials (NCT03605680 and NCT03605836; n=859 total adults with ADHD aged 18 to 55): primary endpoint: change from baseline in AISRS (Adult ADHD Investigator Symptom Rating Scale) total score at week 6; both centanafadine 200 mg/day and 400 mg/day showed statistically significant and clinically meaningful improvements versus placebo; onset at week 1 (first post-baseline assessment); sustained through week 6. One adolescent trial (ages 13 to 17): primary endpoint: change from baseline in ADHD-RS-5 total score at week 6; high-dose group met primary endpoint with statistically significant improvement; benefit emerging by week 1. One pediatric trial (ages 6 to 12): primary endpoint: change from baseline in ADHD-RS-5 total score at week 6; high-dose group met primary endpoint with statistically significant improvement; benefit emerging by week 1. Low-dose groups did not reach statistical significance in pediatric or adolescent trials. Notable Phase 3b finding: in 315 adults with ADHD and comorbid anxiety (NCT06973577): AISRS improvement LS mean change minus 18.5 versus minus 12.6 for placebo; treatment difference minus 5.87; p less than 0.0001; HAM-A improvement (anxiety scale) also statistically significant (p=0.02); separation at week 1 maintained through week 8. Regulatory designations: Priority Review. DEA scheduling: Simtriyo is classified as a CNS stimulant and must receive a DEA Schedule classification before commercial launch; this standard process takes up to 3 months. How the DEA classifies it (Schedule II like amphetamines, or a lower schedule) will affect prescribing practices and commercial potential. Boxed warnings: suicidal ideation and behavior in children aged 6 to 12; and abuse, misuse, and addiction (with risk mitigation counseling on storage, disposal, and ongoing patient reassessment). Common adverse reactions: decreased appetite, nausea, rash, fatigue, upper abdominal pain, somnolence. Population: approximately 7 million children and 15.5 million adults in the United States have ADHD.

    Attention-deficit/hyperactivity disorder is the most commonly diagnosed neurodevelopmental condition in childhood and affects a substantial and often undertreated adult population. The FDA approved its first treatments for ADHD over 60 years ago. Since then, the pharmacological toolkit has evolved, but it has stayed within two broad categories: stimulants that drive up dopamine and norepinephrine in the prefrontal cortex, and non-stimulants that work more selectively on norepinephrine alone.

    That framework has worked well for millions of patients. But it has also left clear gaps. The emotional dysregulation that characterizes many ADHD presentations, the hair-trigger frustration, the mood swings that follow a bad day, the inability to manage disappointment proportionally, these are not adequately addressed by dopamine and norepinephrine manipulation alone. The comorbid anxiety that co-occurs with ADHD in an estimated 50% of patients is poorly served by stimulants, which can exacerbate anxiety in many individuals. The 30% of patients who do not respond to or cannot tolerate existing medications continue cycling through options that were designed around the same two-target pharmacology.

    Simtriyo (centanafadine, Otsuka) is the first drug for ADHD that adds serotonin to the target profile. Its three-neurotransmitter mechanism is not just a numbers upgrade. It is a qualitatively different pharmacological approach to a condition that has long been understood to involve more than two neurochemical systems.

    The four Phase 3 trials, conducted across all ages from children to adults, showed consistent, statistically significant improvement in ADHD symptoms. A Phase 3b trial in adults with ADHD and comorbid anxiety showed that centanafadine improved both conditions simultaneously. And the drug demonstrated low abuse and dependence potential in clinical studies, which is a meaningful clinical consideration in a condition where stimulant diversion, misuse, and concerns about controlled substance prescribing remain persistent barriers to treatment access.


    What ADHD Is: The Neurobiology and the Clinical Picture

    Attention-deficit/hyperactivity disorder is a chronic neurodevelopmental disorder characterized by a persistent pattern of inattention, hyperactivity, and impulsivity that is inconsistent with the developmental level of the individual and interferes with functioning across settings. The DSM-5-TR recognizes three presentations: predominantly inattentive, predominantly hyperactive-impulsive, and combined presentation.

    The prevalence of ADHD is substantial. In the United States, approximately 7 million children (approximately 9.4% of children aged 2 to 17 years) have a diagnosed ADHD, and approximately 15.5 million adults are currently estimated to have the condition. These numbers have grown with improved diagnostic criteria and increased awareness of adult ADHD, which was underrecognized for decades as a condition that was assumed to be outgrown in adolescence.

    ADHD is highly heritable (heritability estimates of 70 to 80%) and is associated with dysregulation of the prefrontal cortex and its dopaminergic and noradrenergic inputs, which modulate attention, working memory, response inhibition, and executive function. Functional neuroimaging consistently shows reduced activation in fronto-striatal circuits in individuals with ADHD during tasks requiring sustained attention and executive control.

    What standard neurobiology discussions of ADHD have historically underweighted is the role of serotonin. Serotonergic projections from the dorsal raphe nucleus reach the prefrontal cortex, striatum, and limbic system, where they modulate emotional reactivity, frustration tolerance, and mood stability, precisely the domains in which many individuals with ADHD experience their most functionally limiting symptoms. The emotional dysregulation of ADHD, which some researchers have proposed is a core feature rather than a comorbidity, is substantially serotonin-mediated. This is the gap that centanafadine’s third mechanism targets.


    The ADHD Treatment Landscape and Where Simtriyo Fits

    ADHD pharmacotherapy before Simtriyo was organized around two treatment classes:

    Stimulants (Schedule II controlled substances)

    Stimulants are the most prescribed and most effective first-line treatment for ADHD across all ages. They include:

    Amphetamine-based stimulants: Amphetamine salts (Adderall, Adderall XR), lisdexamfetamine (Vyvanse), dextroamphetamine (Dexedrine). Mechanism: release of dopamine and norepinephrine from presynaptic terminals and inhibition of their reuptake.

    Methylphenidate-based stimulants: Methylphenidate (Ritalin, Concerta, Daytrana, numerous others), dexmethylphenidate (Focalin). Mechanism: primarily reuptake inhibition of dopamine and norepinephrine without significant release.

    Both classes produce robust improvements in attention, hyperactivity, and impulsivity in 70 to 80% of patients. Both are Schedule II controlled substances, requiring specific prescribing procedures, limiting the quantity dispensed, and restricting refills. Both carry abuse potential and are diverted for non-therapeutic use. Some patients cannot tolerate them due to cardiovascular effects, anxiety exacerbation, appetite suppression, or sleep disruption.

    Non-stimulants

    Atomoxetine (Strattera): A selective norepinephrine reuptake inhibitor, approved for ADHD in 2002 for children and adults. Takes 4 to 6 weeks to reach therapeutic effect. Effective for inattention; less effective than stimulants for hyperactivity in many patients. Not a controlled substance. Carries a boxed warning for suicidal ideation in pediatric patients.

    Viloxazine ER (Qelbree): A selective norepinephrine reuptake inhibitor, approved 2021 for children and adolescents, 2022 for adults. Similar profile to atomoxetine but with some evidence of faster onset.

    Alpha-2 adrenergic agonists (guanfacine ER/Intuniv; clonidine ER/Kapvay): Non-stimulant, non-controlled. Particularly useful for hyperactivity, impulsivity, and emotional dysregulation. Less effective for inattention as monotherapy. Often used as adjuncts to stimulants.

    Where Simtriyo sits

    Simtriyo occupies a novel position in this landscape. It is classified as a CNS stimulant (reflecting its dopaminergic and noradrenergic mechanism, which produces the physiological profile of a stimulant) but it is not a traditional amphetamine or methylphenidate. It adds serotonin reuptake inhibition to the dopamine and norepinephrine target profile. And it demonstrated low abuse and dependence potential in clinical studies, which is the basis for Otsuka’s expectation that the DEA may grant it a Schedule III or lower classification rather than the Schedule II designation that applies to amphetamines and methylphenidate.

    The DEA scheduling decision will have significant commercial and clinical implications. A Schedule III or lower classification would allow phone-in and electronic prescriptions with refills (unlike Schedule II, which requires a new written or electronic prescription each month), which is a meaningful practical barrier reduction for patients on long-term ADHD therapy.


    How Centanafadine Works: The Triple Reuptake Mechanism

    Centanafadine inhibits the reuptake transporters for all three monoamine neurotransmitters: the norepinephrine transporter (NET), the dopamine transporter (DAT), and the serotonin transporter (SERT). By blocking these transporters, centanafadine prevents the reabsorption of norepinephrine, dopamine, and serotonin from the synaptic cleft back into the presynaptic neuron, increasing the availability of all three neurotransmitters in the synapse.

    Dopamine transporter (DAT) inhibition: Increases synaptic dopamine in the prefrontal cortex and striatum, improving attention, motivation, and executive function. This is the mechanism shared with methylphenidate, though without the amphetamine-like release component.

    Norepinephrine transporter (NET) inhibition: Increases synaptic norepinephrine in the prefrontal cortex, improving working memory, sustained attention, and response inhibition. This is the mechanism shared with atomoxetine and viloxazine, as well as with amphetamines.

    Serotonin transporter (SERT) inhibition: Increases synaptic serotonin in the prefrontal cortex, limbic system, and striatum. Serotonin modulates emotional reactivity, frustration tolerance, anxiety, and mood stability. This is the mechanism shared with SSRIs and SNRIs, but in a drug designed primarily for ADHD rather than depression or anxiety.

    The combination of all three mechanisms in a single molecule produces a pharmacological effect that simultaneously addresses the attention and executive function deficits of ADHD (via dopamine and norepinephrine) and the emotional dysregulation and comorbid anxiety that frequently accompany them (via serotonin). As Dr. Greg Mattingly noted in a discussion of centanafadine’s mechanism: the serotonin component was shown to help anxiety and mood in people with ADHD, since the drug kind of has an SSRI built in.

    The extended-release capsule formulation delivers the drug over the course of the day, enabling once-daily dosing that maintains therapeutic concentrations through school or work hours without the rebound effects that can accompany immediate-release formulations.


    The Four Phase 3 Trials: What the Data Shows

    The FDA based its approval on the totality of evidence from four Phase 3 trials, spanning adults, adolescents, and children, with consistent findings of statistically significant and clinically meaningful ADHD symptom improvement in the higher-dose groups.

    Adult trials: NCT03605680 and NCT03605836

    Two randomized, double-blind, placebo-controlled Phase 3 trials in 859 adults aged 18 to 55 years with ADHD evaluated centanafadine sustained-release at 200 mg/day or 400 mg/day (administered in divided twice-daily doses) versus placebo over 6 weeks. The primary endpoint was the change from baseline in the AISRS (Adult ADHD Investigator Symptom Rating Scale) total score at week 6.

    Both centanafadine doses (200 mg/day and 400 mg/day) demonstrated statistically significant and clinically meaningful improvement in AISRS total score versus placebo at week 6. Statistical separation from placebo emerged as early as week 1, the first post-baseline assessment time point, and was maintained through the 6-week study period.

    Post-hoc analyses of the 744-patient adult dataset showed improvements in patient-reported executive function, including time management, planning and prioritization, task initiation and completion, and working memory. Improvements in emotional regulation measures, including reduced mood shifts, emotional overactivity, and anger outbursts, were also observed in the same post-hoc analyses.

    Adolescent trial (ages 13 to 17)

    A 6-week, randomized, double-blind, placebo-controlled, fixed-dose trial with weight-based dosing evaluated centanafadine extended-release in adolescents aged 13 to 17 years. The primary endpoint was change from baseline in ADHD-RS-5 (ADHD Rating Scale, fifth edition) total score at week 6. The high-dose group met the primary endpoint with statistically significant improvement versus placebo. Benefit was observed as early as week 1. The low-dose group did not reach statistical significance.

    Pediatric trial (ages 6 to 12)

    A 6-week, randomized, double-blind, placebo-controlled, fixed-dose trial with weight-based dosing evaluated centanafadine extended-release in children aged 6 to 12 years. The primary endpoint was change from baseline in ADHD-RS-5 total score at week 6. The high-dose group met the primary endpoint with statistically significant improvement versus placebo. Benefit was observed as early as week 1. The low-dose group did not reach statistical significance.

    The weight minimum of 20 kg (approximately 44 pounds) for the approved indication reflects both the weight-based dosing approach in the pediatric trials and the pharmacokinetic considerations for centanafadine at the approved doses in the youngest and smallest children.

    Phase 3b trial in ADHD with comorbid anxiety (NCT06973577)

    Beyond the core NDA-supporting trials, Otsuka conducted a Phase 3b study in 315 adults aged 18 to 65 years with ADHD and comorbid anxiety (generalized anxiety disorder and/or social anxiety disorder) to evaluate centanafadine XR 280 mg once daily over 8 weeks.

    EndpointCentanafadine 280 mg (n=approximately 158)Placebo (n=approximately 157)Result
    AISRS change from baseline at week 8 (primary)LS mean minus 18.5LS mean minus 12.6Treatment difference minus 5.87; p less than 0.0001
    HAM-A change from baseline at week 8 (key secondary)LS mean minus 12.5LS mean minus 10.6p=0.02
    Statistical separationWeek 1 (first post-baseline)—Maintained through week 8

    Source: Otsuka Phase 3b press release. June 25, 2026. NCT06973577.

    The simultaneous improvement in both ADHD and anxiety symptoms from a single drug in a population that traditionally requires two medications addresses one of the most clinically significant gaps in ADHD management. The 50% of ADHD patients who have comorbid anxiety are often undertreated for one or both conditions because stimulants can exacerbate anxiety, and adding an SSRI or SNRI to a stimulant regimen increases medication burden and interaction risk. A single drug that addresses both represents a meaningful clinical advance for this population.


    Safety: What the Prescribing Information Covers

    Boxed warnings

    Simtriyo carries two boxed warnings, the FDA’s strongest safety designation:

    Suicidal ideation and behavior in children aged 6 to 12: Centanafadine carries a boxed warning for suicidal ideation and behavior specifically in the 6-to-12 age group. This warning is supported by data from the pediatric trials and reflects the same class-level concern that applies to other ADHD treatments including atomoxetine and viloxazine. Caregivers should monitor children for new or worsening depression, unusual changes in behavior, or suicidal thoughts, particularly early in treatment or after dose changes. Clinical monitoring with frequent follow-up visits is recommended during initial titration in this age group.

    Abuse, misuse, and addiction: As a CNS stimulant with dopaminergic mechanism, centanafadine carries an abuse potential warning. The prescribing information requires counseling patients and caregivers on the risk of abuse and misuse, safe storage (keeping the medication secure and away from others), proper disposal of unused medication, and ongoing reassessment of the patient’s need for the drug at each visit. Centanafadine demonstrated low abuse and dependence potential in clinical studies, which is factored into the pending DEA scheduling decision.

    Common adverse reactions

    The most common adverse reactions reported in ADHD clinical trials, occurring at higher rates than placebo, include: decreased appetite, nausea, rash, fatigue, upper abdominal pain, and somnolence. This adverse reaction profile is broadly consistent with CNS stimulant class effects, though the absence of headache from the list and the presence of rash distinguish the centanafadine profile somewhat from amphetamine formulations.

    Key warnings and precautions

    Cardiovascular monitoring: As with all CNS stimulants, centanafadine may affect heart rate and blood pressure. Cardiovascular status should be evaluated before initiating and monitored during treatment. Centanafadine should be used with caution in patients with pre-existing cardiac conditions, and the prescribing information should be reviewed for specific guidance.

    Psychiatric adverse effects: Beyond the suicidality boxed warning in young children, psychiatric adverse effects including irritability, mood changes, and psychotic or manic episodes have been reported with stimulant class medications. Monitor for emergence of psychiatric symptoms during treatment.

    Growth monitoring in children: As with other stimulant medications, height and weight monitoring is appropriate in pediatric patients on long-term centanafadine therapy.


    The DEA Scheduling Question: A Critical Pre-Commercial Consideration

    Before Simtriyo can be commercially dispensed in the United States, the Drug Enforcement Administration must assign it a controlled substance schedule. This is a standard regulatory process for all drugs with CNS activity and abuse potential, and it can take up to three months from FDA approval.

    The question of which schedule is genuinely important:

    A Schedule II designation (the classification of amphetamines and methylphenidate) would impose: no telephone or electronic prescriptions with refills; patients must obtain a new written or electronic prescription each month; some states impose additional restrictions. This schedule reflects the highest abuse potential among clinical controlled substances.

    A Schedule III, IV, or V designation would allow: prescriptions with refills; electronic transmission; fewer administrative burdens per refill. Schedule III is where buprenorphine for opioid use disorder and many other abusable but non-amphetamine drugs sit.

    Centanafadine’s clinical trial data showing low abuse potential, and its structural and pharmacological differentiation from classical amphetamines, support Otsuka’s expectation that the DEA may assign a lower schedule than amphetamines. Jefferies analysts noted that a lower schedule could give Simtriyo a competitive edge in a crowded ADHD market, and that how the DEA classifies it could determine its commercial potential.


    What This Means for Clinicians and Patients

    For psychiatrists, pediatricians, and primary care providers

    Simtriyo introduces a genuinely new pharmacological option in the ADHD landscape. The triple reuptake mechanism is not a repackaging of existing approaches. It provides a new tool for the following patient profiles:

    Patients with ADHD and comorbid anxiety, who cannot tolerate stimulants or who have had anxiety exacerbated by them. The Phase 3b comorbid anxiety data showing simultaneous improvement in both ADHD and anxiety symptoms from one drug is a clinically important finding.

    Patients with prominent emotional dysregulation, the impulsive anger, frustration intolerance, and mood lability that sit at the intersection of ADHD and emotional disorders and are poorly addressed by traditional stimulants.

    Patients who have not responded to or cannot tolerate existing stimulants or non-stimulants. The additional mechanistic target (serotonin) may produce therapeutic benefit in patients where dopamine/norepinephrine-focused agents have been insufficient.

    Patients or families concerned about controlled substance prescribing, if the DEA assigns a lower schedule than amphetamines.

    The DEA scheduling outcome, expected within approximately three months of the July 24 approval, will be an important milestone that determines the practical prescribing workflow. Most clinicians will want to wait for this clarification before integrating Simtriyo into their prescribing routines.

    For patients and families

    ADHD is a highly individualized condition. Not every patient will respond the same way to any given medication, and finding the right ADHD treatment often involves trial and adjustment of medications, doses, and formulations over time. Simtriyo adds a new first-in-class option to that process, with a mechanism specifically designed to address the emotional and anxiety-related dimensions of ADHD that current medications often leave inadequately treated.

    As Dr. Lenard Adler, director of the adult ADHD program at NYU Langone Health and an investigator on the centanafadine trials, noted: having more therapeutic choices is important because ADHD is a highly individualized condition and treatment decisions should reflect the unique needs of each patient.

    For families navigating a pediatric ADHD diagnosis, the weight requirement of at least 20 kg (approximately 44 pounds) should be confirmed before treatment initiation. The suicidal ideation boxed warning in children aged 6 to 12 is a prescribing information requirement that warrants close communication with the prescribing clinician about monitoring, visit frequency in early treatment, and what behavioral changes to watch for and report.

    The Attention Deficit Disorder Association (ADDA) (add.org) and CHADD (Children and Adults with ADHD) (chadd.org; 1-800-233-4050) maintain current treatment information, prescriber directories, and patient community resources for adults and families navigating ADHD management.


    Sources

    FDA approval announcement: FDA approves centanafadine extended-release capsules for ADHD. FDA.gov. July 24, 2026. Full announcement.

    Otsuka FDA approval press release: Otsuka receives FDA approval for first-in-class SIMTRIYO (centanafadine) for the treatment of attention-deficit hyperactivity disorder (ADHD) in adults and pediatric patients aged 6 years and older. Otsuka. July 24, 2026.

    Drugs.com approval news: FDA Approves Simtriyo (centanafadine) for the Treatment of Attention-Deficit Hyperactivity Disorder (ADHD). drugs.com. July 24, 2026.

    Psychiatric Times (first-in-class NDSRI mechanism, four Phase 3 trials, executive function post-hoc): FDA Approves Centanafadine for ADHD in Children, Adolescents, and Adults. psychiatrictimes.com. July 2026. Full article.

    Psychiatric Times (clinical development path, AISRS primary endpoint, adult and pediatric trial design): Centanafadine’s Route to FDA Review: A Clinical Path of the ADHD Medication. psychiatrictimes.com.

    Managed Healthcare Executive (AISRS week 1 onset, boxed warning detail, DEA scheduling context): FDA approves Simtriyo, the first triple reuptake inhibitor for ADHD. managedhealthcareexecutive.com. July 2026. Full article.

    Fierce Pharma (DEA schedule, commercial analysis, Jefferies note, Dr. Adler quote): FDA approves Otsuka’s first-in-class ADHD drug Simtriyo. fiercepharma.com. July 2026.

    Drug Topics (adult n=744 post-hoc data, pediatric/adolescent high-dose-only result, boxed warnings, week 1 onset): FDA Approves First-in-Class Centanafadine for Treatment of ADHD. drugtopics.com. July 2026.

    ADDitude Magazine (serotonin-SSRI analogy quote, FDA approval context, 280 mg anxiety trial): Centanafadine (Simtriyo) Receives FDA Approval as ADHD Medication. additudemag.com.

    ADDitude clinical path article (Phase 2 dose, pediatric trial design, low-dose negative results, Dr. Wilens investigator reference): Centanafadine: Forthcoming Triple Reuptake Inhibitor ADHD Drug. additudemag.com.

    Otsuka Phase 3b comorbid anxiety press release (exact LS mean data, p-values): Otsuka Announces Positive Phase 3b Results for Centanafadine in Adults with ADHD and Comorbid Anxiety. otsuka-us.com. June 25, 2026.

    Pharmacy Times (AISRS LS mean data, HAM-A secondary endpoint, pediatric trial detail): Centanafadine Demonstrates Statistically Significant, Clinically Relevant Improvements in ADHD Symptoms. pharmacytimes.com.

    Otsuka ASCP 2026 post-hoc press release (executive function, emotional dysregulation domains from n=744): Otsuka Presents New Phase 3 Post Hoc Analyses of Centanafadine at ASCP 2026. otsuka-us.com. May 2026.

    Medscape (first NDSRI approved, prevalence statistics): FDA Approves First NDSRI for ADHD in Adults and Children. medscape.com. July 2026.

    Adult Phase 3 trial registrations: NCT03605680 and NCT03605836. ClinicalTrials.gov.

    Phase 3b comorbid anxiety trial registration: NCT06973577. ClinicalTrials.gov.

    ADHD overview: Attention Deficit Hyperactivity Disorder. StatPearls. NCBI.

    Simtriyo prescribing information: SIMTRIYO (centanafadine) Extended-Release Capsules Prescribing Information. Otsuka. 2026.

    Simtriyo approval history: Simtriyo FDA Approval History. drugs.com.

    Patient resources: CHADD (Children and Adults with ADHD): 1-800-233-4050 | Attention Deficit Disorder Association (ADDA) | Otsuka Simtriyo patient support | CDC ADHD information

    Disclaimer: Health Evidence Digest provides general information about FDA approvals and health research for educational purposes. This content is not a substitute for professional medical advice. Simtriyo (centanafadine) carries a boxed warning for suicidal ideation and behavior in children aged 6 to 12 years, and a boxed warning for abuse, misuse, and addiction. Commercial availability awaits DEA scheduling, which is expected within approximately three months of FDA approval. Treatment decisions for ADHD, including the selection and initiation of any pharmacologic therapy, should be made in close collaboration with a board-certified psychiatrist, pediatrician, or primary care provider experienced in ADHD management, taking into account the individual patient’s clinical profile, comorbidities, and treatment history.
  • ROS1-Positive Lung Cancer Tends to Affect Younger, Non-Smoking Patients. First-Line TKI Therapy Works (Until It Doesn’t). Jideytro Is Now the First Approved Option When It Stops Working.

    ROS1-Positive Lung Cancer Tends to Affect Younger, Non-Smoking Patients. First-Line TKI Therapy Works (Until It Doesn’t). Jideytro Is Now the First Approved Option When It Stops Working.

    The essentials: On July 22, 2026, the FDA approved Jideytro (zidesamtinib, GSK/Nuvalent) for adults with locally advanced or metastatic ROS1-positive non-small cell lung cancer (NSCLC) who have received at least one prior ROS1 tyrosine kinase inhibitor (TKI). The approval came approximately two months ahead of the original PDUFA target action date of September 18, 2026. Jideytro received Breakthrough Therapy Designation and Orphan Drug Designation from the FDA. It is GSK’s first approved lung cancer medicine, developed by Nuvalent Inc., which GSK acquired in 2025. Regulatory context: this is an accelerated approval based on overall response rate and duration of response. What zidesamtinib is: a next-generation, brain-penetrant, ROS1-selective kinase inhibitor engineered to address the two primary failure modes of earlier ROS1 TKIs: acquired resistance mutations (particularly the G2032R solvent front mutation) and inadequate central nervous system (CNS) penetration. Importantly, zidesamtinib avoids inhibition of the structurally related TRK family kinases, which is expected to reduce TRK-related CNS adverse events (cognitive effects, dizziness, ataxia) that limit tolerability of some dual TRK/ROS1 inhibitors. The clinical basis: Phase 1/2 ARROS-1 (NCT05118789), global, multicenter, single-arm, open-label, multi-cohort. Efficacy population: 117 adults with previously treated ROS1-positive NSCLC who had received at least one prior ROS1 TKI. ORR: 44% (95% CI not reported in early sources; durable). Durability: 78% of responders remained in response at 12 months; 62% at 18 months. Subgroup ORR after one prior ROS1 TKI: 51%. Subgroup ORR in G2032R resistance mutation: 54%. Intracranial ORR in patients with measurable brain metastases: 48%; complete intracranial responses: 20%. Tolerability: adverse event-related dose reductions in 10%; discontinuations due to AEs in 2%. The comparison context: the most commonly used first-line ROS1 TKIs are crizotinib (approved, but older generation), entrectinib (Rozlytrek, brain-penetrant dual ROS1/TRK inhibitor), and lorlatinib (approved for ROS1-positive NSCLC). Repotrectinib (Augtyro) and taletrectinib are later-generation options. ARROS-1 included patients who had received lorlatinib, repotrectinib, and taletrectinib as prior therapy, meaning zidesamtinib demonstrated activity even after the most potent existing ROS1 inhibitors had been used. Population context: approximately 50,000 people worldwide are diagnosed with ROS1-positive NSCLC each year; in the United States, 1 to 2% of NSCLC cases carry ROS1 rearrangements. The population is characterized by younger median age, female predominance, and a high proportion of never-smokers.

    Lung cancer is the leading cause of cancer death in the United States. But within lung cancer, the approximately 1 to 2% of patients whose tumors carry a ROS1 gene rearrangement face a distinct clinical experience from most of the other 98 to 99%. They tend to be younger. Many have never smoked. Their tumors are often adenocarcinomas with a predilection for brain metastases. And when they receive a matched ROS1 tyrosine kinase inhibitor, they frequently respond dramatically.

    The problem, as with essentially every other targeted oncology therapy, is that the response eventually ends. Resistance mutations develop. The cancer finds molecular workarounds. Brain metastases progress. And until July 22, 2026, there was no FDA-approved therapy specifically designed for this post-first-line moment.

    Jideytro (zidesamtinib, GSK/Nuvalent) is the first. Approved two months ahead of its PDUFA date, zidesamtinib was engineered from the ground up to address the specific failure modes of earlier ROS1 inhibitors: the resistance mutations that drive progression, the inadequate brain penetration that allows CNS disease to advance, and the off-target TRK inhibition that compromises tolerability of some existing brain-penetrant options.

    The ARROS-1 trial enrolled 117 patients with previously treated ROS1-positive NSCLC, including patients who had already received the newest and most potent ROS1 inhibitors available: lorlatinib, repotrectinib, and taletrectinib. In this heavily pretreated population, zidesamtinib produced a 44% overall response rate, with 78% of responders still in response at one year. In patients with the most common resistance mutation (G2032R), the response rate was 54%. And in patients with brain metastases, nearly half achieved an intracranial response, with one in five achieving complete intracranial clearance.


    What ROS1-Positive NSCLC Is and Who Gets It

    Non-small cell lung cancer accounts for approximately 85% of all lung cancers. Within NSCLC, molecular profiling has identified multiple distinct oncogenic driver subtypes, each with its own therapeutic vulnerabilities and clinical characteristics. EGFR mutations, ALK rearrangements, KRAS mutations, MET amplifications, BRAF mutations, HER2 alterations, and RET fusions each define patient populations for whom specific targeted therapies have transformed the treatment landscape over the past two decades.

    ROS1 gene rearrangements are present in approximately 1 to 2% of NSCLC cases. In the United States, where approximately 250,000 new lung cancer cases are diagnosed annually, this translates to approximately 2,500 to 5,000 new ROS1-positive NSCLC diagnoses per year. Globally, Nuvalent and GSK estimate approximately 50,000 new diagnoses annually.

    The ROS1-positive NSCLC population has several distinguishing epidemiological features. The median age at diagnosis is younger than for other NSCLC subtypes, often in the 40s to 50s. Women are represented at higher rates than in unselected NSCLC. Most patients are never-smokers or former light smokers. The tumors are predominantly adenocarcinoma histology, and brain metastases are common both at initial presentation and during the course of treatment, occurring in 30 to 45% of patients at some point in their disease course.

    These epidemiological features matter clinically. A younger, otherwise healthy patient diagnosed with ROS1-positive NSCLC has a long potential treatment horizon ahead of them, which means the durability of each line of therapy matters more than in a frailer, older patient. It also means that CNS disease management is a central concern across the treatment timeline, not a late-stage complication.


    The ROS1 Kinase and Why It Drives Lung Cancer

    ROS1 (ROS proto-oncogene 1) is a receptor tyrosine kinase expressed in multiple tissues during development but with limited expression in most normal adult tissues. Its natural ligand and physiological signaling functions are not fully characterized. What is known is that chromosomal rearrangements involving ROS1, in which the ROS1 kinase domain fuses to the promoter and partial coding sequence of a partner gene, create constitutively active chimeric oncoproteins that drive uncontrolled cell proliferation.

    Over 20 ROS1 fusion partners have been identified in NSCLC, with CD74-ROS1 being among the most common. All fusion partners produce the same functional consequence: constitutive activation of the ROS1 kinase domain, which signals continuously through the same downstream pathways as the RET and ALK kinases (RAS/MAPK, PI3K/AKT, JAK/STAT), driving tumor growth and survival.

    The structural similarity between ROS1 and ALK (approximately 77% kinase domain amino acid identity) is clinically relevant: several ALK inhibitors, particularly crizotinib and lorlatinib, have significant ROS1 inhibitory activity and are approved for ROS1-positive NSCLC alongside their ALK indications. This shared structural profile was the historical basis for applying ALK inhibitors to ROS1-positive disease, before ROS1-specific and ROS1/RET co-targeting inhibitors were developed.

    The structural similarity between ROS1 and the TRK family (TRKA, TRKB, TRKC) is the source of a distinct tolerability challenge. Earlier-generation brain-penetrant dual inhibitors that cover both ROS1 and TRK kinases (particularly entrectinib and repotrectinib) produce neurological adverse events from CNS TRK inhibition: cognitive effects, dizziness, paresthesias, and ataxia. These toxicities are often dose-limiting and have been a meaningful contributor to treatment discontinuation in clinical practice.


    What Makes Zidesamtinib a Next-Generation Approach

    Zidesamtinib was engineered by Nuvalent with three specific design objectives aimed at the clinical shortcomings of existing ROS1 inhibitors:

    1. Activity against resistance mutations, particularly G2032R

    The most common acquired resistance mutation in ROS1-positive NSCLC is G2032R, a “solvent front” mutation in the ROS1 kinase domain at amino acid position 2032. This mutation alters the geometry of the kinase active site in a way that physically impedes the binding of many first- and second-generation ROS1 inhibitors. G2032R resistance is observed in a significant proportion of patients who progress on crizotinib, entrectinib, and other earlier-generation agents.

    Zidesamtinib was designed with a molecular conformation that maintains potent binding to the G2032R-mutant kinase despite the altered active site geometry. The ARROS-1 data confirmed this pharmacological design goal: patients with G2032R-mutant ROS1-positive NSCLC achieved a 54% ORR, comparable to the overall 44% ORR in the full efficacy population, demonstrating that the drug maintains activity at the resistance mutation that has historically been the most difficult to address.

    2. CNS penetration

    Brain metastases in ROS1-positive NSCLC are common and clinically significant. In patients with CNS disease, the drug’s ability to penetrate the blood-brain barrier determines whether brain metastases are addressed alongside systemic disease or whether the CNS becomes a sanctuary site for disease progression.

    Zidesamtinib was designed with molecular properties optimized for blood-brain barrier penetration: molecular weight, lipophilicity, and efflux transporter (P-glycoprotein) substrate profile were all considered in the drug’s structure. In ARROS-1, among patients with measurable brain metastases, the intracranial ORR was 48%, with complete intracranial responses in 20% of evaluable patients. A 20% complete intracranial response rate in a previously treated population is a strong CNS efficacy signal.

    3. ROS1 selectivity over TRK kinases

    The structural similarity between ROS1 and TRK kinases creates a design challenge: inhibitors that are potent against ROS1 often have collateral TRK inhibitory activity. In the CNS, where TRK signaling supports neuronal function, this TRK inhibition produces the neurological adverse events (cognitive effects, dizziness, ataxia) that characterize some existing brain-penetrant options.

    Zidesamtinib was designed with selectivity favoring ROS1 over TRK kinases, exploiting subtle structural differences in the ROS1 versus TRK active sites. In the ARROS-1 safety data, adverse event-related dose reductions occurred in only 10% of patients and treatment discontinuations due to adverse events in only 2%, a very favorable tolerability profile for an oncology drug in a previously treated population. The avoidance of TRK-related CNS adverse events is a key contributor to this favorable tolerability.


    The ARROS-1 Trial: Full Data

    Design

    ARROS-1 (NCT05118789) is a global, multicenter, Phase 1/2, single-arm, open-label, multi-cohort basket trial evaluating zidesamtinib in patients with advanced ROS1-positive NSCLC and other ROS1-positive solid tumors. The trial is ongoing; the approval was based on a prespecified interim analysis of the previously-treated ROS1-positive NSCLC cohort.

    The efficacy population included 117 adult patients with locally advanced or metastatic ROS1-positive NSCLC who had received at least one prior ROS1 TKI, with or without prior platinum-based chemotherapy or immunotherapy. The cohort was split:

    • 59 patients with one prior ROS1 TKI (less heavily pretreated)
    • 58 patients with two or more prior ROS1 TKIs, including patients who had specifically received lorlatinib, repotrectinib, and/or taletrectinib (the most potent existing options)

    Efficacy results

    EndpointFull efficacy population (n=117)One prior ROS1 TKI (n=59)Two or more prior ROS1 TKIs (n=58)
    Overall response rate44%51%38%
    Responders in response at 6 monthsFavorable (reported consistent with 12- and 18-month data)——
    Responders in response at 12 months78%——
    Responders in response at 18 months62%——
    ORR in G2032R resistance mutation subgroup54%——
    Intracranial ORR (patients with measurable brain metastases)48%——
    Complete intracranial response rate20%——

    Source: ARROS-1 FDA approval summary. FDA.gov. July 22, 2026. AJMC July 2026 clinical data. NCT05118789.

    The 44% ORR in 117 previously treated patients spanning one to more than two prior ROS1 TKIs is a clinically meaningful result for a post-TKI setting where available cytotoxic alternatives typically produce response rates of 15 to 25%. The durability finding, that 78% of responders remained in response at one year, distinguishes zidesamtinib from conventional chemotherapy in this setting and is consistent with the deep, durable responses that characterize well-matched targeted oncology therapies.

    The 51% ORR after one prior ROS1 TKI versus 38% after two or more prior TKIs reflects the expected gradient of response with increasing prior therapy, but the 38% rate in heavily pretreated patients who have already received lorlatinib, repotrectinib, or taletrectinib is itself notable. These are the most potent currently available ROS1 inhibitors, and maintaining a meaningful response rate after them is a meaningful demonstration of zidesamtinib’s differentiated activity.

    The G2032R subgroup ORR of 54% is the most important resistance mutation-specific finding, confirming that the drug’s pharmacological design goal of maintaining activity against the most common ROS1 resistance mutation was achieved in the clinic.

    Dr. Alexander Drilon of Memorial Sloan Kettering Cancer Center, a principal investigator of ARROS-1, noted that despite advances in treatment, resistance mutations, disease progression in the brain, and treatment-related adverse events continue to create challenges for patients, and that the responses observed in ARROS-1, including in heavily pretreated patients, represent meaningful progress for people living with this disease.

    Tolerability

    The tolerability profile from ARROS-1 is among the most favorable observed for any ROS1-targeted therapy in this treatment setting:

    • Adverse event-related dose reductions: 10%
    • Treatment discontinuations due to adverse events: 2%

    The most common adverse reactions occurring in at least 15% of patients in the pooled safety population of 446 patients (which includes the full ARROS-1 treated population beyond the 117-patient efficacy population) were not individually reported in the available press release and will be detailed in the full prescribing information. The generally favorable tolerability reflects the ROS1-selective design and the absence of significant TRK off-target activity.


    The ROS1-Positive NSCLC Treatment Landscape After July 2026

    ROS1-positive NSCLC now has an increasingly complex treatment landscape, with multiple approved options across lines of therapy:

    DrugCompanyROS1 indicationFDA approvalCNS activityResistance coverage
    Xalkori (crizotinib)PfizerROS1-positive NSCLC, first-lineMarch 2016Limited (poor CNS penetration)Limited
    Rozlytrek (entrectinib)Roche/GenentechROS1-positive NSCLC with or without CNS involvementAugust 2019Good (CNS activity)Limited G2032R activity; TRK off-target CNS effects
    Lorlatinib (Lorbrena)PfizerROS1-positive NSCLC, any lineJanuary 2022Good (brain-penetrant)Some resistance mutation coverage; TRK off-target effects
    Augtyro (repotrectinib)BMSROS1-positive NSCLC, any lineNovember 2023GoodImproved G2032R coverage; TRK off-target effects possible
    Taletrectinib (Enhertu)AnHeart/Eli LillyROS1-positive NSCLCApprovedModerate CNS activitySome resistance coverage
    Jideytro (zidesamtinib)GSK/NuvalentROS1-positive NSCLC, after prior ROS1 TKIJuly 22, 2026Good (engineered CNS penetration)G2032R: 54% ORR; TRK-selective sparing

    Zidesamtinib is the only approved agent specifically indicated for the post-prior-ROS1-TKI setting. All other approved ROS1 inhibitors are first-line options or are approved regardless of prior therapy. The approved indication for zidesamtinib is specifically patients who have received at least one prior ROS1 TKI, positioning it as the designated second-line-and-beyond option.

    ARROS-1 is also evaluating zidesamtinib in the first-line setting for patients who have not yet received a ROS1 TKI. If that cohort produces compelling results, a first-line indication could follow, potentially positioning zidesamtinib across the full treatment continuum.


    Safety: What the Prescribing Information Covers

    The full adverse reaction profile will be detailed in the complete prescribing information for Jideytro. Based on available data from ARROS-1 and the pooled safety population of 446 patients:

    Most common adverse reactions (at least 15%): The specific adverse reactions and their frequencies were not individually listed in the available press releases and will be published in the full prescribing information. The favorable overall tolerability profile (dose reductions 10%, discontinuations 2%) indicates that the adverse reaction profile is manageable.

    Warnings and precautions from the prescribing information (based on FDA summary):

    WarningDetailsClinical guidance
    Interstitial lung disease/pneumonitisReported with ROS1 inhibitor class; potentially seriousMonitor for new or worsening respiratory symptoms; hold for suspected pneumonitis; permanently discontinue for confirmed severe events
    HepatotoxicityLiver enzyme elevations observedMonitor liver function tests at baseline and periodically; dose modification for significant elevation
    HypertensionObserved with kinase inhibitorsMonitor blood pressure; antihypertensive therapy as needed
    QT interval prolongationKinase inhibitor class effectECG monitoring in patients with risk factors; electrolyte monitoring and correction
    Hemorrhagic eventsMonitorWithhold for significant hemorrhage
    HypersensitivityReportedManage per prescribing information
    Tumor lysis syndromeRisk in rapidly proliferating tumorsHydration and laboratory monitoring
    Impaired wound healingKinase inhibitor class effectWithhold before and after elective surgery per prescribing information timing guidance
    HypothyroidismMonitor thyroid functionReplace thyroid hormone as clinically indicated
    Embryo-fetal toxicityZidesamtinib can cause fetal harmEffective contraception during treatment and for specified period after last dose

    Required Testing: ROS1 Positivity Must Be Confirmed

    The approved indication requires ROS1-positive disease detected by an FDA-approved test. ROS1 testing should be part of the standard comprehensive molecular profiling that is now recommended for all newly diagnosed advanced NSCLC patients.

    Fluorescence in situ hybridization (FISH) and next-generation sequencing (NGS)-based RNA and DNA panels are the most commonly used ROS1 detection methods. RNA-based sequencing is particularly important for ROS1 fusion detection because the diverse range of fusion partners and intronic breakpoints can be missed by DNA-only sequencing approaches. Major approved NGS platforms including FoundationOne CDx are validated for ROS1 fusion detection.

    At disease progression on a prior ROS1 TKI, molecular re-testing can characterize acquired resistance mechanisms including specific resistance mutations (such as G2032R), which may guide selection among available post-progression options. Liquid biopsy (cell-free DNA) can detect some resistance mutations from blood with a less invasive approach than repeat tissue biopsy and is available through several approved platforms.


    Corporate Context: Nuvalent, GSK, and What Comes Next

    Jideytro is GSK’s first approved lung cancer medicine, and its approval reflects the strategic acquisition of Nuvalent Inc., the biotech that developed zidesamtinib. Nuvalent was founded on the premise that existing targeted kinase inhibitors for thoracic oncology left significant clinical gaps related to CNS penetration, resistance mutations, and off-target tolerability challenges, and that next-generation selective inhibitors engineered to address these specific failure modes could meaningfully improve outcomes.

    GSK’s acquisition of Nuvalent brought not only zidesamtinib but also:

    • Neladalkib (NVL-655): an ALK-selective inhibitor under FDA review with a target action date of November 27, 2026, for ALK-altered NSCLC
    • NVL-330: an investigational HER2-selective inhibitor for HER2-altered NSCLC, in earlier-stage development

    If neladalkib receives approval in November 2026 as expected, GSK will hold two next-generation precision oncology approvals in NSCLC within six months, establishing a meaningful footprint in thoracic oncology that did not exist before the Nuvalent acquisition.

    Janet Freeman-Daily, Co-Founder and President of The ROS1ders, the leading patient advocacy organization for ROS1-positive cancer patients, noted that the ROS1-positive community is deeply invested in advancing care with treatments that are effective and tolerable, and that this approval represents an important advance for people in need.

    For related HED coverage on targeted kinase inhibitor approvals in lung cancer and related precision oncology, see our post on Retevmo (selpercatinib) converting from accelerated to traditional approval for RET fusion-positive solid tumors and our post on Padcev (enfortumab vedotin) receiving its first perioperative MIBC approval regardless of cisplatin eligibility.

    For patients and families navigating a ROS1-positive NSCLC diagnosis, The ROS1ders (theROS1ders.org) is the leading patient-founded organization dedicated specifically to this molecular subtype. The LUNGevity Foundation (lungevity.org; 1-800-LUNG-USA) and the GO2 Foundation for Lung Cancer maintain current resources on molecular testing, treatment options, and clinical trials.


    Sources

    FDA approval announcement: FDA approves zidesamtinib for ROS1-positive non-small cell lung cancer. FDA.gov. July 22, 2026. Full announcement at FDA.gov. Wikipedia

    GSK approval press release: GSK announces the US FDA approval of Jideytro (zidesamtinib) for previously treated ROS1-positive non-small cell lung cancer. PRNewswire. July 22, 2026. Full press release.

    GSK news release (first lung cancer approval, ahead of PDUFA): Jideytro (zidesamtinib) approved in the US for previously treated ROS1-positive non-small cell lung cancer. gsk.com. July 22, 2026.

    Drugs.com approval news: FDA Approves Jideytro (zidesamtinib) for Previously Treated ROS1-Positive Non-Small Cell Lung Cancer. drugs.com. July 22, 2026.

    AJMC (full ORR/DOR breakdown, subgroup data, tolerability rates): FDA Approves Zidesamtinib as New Option for Resistant ROS1+ NSCLC. ajmc.com. July 2026. Full article.

    Oncology News Central (ARROS-1 data, Dr. Drilon quote): FDA Approves Zidesamtinib (Jideytro) for ROS1-Positive Non-Small Cell Lung Cancer. oncologynewscentral.com. July 2026. Full article.

    HMP Global Oncology (ORR 44%, durability at 12 and 18 months, first-line investigation context): FDA Approves Zidesamtinib for Previously Treated ROS1-Positive Non-Small Cell Lung Cancer. hmpgloballearningnetwork.com. July 2026. Full article.

    OncoDaily (GSK first lung cancer approval, neladalkib pipeline, ROS1ders quote, 50,000 global cases): FDA Approves Zidesamtinib (Jideytro) for ROS1-Positive NSCLC. oncodaily.com. July 2026. Full article. Oncology News Central

    Cancer Therapy Advisor (ARROS-1 population detail, trial support summary): FDA Approves Jideytro for Previously Treated ROS1+ NSCLC. cancertherapyadvisor.com. July 2026.

    ARROS-1 trial registration: NCT05118789. ClinicalTrials.gov.

    Jideytro prescribing information (full PI): JIDEYTRO (zidesamtinib) Prescribing Information. Nuvalent/GSK. 2026.

    Jideytro approval history: Jideytro FDA Approval History. drugs.com.

    NSCLC and molecular oncology overview: Non-Small Cell Lung Cancer. StatPearls. NCBI.

    Crizotinib ROS1 approval: FDA approves crizotinib for ROS1-positive NSCLC. FDA.gov.

    Entrectinib ROS1 approval: FDA approves entrectinib for ROS1-positive NSCLC. FDA.gov.

    Patient resources: The ROS1ders: theROS1ders.org | LUNGevity Foundation: 1-800-LUNG-USA | GO2 Foundation for Lung Cancer | Free to Breathe | GSK Jideytro patient support

    Disclaimer: Health Evidence Digest provides general information about FDA approvals and health research for educational purposes. This content is not a substitute for professional medical advice. Jideytro (zidesamtinib) received accelerated approval based on overall response rate and duration of response; continued approval may depend on verification and description of clinical benefit in a confirmatory trial. ROS1-positive status must be confirmed by an FDA-approved test before initiating treatment. Treatment decisions for ROS1-positive NSCLC following prior TKI therapy should be made in close collaboration with a board-certified medical oncologist with expertise in thoracic oncology and molecular-targeted therapy.
  • Retevmo Received Accelerated Approval for RET Fusion-Positive Solid Tumors in 2022 on Response Rate Data. On July 14, 2026, the FDA Confirmed the Clinical Benefit Was Real. Here Is What That Conversion Means.

    Retevmo Received Accelerated Approval for RET Fusion-Positive Solid Tumors in 2022 on Response Rate Data. On July 14, 2026, the FDA Confirmed the Clinical Benefit Was Real. Here Is What That Conversion Means.

    The essentials: On July 14, 2026, the FDA granted traditional (full) approval to Retevmo (selpercatinib, Eli Lilly and Company) for adult and pediatric patients aged 2 years and older with locally advanced or metastatic solid tumors with a RET gene fusion, as detected by an FDA-approved test, that have progressed on or following prior systemic treatment or who have no satisfactory alternative treatment options. This is a regulatory conversion from accelerated to traditional approval. It does not change the indication, the population, or the drug. What changed is the evidentiary threshold: accelerated approval was granted in 2022 based on overall response rate and duration of response as surrogate endpoints. Traditional approval requires confirmatory evidence demonstrating actual clinical benefit. The conversion confirms that the response rates observed in LIBRETTO-001 represent genuine clinical benefit rather than a surrogate that might not translate to meaningful outcomes. Timeline of the tissue-agnostic indication: accelerated approval for adult patients: September 21, 2022. Pediatric extension (accelerated approval for ages 2 and older): May 29, 2024. Traditional (full) approval covering both adults and children aged 2 and older: July 14, 2026. Primary evidence base (tissue-agnostic, non-NSCLC/non-thyroid solid tumors): LIBRETTO-001 (NCT03157128), multicenter, open-label, multi-cohort Phase 1/2 trial. Efficacy analysis set for traditional approval: 75 patients with RET fusion-positive solid tumors other than NSCLC and thyroid cancer. ORR: 47% (95% CI 35% to 59%). Median DOR: 24.5 months (95% CI 11.2 to 49.1). Pediatric evidence: LIBRETTO-121 (NCT03899792), demonstrating responses in congenital infantile fibrosarcoma, spindle cell sarcoma, and RET fusion-positive thyroid cancer. Supported by: established traditional approval data in NSCLC (LIBRETTO-001 NSCLC cohort, original May 2020 approval) and thyroid cancer (traditional approval in medullary thyroid cancer May 2020; RET fusion-positive thyroid cancer traditional approval 2022). What this means for prescribing: no change in the indication, patient eligibility, required RET testing, or dosing. The conversion to traditional approval removes the post-marketing requirement to verify clinical benefit in a confirmatory trial, because that verification has been provided.

    The accelerated approval program is one of the FDA’s most powerful tools for getting effective drugs to patients with serious diseases faster. But it comes with a condition: the drug is approved based on a surrogate endpoint (typically tumor response rate, a measure of whether the tumor shrinks) that is reasonably likely to predict clinical benefit, and continued approval depends on completing a confirmatory trial that demonstrates the actual clinical benefit, whether patients live longer, function better, or have improved quality of life.

    When a drug converts from accelerated to traditional approval, it means the confirmatory standard has been met. The FDA has reviewed the totality of evidence and concluded that the benefit originally inferred from surrogate response data is, in fact, real and established. The drug’s position in therapy is strengthened. The post-marketing obligation to verify is fulfilled. The label revision reflects a regulatory maturation, not a discovery.

    For Retevmo (selpercatinib, Eli Lilly), this conversion arrived on July 14, 2026, for its tissue-agnostic indication covering RET fusion-positive solid tumors other than the NSCLC and thyroid cancer indications that already held full traditional approval. The drug had been treating patients under accelerated approval in this broader solid tumor population since September 2022. The 47% response rate and 24.5-month median duration of response in the LIBRETTO-001 non-NSCLC/non-thyroid cohort, combined with accumulated clinical experience and responses observed in pediatric patients across rare histologies in LIBRETTO-121, provided the confirmatory evidence base the FDA required.

    This post covers what RET gene fusions are and why they matter across cancer types, how selpercatinib works as a selective RET inhibitor, what the complete Retevmo approval history looks like, what the LIBRETTO-001 and LIBRETTO-121 data show, what the regulatory distinction between accelerated and traditional approval means in practice, and what the conversion means for the clinicians and patients who have been using this drug.


    What RET Is and Why a Gene Fusion Changes Everything

    RET (Rearranged during Transfection) is a proto-oncogene encoding a receptor tyrosine kinase expressed in cells derived from the neural crest, including thyroid parafollicular cells (C cells), renal collecting duct cells, and neurons of the enteric nervous system. In normal cells, the RET kinase requires its ligand (glial cell line-derived neurotrophic factor, GDNF, and related proteins) to activate. Ligand binding triggers receptor dimerization and autophosphorylation, initiating downstream signaling through RAS/MAPK, PI3K/AKT/mTOR, and JAK/STAT pathways that regulate cell growth and survival.

    Two types of oncogenic RET alterations drive human cancers: activating point mutations, which constitutively activate RET without requiring ligand binding, and gene fusions, in which chromosomal rearrangements fuse the RET kinase domain to the promoter and partial coding sequence of a partner gene.

    RET gene fusions create chimeric proteins in which the kinase domain of RET is constitutively active, continuously signaling for cell proliferation and survival regardless of ligand availability. The fusion partner determines the specific structural features of the chimeric protein (including its dimerization properties and intracellular localization), but in all cases the downstream consequence is uncontrolled kinase activity driving tumor growth.

    RET fusions are found across multiple tumor types:

    • Non-small cell lung cancer (approximately 1 to 2% of NSCLC): the most common solid tumor context; typically KIF5B-RET or CCDC6-RET fusions
    • Thyroid cancer: highly prevalent in papillary thyroid cancer (approximately 10 to 20% of cases) and relevant in other thyroid malignancies
    • Pancreatic cancer, colorectal cancer, salivary gland tumors, ovarian cancer, breast cancer, and multiple other histologies: lower individual prevalence but collectively encompassing thousands of patients annually

    The tissue-agnostic indication covers this last category: any advanced solid tumor with a confirmed RET gene fusion, regardless of the cancer type in which it occurs, provided the patient has received prior systemic therapy or has no satisfactory alternative treatment options.

    The tissue-agnostic regulatory framework reflects a broader shift in oncology toward molecular characterization of cancer over purely anatomic characterization. A RET fusion-positive pancreatic cancer and a RET fusion-positive NSCLC are different diseases in terms of their tissue of origin, their natural history, and their treatment history, but they share the molecular driver that makes them susceptible to RET inhibition. The shared molecular vulnerability justifies a shared approval across tumor types.


    How Selpercatinib Works: Selective RET Inhibition

    Selpercatinib is an oral, highly selective RET kinase inhibitor designed to potently inhibit both wild-type RET and the common oncogenic RET alterations (fusions and point mutations including RET M918T, the most common mutation in medullary thyroid cancer) while minimizing activity against off-target kinases.

    The selectivity design philosophy distinguishes selpercatinib from earlier multi-kinase inhibitors (such as cabozantinib and vandetanib) that had incidental RET activity alongside activity against VEGFR, MET, and other kinases. Those earlier agents’ off-target activity contributed to high rates of adverse events, particularly cardiovascular and dermatological toxicities, and limited the depth and duration of RET-specific therapeutic benefit achievable in clinical practice.

    Selpercatinib occupies the ATP-binding pocket of the RET kinase domain in a way that locks the enzyme in an inactive conformation. The drug is also designed to address known resistance mutations: at concentrations achievable in the clinic, it maintains activity against several RET mutations that confer resistance to earlier-generation RET inhibitors, including V804M and V804L (the “gatekeeper” mutations).

    The high selectivity translates into an adverse event profile that differs from multi-kinase inhibitors. The most common adverse reactions in LIBRETTO-001 (occurring in 25% or more of the full safety population, n=796) were edema, diarrhea, fatigue, dry mouth, hypertension, abdominal pain, constipation, rash, nausea, and headache. These are largely manageable with dose modification and supportive care, and the rates of severe (grade 3 or 4) events are substantially lower than with the older multi-kinase inhibitors used in RET-altered thyroid cancer.


    Retevmo’s Full Approval History: A Cumulative Story

    Understanding the July 2026 traditional approval requires context for Retevmo’s complete regulatory trajectory. The drug now holds multiple distinct approved indications accumulated over six years.

    IndicationApproval typeDateTrial basis
    RET fusion-positive NSCLC (adults)AcceleratedMay 8, 2020LIBRETTO-001 NSCLC cohort
    RET-mutant medullary thyroid cancer (adults)AcceleratedMay 8, 2020LIBRETTO-001 MTC cohort
    RET fusion-positive thyroid cancer (adults)AcceleratedMay 8, 2020LIBRETTO-001 thyroid cohort
    RET fusion-positive NSCLC (adults)Traditional (full)March 25, 2022LIBRETTO-431 Phase 3 versus chemo
    RET-mutant MTC and RET fusion-positive thyroid cancer (adults and pediatric ages 12 and older)Traditional (full)October 19, 2022LIBRETTO-001 confirmed data
    RET fusion-positive solid tumors, all types (adults)AcceleratedSeptember 21, 2022LIBRETTO-001 non-NSCLC/non-thyroid ORR/DOR
    RET-mutant MTC and RET fusion-positive thyroid cancer (pediatric ages 2 and older)AcceleratedMay 29, 2024LIBRETTO-121 pediatric data
    RET fusion-positive solid tumors, all types (adults and pediatric ages 2 and older)Traditional (full)July 14, 2026LIBRETTO-001 confirmed; LIBRETTO-121 supported

    The July 2026 action completes the regulatory maturation of the tissue-agnostic indication and extends full traditional approval to the pediatric population (ages 2 and older) that had previously held only accelerated approval.


    The Evidence Base: LIBRETTO-001 and LIBRETTO-121

    LIBRETTO-001: The backbone of the tissue-agnostic indication

    LIBRETTO-001 (NCT03157128) is an international, non-randomized, open-label, multi-cohort Phase 1/2 basket trial evaluating selpercatinib across all RET-altered solid tumors. The trial enrolled both RET fusion-positive and RET-mutant cancers across multiple tumor types and is the primary evidence source for most of Retevmo’s approved indications.

    The efficacy analysis supporting the traditional approval conversion for the tissue-agnostic indication focused on 75 patients with RET fusion-positive solid tumors excluding NSCLC and thyroid cancer (the tumor types with separate, fully established approval pathways). This population included cancers of the pancreas, colon, rectum, salivary gland, ovary, breast, and other sites, all unified by the presence of a confirmed RET gene fusion.

    Efficacy endpointResult
    Population (non-NSCLC, non-thyroid RET fusion-positive solid tumors)n=75
    Overall response rate (ORR)47% (95% CI 35% to 59%)
    Complete response rateIncluded in the 47% ORR
    Median duration of response (DOR)24.5 months (95% CI 11.2 to 49.1)

    Source: LIBRETTO-001. NCT03157128. FDA traditional approval summary July 14, 2026.

    A 47% ORR and 24.5-month median DOR in a pan-tumor, pretreated population with diverse histologies is a clinically meaningful and durable response. The median DOR of nearly 2 years means that among the patients who responded, approximately half maintained that response beyond 24 months. In the context of heavily pretreated advanced solid tumors, which typically show short-duration responses to available cytotoxic chemotherapy, this durability distinguishes the targeted RET inhibitor approach from standard cytotoxic alternatives.

    The supporting efficacy evidence from the NSCLC and thyroid cancer cohorts in LIBRETTO-001, both of which carry traditional approval, provides additional confirmation that selpercatinib’s anti-tumor activity is a real, consistent pharmacological phenomenon rather than a statistical artifact of small-cohort data.

    LIBRETTO-121: The pediatric evidence base

    LIBRETTO-121 (NCT03899792) is a multicenter, open-label, multi-cohort trial evaluating selpercatinib specifically in pediatric and young adult patients with RET-altered cancers. The trial evaluated patients with locally advanced refractory RET fusion-positive solid tumors who were unresponsive to available therapies or had no standard systemic curative therapy.

    The evidence from LIBRETTO-121 supporting the July 2026 traditional approval included:

    • One patient with congenital infantile fibrosarcoma: response observed
    • One patient with spindle cell sarcoma: response observed
    • Patients with RET fusion-positive thyroid cancer: responses observed

    Congenital infantile fibrosarcoma and spindle cell sarcoma are rare pediatric tumors that carry ETV6-NTRK3 or other fusions in many cases, but the subset with RET fusions represents an ultra-rare population with very limited treatment options. A documented response in even a single patient with a rare pediatric sarcoma histology is clinically meaningful in a disease where treatment options are severely constrained.

    The pediatric dosing framework for selpercatinib in LIBRETTO-121 includes weight-based dosing for children under 50 kg and adult dosing (160 mg twice daily) for patients at or above 50 kg or aged 12 and older meeting weight criteria. The prescribing information specifies dosing tables by weight for the pediatric population.


    The Accelerated to Traditional Approval Conversion: What It Means and Why It Matters

    Accelerated approval is a regulatory pathway created to make drugs available earlier for serious conditions with unmet medical need, based on surrogate endpoints that are “reasonably likely to predict” clinical benefit. Response rate is the most commonly used surrogate: if a tumor shrinks, the inference is that the patient will likely benefit clinically, even if survival data are not yet mature.

    The limitation of accelerated approval is exactly that: it is based on an inference. A tumor can shrink and still not provide meaningful clinical benefit if the response is short, if the toxicity is prohibitive, or if the shrinkage does not translate into longer survival or better function. These are the cases where confirmatory trials sometimes reveal that the surrogate did not predict the expected clinical benefit, and the drug’s accelerated approval is subsequently withdrawn.

    The conversion to traditional approval is the opposite event: it means the FDA has reviewed additional evidence demonstrating that the drug delivers genuine clinical benefit. For selpercatinib, the combination of the extended response durations observed in LIBRETTO-001 (median DOR of 24.5 months across the diverse non-NSCLC/non-thyroid cohort), the fully established traditional approval in NSCLC and thyroid cancer, and the pediatric response data in LIBRETTO-121 together provided the evidentiary confirmation required.

    The practical implications of the conversion for patients and prescribers:

    The indication does not change. The patient population, dosing, and required testing are identical before and after the conversion.

    The regulatory confidence in the drug’s benefit is strengthened. Traditional approval removes the qualifier from the label indicating that continued approval may depend on a confirmatory trial. The clinical benefit is established.

    The post-marketing verification requirement is fulfilled. Under accelerated approval, sponsors are legally required to conduct and submit confirmatory trial data. That obligation is discharged when traditional approval is granted.

    Payer coverage is sometimes affected. Some commercial payers treat accelerated-approval drugs with greater scrutiny in prior authorization decisions, viewing them as having a higher evidentiary uncertainty. Traditional approval can support broader formulary access and simpler authorization pathways in some systems.


    RET Testing: A Required Prerequisite

    The tissue-agnostic indication for Retevmo requires RET gene fusion detection using an FDA-approved test. This testing requirement is embedded in the indication language: “locally advanced or metastatic solid tumors with a RET gene fusion, as detected by an FDA-approved test.”

    For oncologists managing patients with advanced solid tumors: comprehensive genomic profiling (CGP) panels, which assess for RET fusions alongside hundreds of other clinically relevant alterations in a single assay, are the most efficient approach to RET testing in practice. Major approved CGP tests include Foundation Medicine’s FoundationOne CDx and Liquid CDx platforms, MSKCC’s MSK-IMPACT, and others. RNA-based sequencing is particularly important for RET fusion detection because DNA-based sequencing may miss some intronic fusion breakpoints; laboratories offering solid tumor profiling should ideally include RNA-based detection for fusion genes.

    Patients whose tumors have not previously undergone molecular profiling and who are progressing on first-line therapy should be considered for testing at the earliest opportunity, because tissue requirements for a repeat biopsy may limit testing access later in the disease course. Cell-free DNA (liquid biopsy) is also available and can detect RET fusions from a blood draw, though with lower sensitivity than tissue testing for some rare fusion partners.


    Safety: What the Prescribing Information Covers

    The safety profile of selpercatinib from LIBRETTO-001 is well-characterized across the approximately 796-patient full safety population with advanced solid tumors. The July 14, 2026 conversion does not change the safety profile or the warnings; it confirms the established benefit-risk assessment.

    Most common adverse reactions (25% or more in the full safety population): edema, diarrhea, fatigue, dry mouth, hypertension, abdominal pain, constipation, rash, nausea, and headache.

    Most common grade 3 or 4 laboratory abnormalities (5% or more): decreased lymphocytes, increased ALT, increased AST, decreased sodium, and decreased calcium.

    Key warnings and precautions:

    WarningRate/detailManagement
    HepatotoxicityALT or AST elevation; monitor before initiating and periodicallyMonitor liver enzymes; dose interrupt or discontinue for significant elevation
    ILD/pneumonitisPotentially fatalMonitor for pulmonary symptoms; hold for grade 2; permanently discontinue for grade 3 or 4
    HypertensionGrade 3 or higher in approximately 20%Monitor blood pressure; antihypertensive medications as needed; dose modification for uncontrolled hypertension
    QT interval prolongationGrade 3 or higher in approximately 5%ECG at baseline and periodically; electrolyte monitoring and replacement
    Hemorrhagic eventsMonitorWithhold for grade 3 or higher bleeding; discuss with prescribing information for resumption
    HypersensitivityReportedManage per prescribing information; may require corticosteroids
    Tumor lysis syndromeParticularly in rapidly proliferating tumorsMonitor laboratory values; hydration
    Impaired wound healingWithhold before and after surgerySee prescribing information for timing guidance around elective procedures
    HypothyroidismMonitor TSH periodicallyReplace thyroid hormone as clinically indicated
    Embryo-fetal toxicitySelpercatinib can cause fetal harmEffective contraception during treatment and for specified time after last dose
    Slipped capital femoral epiphysis (pediatric)Monitor for hip or knee pain in pediatric patientsA specific pediatric warning added with the 2024 pediatric expansion

    The pediatric-specific warning for slipped capital femoral epiphysis (SCFE), a disruption of the growth plate at the femoral head, was added to the prescribing information with the 2024 pediatric expansion and remains in place with the 2026 traditional approval. Pediatric patients receiving selpercatinib should be monitored for hip or knee pain, and any such complaint should prompt orthopedic evaluation.


    Retevmo’s Current Complete Indication Coverage

    After July 14, 2026, Retevmo (selpercatinib) holds the following approved indications:

    IndicationPopulationApproval status
    RET fusion-positive NSCLCAdultsTraditional (full)
    RET-mutant medullary thyroid cancerAdults and pediatric ages 2 and olderTraditional (full)
    RET fusion-positive thyroid cancerAdults and pediatric ages 2 and olderTraditional (full)
    RET fusion-positive solid tumors (any type)Adults and pediatric ages 2 and olderTraditional (full), July 14, 2026

    All indications now hold traditional approval. Retevmo has no remaining accelerated approval indications. The regulatory maturation of the drug is complete across its full clinical scope.


    What This Means for Oncologists and Patients

    For oncologists managing patients with advanced solid tumors

    The practical implication for clinical practice is modest because the indication, the patient population, and the drug are unchanged. What the traditional approval provides is regulatory confirmation of clinical benefit, which strengthens the position of selpercatinib in treatment guidelines and may support broader formulary access in payer systems that treat accelerated-approval drugs differently.

    For patients currently receiving selpercatinib under the prior accelerated approval: nothing changes about their treatment. The drug they are taking is the same; the benefit they are receiving is now confirmed rather than inferred.

    For oncologists identifying new patients with RET fusion-positive solid tumors (outside of NSCLC and thyroid cancer): the traditional approval removes any label-language qualifier about provisional status. The evidence base is established. The indication is full.

    The response rate of 47% and median DOR of 24.5 months represent the expected clinical outcomes in a heavily pretreated pan-tumor population. Individual patient outcomes will vary based on tumor histology, prior treatment burden, performance status, and specific RET fusion partner, but these numbers provide a reasonable framework for pre-treatment counseling.

    For patients with rare RET fusion-positive cancers

    The tissue-agnostic nature of this indication remains one of its most important features for patients. A patient with RET fusion-positive pancreatic cancer or colon cancer does not have a separate lung cancer drug or a thyroid cancer drug being offered off-label. They have a drug approved specifically for their cancer type, based on the molecular driver their tumor carries, regardless of where in the body the tumor originated. That clarity matters for insurance coverage, for informed consent, and for the patient’s understanding of why this specific drug was recommended.

    The full traditional approval now reinforces that position. For patients who were told in 2022 or 2023 that they were receiving a drug under accelerated approval pending confirmatory data, the July 2026 update means that confirmatory standard has been met. The benefit is established.

    For related HED coverage on precision oncology and targeted kinase inhibitor approvals, see our post on Revtorpyk (gedatolisib) becoming the first approved targeted therapy for PIK3CA wild-type HR+/HER2- breast cancer and our post on daraxonrasib (RMC-6236) generating a standing ovation at ASCO 2026 for its Phase 3 results in KRAS-driven pancreatic cancer.


    Sources

    FDA traditional approval announcement: FDA grants traditional approval to selpercatinib for locally advanced or metastatic RET fusion-positive solid tumors. FDA.gov. July 14, 2026. Full announcement at FDA.gov. Eli Lilly and Company

    CancerNetwork coverage (trial support overview): FDA Traditionally Approves Selpercatinib in RET+ Solid Tumors. cancernetwork.com. July 2026.

    OncLive (ORR 47% and DOR 24.5 months data): FDA Awards Traditional Approval to Selpercatinib for RET+ Advanced Solid Tumors. onclive.com. July 2026.

    Healio (n=75 population, LIBRETTO-001 cohort detail): FDA grants traditional approval to Retevmo for RET fusion-positive solid tumors. healio.com. July 2026.

    CURE (patient-focused conversion explanation, LIBRETTO-121 histologies): FDA Grants Traditional Approval to Retevmo for RET Fusion-Positive Solid Tumors. curetoday.com. July 2026.

    ASCO Post (complete indication language, LIBRETTO-121 context): FDA Grants Traditional Approval to Selpercatinib for Locally Advanced or Metastatic RET Fusion-Positive Solid Tumors. ascopost.com. July 2026.

    Oncology Nursing News (regulatory conversion context): FDA Grants Traditional Approval to Selpercatinib for RET-Fusion Solid Tumors. oncnursingnews.com. July 2026.

    Lilly accelerated approval press release (September 2022): FDA Approves Lilly’s Retevmo (selpercatinib), the First and Only RET Inhibitor for Adults with Advanced or Metastatic Solid Tumors with a RET Gene Fusion. Eli Lilly. September 21, 2022.

    LIBRETTO-001 FDA review article (PMC): FDA accelerated approval summary for selpercatinib RET fusion-positive solid tumors (2022). PMC10524590.

    LIBRETTO-001 trial registration: NCT03157128. ClinicalTrials.gov.

    LIBRETTO-121 trial registration: NCT03899792. ClinicalTrials.gov.

    Drugs.com approval news: FDA Grants Traditional Approval to Retevmo (selpercatinib) for Locally Advanced or Metastatic RET Fusion-Positive Solid Tumors. drugs.com. July 14, 2026.

    Retevmo prescribing information: RETEVMO (selpercatinib) Prescribing Information. Eli Lilly and Company. 2026.

    Retevmo approval history: Retevmo FDA Approval History. drugs.com.

    Patient resources: LUNGevity Foundation: RET+ resources | Thyroid Cancer Alliance | RET Research Foundation | ClinicalTrials.gov: search selpercatinib | Lilly Cares patient support for Retevmo

    Disclaimer: Health Evidence Digest provides general information about FDA approvals and health research for educational purposes. This content is not a substitute for professional medical advice. The July 14, 2026 traditional approval of Retevmo (selpercatinib) for RET fusion-positive solid tumors reflects a regulatory conversion from accelerated to traditional approval; the indication, population, dosing, and required testing are unchanged. RET gene fusion testing using an FDA-approved test is required before initiating treatment. Decisions about selpercatinib therapy should be made in close collaboration with a board-certified medical oncologist experienced in molecular-targeted therapy and familiar with the tumor type in question.

  • Leqembi Has Changed What Is Possible in Early Alzheimer’s Disease. Until Now, Every Dose Required a Clinic Visit and an IV Line. That Changed on July 13, 2026.

    Leqembi Has Changed What Is Possible in Early Alzheimer’s Disease. Until Now, Every Dose Required a Clinic Visit and an IV Line. That Changed on July 13, 2026.

    The essentials: On July 13, 2026, the FDA approved a supplemental Biologics License Application for Leqembi Iqlik (lecanemab-irmb, Eisai and Biogen) as a once-weekly subcutaneous injection for treatment initiation in adults with early Alzheimer’s disease. This is the world’s first anti-amyloid therapy that can be started at home, without a clinic visit, and administered by the patient or a caregiver in approximately 15 seconds per injection. What this approval adds: Leqembi Iqlik was previously approved (August 2025) for subcutaneous maintenance dosing following 18 months of IV treatment. The July 13, 2026 approval extends SC use to the initiation phase, meaning the entire treatment course can now be managed subcutaneously from the first dose. No IV infusion is required at any point for patients who choose the SC formulation. The approved initiation regimen: 500 mg subcutaneous once weekly, delivered as two simultaneous 250 mg injections, each administered in approximately 15 seconds, via a pre-filled autoinjector. After completing the initiation phase (18 months of SC or IV dosing), patients transition to maintenance dosing at 360 mg SC once weekly. The evidentiary basis: sub-studies within the Phase 3 Clarity AD long-term extension (LTE) demonstrating that once-weekly SC administration achieves pharmacokinetic exposure equivalent to the approved biweekly IV regimen, with similar clinical and biomarker (amyloid removal) benefits. ARIA-E (amyloid-related imaging abnormalities, edema type) rates with SC administration are expected to be comparable to IV. The underlying efficacy data: the Phase 3 Clarity AD trial (n=1,795, 18 months, double-blind, randomized, placebo-controlled) showed 27% slowing of clinical decline on CDR-SB versus placebo (treatment difference minus 0.45; 95% CI minus 0.67 to minus 0.23; p=0.00005). All key secondary endpoints met. Four-year open-label extension data shows the benefit deepening over time: CDR-SB benefit versus ADNI-matched controls grew from 0.52 points at 18 months to 1.01 at 36 months and 1.75 at 48 months. Real-world data from the LEADER study (AAIC 2026, July 2026): over 75% of early AD patients remained stable and nearly 7% improved over an average of 17 months of lecanemab treatment in clinical practice. U.S. commercial launch of Leqembi Iqlik as initiation dose: planned for late August 2026. Leqembi is currently approved in 53 countries. Leqembi Iqlik is the first and only anti-amyloid treatment in the world to offer at-home dosing from the beginning of treatment through maintenance.

    Alzheimer’s disease affects approximately 7 million Americans today and is projected to affect nearly 13 million by 2050. It is the only disease in the top 10 causes of death in the United States without a therapy that prevents it, stops it, or reverses it. The disease modifies everything, the person living with it, the family surrounding them, the daily structure of home life, the ability to work, to drive, to recognize the people who matter most.

    The January 2023 accelerated approval and July 2023 full traditional approval of Leqembi (lecanemab-irmb, Eisai/Biogen) represented the first time a drug had demonstrated statistically significant, clinically meaningful slowing of Alzheimer’s disease progression in a Phase 3 trial with sufficient safety profile to support full approval. The Phase 3 Clarity AD data were not a marginal finding: 27% slowing of clinical decline measured by the CDR-SB, beginning as early as 6 months of treatment, growing over time, sustained through four years of open-label extension. This was not the drug that reverses Alzheimer’s disease. But it was proof, for the first time in the disease’s clinical history, that the underlying biological process could be meaningfully slowed.

    What it was not, until now, was accessible in the most practical sense. Every lecanemab dose required a biweekly trip to an infusion center. For a patient with mild cognitive impairment or mild Alzheimer’s dementia, managing regular clinic visits was manageable. Over time, as disease progresses, or for patients in rural areas, or for those whose caregiver situation makes regular infusion center visits logistically difficult, this requirement becomes an accumulating burden. And the infusion reactions that occurred in 26% of IV-treated patients in Clarity AD added another layer of clinical management to every visit.

    Leqembi Iqlik’s July 13, 2026 approval as an initiation-dose subcutaneous treatment removes that burden from the first dose. A 15-second subcutaneous injection at home replaces a biweekly infusion clinic visit. For patients who want it, and for whom home administration is appropriate, the treatment that slows Alzheimer’s disease is now something that can happen at the kitchen table rather than in a healthcare facility. That is not a trivial change.


    What Alzheimer’s Disease Is and Why the Disease Stage Matters

    Alzheimer’s disease is a progressive neurodegenerative disease and the most common cause of dementia. It is characterized pathologically by the accumulation of amyloid beta plaques and neurofibrillary tangles of tau protein in the brain, beginning years or decades before clinical symptoms appear, and progressing through stages of cognitive impairment that ultimately result in the inability to perform basic daily functions.

    The disease is understood to follow a continuum:

    Preclinical Alzheimer’s disease: Amyloid accumulation detectable by PET scan or CSF analysis but no cognitive symptoms. This is the earliest detectable stage, before the disease has clinically manifested.

    Mild cognitive impairment (MCI) due to Alzheimer’s disease: Subtle but measurable cognitive changes, below the threshold for dementia, with confirmed amyloid pathology. Activities of daily living are largely preserved. Patients may notice memory lapses, word-finding difficulties, or difficulty with complex planning, but remain independent.

    Mild Alzheimer’s dementia: Cognitive impairment that interferes with daily functioning, though patients retain significant independence. This is the stage at which symptoms are first clearly apparent to family members and often when a diagnosis is formally established.

    Leqembi (and Leqembi Iqlik) is approved for early Alzheimer’s disease, which encompasses both MCI due to Alzheimer’s and mild Alzheimer’s dementia. The approval requires confirmation of amyloid pathology before initiating treatment, either by amyloid PET scan or CSF analysis showing abnormal amyloid levels. This confirmation is not optional: lecanemab’s mechanism of action is directed at amyloid, and the clinical evidence was generated exclusively in amyloid-confirmed patients. Treating without confirmed amyloid would be treating without evidence that the drug’s target is present.

    The restriction to early stages is biologically appropriate and clinically important. The disease-modifying mechanism of lecanemab addresses the amyloid pathology that drives neurodegeneration. By the time a patient reaches moderate or severe dementia, the downstream consequences of amyloid accumulation, significant neuronal loss, synapse loss, and tau tangle burden, are already extensive. Clearing amyloid at that stage provides less opportunity for clinical benefit. The window for anti-amyloid therapy is earlier, before irreversible neuronal damage has accumulated.


    The Amyloid Hypothesis and How Lecanemab Works

    Amyloid beta is a small peptide generated by cleavage of the amyloid precursor protein (APP) by beta-secretase and gamma-secretase enzymes. In normal aging, amyloid beta is produced and cleared in balance. In Alzheimer’s disease, this balance is disrupted: amyloid beta accumulates, misfolds, and aggregates into progressively larger and more toxic forms, from monomers to oligomers to protofibrils and eventually to the insoluble fibrillar plaques that appear in the brains of patients with the disease.

    The amyloid cascade hypothesis holds that this accumulation is not merely a biomarker of Alzheimer’s disease but a key early driver of the downstream pathological cascade, including tau phosphorylation, neuroinflammation, synaptic dysfunction, and neuronal death. The hypothesis has generated decades of scientific debate, and the failures of numerous amyloid-targeting drugs in clinical trials have repeatedly raised questions about its validity. The Clarity AD results, showing that clearing amyloid produces measurable slowing of clinical decline, provide the strongest clinical evidence to date that the hypothesis is at least partially correct in the early disease setting.

    Lecanemab is a humanized IgG1 monoclonal antibody that targets aggregated forms of amyloid beta, with particularly high affinity for soluble amyloid protofibrils, which are thought to be among the most neurotoxic forms of the protein. The binding specificity for aggregated amyloid (protofibrils and fibrils) rather than monomeric amyloid is a key pharmacological feature. By engaging the aggregated forms most associated with toxicity, lecanemab is thought to clear them through several mechanisms: direct antibody-mediated dissolution of aggregates, Fc-receptor-mediated microglial phagocytosis of opsonized amyloid complexes, and inhibition of further fibril formation.

    The pharmacodynamic evidence from Clarity AD confirms robust amyloid clearance: patients treated with lecanemab showed near-complete clearance of amyloid from PET-measurable brain regions by 18 months. This amyloid removal from the brain, measured in centiloids on PET imaging, was one of the key secondary endpoints and showed highly statistically significant differences versus placebo across all brain regions examined.


    How Leqembi Iqlik Is Different: The Subcutaneous Formulation Story

    The development of a subcutaneous formulation for lecanemab required solving a pharmaceutical challenge that applies to all large monoclonal antibodies: how to deliver an effective therapeutic dose through the skin, where the absorption rate and volume limitations differ substantially from intravenous administration.

    The approved SC formulation uses a concentrated lecanemab solution delivered via pre-filled autoinjector at 500 mg per 2 mL injection volume for initiation dosing (two 250 mg autoinjectors per dose) and 360 mg for maintenance. The formulation does not include hyaluronidase, unlike the SC pembrolizumab formulation (Keytruda Qlex) discussed in a previous HED post. Lecanemab’s SC delivery achieves pharmacokinetically equivalent exposure to IV dosing through the concentration and volume of the SC formulation itself, without enzymatic disruption of the subcutaneous matrix.

    The pharmacokinetic equivalence to IV was demonstrated through sub-studies in the Clarity AD long-term extension (LTE). These studies evaluated multiple SC dosing regimens and established that once-weekly SC administration produces area under the curve (AUC) and steady-state trough concentrations equivalent to the approved biweekly IV regimen of 10 mg/kg. The amyloid removal on PET imaging in LTE participants who switched from IV to SC maintenance dosing was maintained, providing biomarker evidence that the SC route produces clinically equivalent amyloid clearance.

    The autoinjector device is designed for patient or caregiver self-administration. Each injection delivers the dose in approximately 15 seconds. For the 500 mg initiation dose, two injections are given simultaneously or in close sequence at each weekly dosing occasion. Injection sites include the abdomen and thigh.

    The most significant clinical implication of the SC initiation approval is the elimination of infusion reactions as a clinical concern at treatment start. In Clarity AD with IV dosing, infusion reactions occurred in 26.4% of lecanemab-treated patients, concentrated in the first dose (75% occurred on day 1). These reactions, predominantly mild to moderate, required premedication protocols, monitoring time, and occasional infusion rate modifications. The SC route eliminates infusion reactions from the ARIA and infusion management framework.


    The Clarity AD Evidence Base: What the Foundational Trial Data Shows

    The efficacy and safety of lecanemab rest on Phase 3 Clarity AD (NCT03887455), the pivotal global randomized trial that supported full traditional FDA approval in July 2023 and all subsequent regulatory approvals globally.

    Clarity AD design and population

    Clarity AD enrolled 1,795 adults aged 50 to 90 years with confirmed amyloid pathology (by PET or CSF) and clinical diagnosis of either MCI due to Alzheimer’s disease or mild Alzheimer’s dementia. Baseline CDR-SB score indicated early disease (mean approximately 3.2 on a 0 to 18 scale). Patients were randomized 1:1 to lecanemab 10 mg/kg IV every 2 weeks or placebo for 18 months. 95% of completers enrolled in the open-label extension.

    Primary and key secondary endpoints at 18 months

    EndpointLecanemabPlaceboResult
    CDR-SB change from baseline (primary)1.211.66Difference minus 0.45 (95% CI minus 0.67 to minus 0.23); p=0.00005; 27% slowing
    Amyloid PET (centiloids, key secondary)Near-complete clearanceAccumulationp less than 0.001
    ADAS-Cog14 (key secondary)Less declineMore declinep less than 0.001
    ADCOMS (key secondary)Less declineMore declinep less than 0.001
    ADCS-MCI-ADL (key secondary)Less declineMore declinep less than 0.001
    Earliest significant CDR-SB separation6 months—p less than 0.01

    Source: van Dyck CH et al. Lecanemab in Early Alzheimer’s Disease. NEJM. 2023;388(1):9-21. doi:10.1056/NEJMoa2212948.

    The 27% slowing of clinical decline is measured on the CDR-SB, the Clinical Dementia Rating Sum of Boxes, a clinician-administered scale assessing six domains: memory, orientation, judgment and problem solving, community affairs, home and hobbies, and personal care. Each domain is rated 0 to 3 and the scores are summed for a total of 0 to 18. A lower score reflects better function. The treatment difference of 0.45 points at 18 months, on a scale where a change from 0.5 to 1 in any domain reflects a meaningful shift in independence, represents measurable preservation of function across the early disease population.

    Long-term open-label extension data: the benefit deepens

    The Clarity AD OLE, with four years of data, shows the clinical benefit of sustained lecanemab treatment growing over time compared to a matched control cohort from the Alzheimer’s Disease Neuroimaging Initiative (ADNI):

    TimepointCDR-SB benefit versus ADNI-matched controls
    18 months (end of core study)0.52 points
    36 months (18 months of OLE)1.01 points
    48 months (30 months of OLE)1.75 points

    Source: Clarity AD OLE 48-month data. PMC12725329.

    This growing absolute benefit over time is consistent with the hypothesis that early removal of amyloid pathology interrupts the downstream disease cascade in a way that produces compounding benefit: the longer treatment continues, the more neurological damage is prevented compared to the untreated trajectory.

    The OLE data also showed that 95% of Clarity AD completers chose to enroll in the open-label extension, a patient choice rate that reflects the acceptability of continued treatment and confidence in the drug’s benefit profile among both patients and their treating physicians.

    LEADER real-world data: the clinical practice picture

    The LEADER study, Leqembi’s real-world evidence program, presented data at the Alzheimer’s Association International Conference (AAIC) in July 2026 showing that in clinical practice:

    Over 75% of early Alzheimer’s patients enrolled in the study remained stable and nearly 7% improved over an average of 17 months of treatment. Eisai

    This real-world data is complementary to the controlled trial results and addresses the question of whether the Clarity AD findings translate to the broader clinical population. The stability rate in clinical practice, in patients selected by treating physicians rather than a research protocol, provides some reassurance that the trial results are not artifactual of a highly selected trial population.


    The Leqembi Iqlik Dosing Framework: What the Full SC Schedule Looks Like

    The approval of SC initiation dosing creates a complete at-home treatment pathway for the first time:

    PhaseFormulationDoseFrequencyDurationSetting
    Initiation (SC)Leqembi Iqlik500 mg (two 250 mg injections)Once weekly18 monthsHome (patient or caregiver)
    Initiation (IV alternative)Leqembi10 mg/kgEvery 2 weeks18 monthsInfusion center
    Maintenance (SC)Leqembi Iqlik360 mgOnce weeklyOngoingHome (patient or caregiver)

    Patients and physicians can choose between the SC and IV initiation routes. The clinical data support equivalent efficacy and biomarker outcomes for both routes; the choice is a shared decision based on patient preference, caregiver capacity, infusion center access, and the individual clinical context.

    For patients who initiate with IV and want to transition to SC maintenance, the August 2025 maintenance approval supports that pathway. For patients who prefer to start at home from dose one, the July 2026 initiation approval enables that pathway. The result is flexibility that was not available at any point in the drug’s first three years of commercial availability.


    Safety: What Patients, Caregivers, and Prescribers Need to Understand

    The safety considerations for lecanemab center on ARIA (amyloid-related imaging abnormalities), which are an on-target effect of anti-amyloid antibody therapy reflecting the vascular and parenchymal response to amyloid removal from the brain.

    ARIA: what it is and how it is managed

    ARIA occurs in two forms. ARIA-E involves cerebral edema or sulcal effusion visible on FLAIR MRI sequences, reflecting blood-brain barrier disruption and edema at sites of amyloid clearance. ARIA-H involves cerebral microhemorrhages, superficial siderosis, or macrohemorrhages, reflecting small vascular bleeds associated with amyloid clearance from vessel walls.

    In Clarity AD:

    • ARIA-E: 12.6% (lecanemab) versus 1.7% (placebo). Symptomatic ARIA-E: 2.8% versus 0.0%
    • ARIA-H: 17.3% (lecanemab) versus 9.0% (placebo). Symptomatic ARIA-H: 0.7% versus 0.2%

    The large majority of ARIA events were asymptomatic and detected on protocol MRI monitoring. Symptomatic ARIA events produced headache, confusion, dizziness, or visual disturbances in a minority of those detected radiographically. Most ARIA events resolved spontaneously or with temporary treatment interruption.

    ApoE4 carrier status substantially affects ARIA risk: homozygous ApoE4 carriers (approximately 2 to 3% of the population) had ARIA rates approximately 3-fold higher than non-carriers. ApoE4 genotyping before treatment initiation is recommended in the prescribing information to inform the risk-benefit discussion.

    ARIA monitoring requirements

    MRI monitoring before initiating treatment, before the 5th, 7th, and 14th infusions (at approximately 3, 6, and 12 months with IV dosing), and as clinically indicated is required per the prescribing information. The monitoring schedule for SC initiation dosing aligns with similar timepoints. ARIA detection before it becomes symptomatic allows dose holds to support resolution, which is the primary management approach.

    The ARIA context for SC administration

    The SC formulation is expected to produce ARIA rates comparable to IV administration, based on the pharmacokinetic equivalence and the established relationship between amyloid clearance (which is equivalent between routes) and ARIA incidence. This does not eliminate ARIA risk; it means the risk profile is similar to what has been established with IV dosing. The elimination of infusion reactions with SC administration improves one aspect of the safety experience without affecting the ARIA monitoring requirements.

    Boxed warnings

    Leqembi (and Leqembi Iqlik) carries a boxed warning for ARIA, including serious and life-threatening events. Patients on anticoagulants, or with additional risk factors for bleeding, may have higher ARIA-H risk and should be evaluated carefully before initiating treatment. The use of tissue plasminogen activator (tPA) for stroke in lecanemab-treated patients requires careful clinical judgment given the potential for increased hemorrhagic risk in ARIA-affected individuals.


    The Meaning of This Approval Beyond the Label

    The approval of lecanemab as an at-home self-administered treatment from the first dose is not a minor administrative update to an existing drug. It is a conceptual shift in what disease-modifying Alzheimer’s therapy looks like as a lived experience.

    Every other element of Alzheimer’s disease management, the cognitive and behavioral symptoms, the functional decline, the caregiver burden, the loss of independence, happens at home, in daily life. Until this approval, the only disease-modifying therapy available required a patient and caregiver to organize their lives around biweekly clinic visits for infusions that could last several hours. The subcutaneous initiation approval brings the disease-modifying treatment into the same setting where the disease itself is experienced.

    For early Alzheimer’s patients who retain sufficient independence and cognitive function to engage meaningfully with their own care, a treatment that can be self-administered at home is one that they can participate in as an active health decision rather than as a healthcare system dependent. That distinction matters to patients, to caregivers, and to the long-term sustainability of treatment adherence.

    The LEADER real-world data, showing 75% stability and 7% improvement at an average of 17 months, is the early evidence that this is working outside of trial conditions. It is not definitive; it is not placebo-controlled; but it is a signal from clinical practice that the Clarity AD trial results are not confined to the controlled research environment.

    For patients and families living with early Alzheimer’s disease who want to understand whether lecanemab or Leqembi Iqlik may be appropriate: the conversation begins with a neurologist who can evaluate cognitive status, confirm amyloid pathology, assess ApoE4 status, review anticoagulant and other medications, and discuss the specific risk-benefit profile in the context of the individual patient’s disease stage and overall health.

    The Alzheimer’s Association (alz.org; 24-hour helpline 1-800-272-3900) and the Alzheimer’s Drug Discovery Foundation maintain current information on treatment options, clinical trials, and caregiver resources.


    Sources

    FDA approval announcement: FDA approves first at-home starting dose for Alzheimer’s disease treatment. FDA.gov. July 13, 2026.

    Eisai and Biogen press release: FDA Approves LEQEMBI IQLIK (lecanemab-irmb) Subcutaneous Injection as an Initiation Dose for Early Alzheimer’s Disease. GlobeNewswire. July 13, 2026.

    Biogen investor news: FDA Approves LEQEMBI IQLIK (lecanemab-irmb) Subcutaneous Injection as an Initiation Dose for Early Alzheimer’s Disease. investors.biogen.com. July 13, 2026.

    BioArctic press release: FDA approves Leqembi Iqlik (lecanemab-irmb) subcutaneous injection as a starting dose for early Alzheimer’s disease. bioarctic.com. July 13, 2026.

    Drugs.com approval news: FDA Approves Leqembi Iqlik (lecanemab-irmb) Subcutaneous Injection as an Initiation Dose for Early Alzheimer’s Disease. drugs.com. July 13, 2026.

    Psychiatry Advisor (SC formulation clinical context, home administration framing): Lecanemab SC Starting Regimen Approved for Early Alzheimer Disease. psychiatryadvisor.com. July 2026.

    Healio (LEADER real-world data, AAIC 2026 reference): FDA approves subcutaneous Leqembi for initiation. healio.com. July 2026.

    Clarity AD primary NEJM publication: van Dyck CH et al. Lecanemab in Early Alzheimer’s Disease. NEJM. 2023;388(1):9-21. doi:10.1056/NEJMoa2212948.

    Clarity AD topline press release (Biogen): LECANEMAB CONFIRMATORY PHASE 3 CLARITY AD STUDY MET PRIMARY ENDPOINT. investors.biogen.com. September 2022.

    Clarity AD full results (Eisai/CTAD 2022): Eisai Presents Full Results of Lecanemab Phase 3 Confirmatory Clarity AD Study. eisai.com. November 2022.

    Clarity AD OLE 48-month data (PMC): The Lecanemab Clarity AD Open-Label Extension in Early Alzheimer’s Disease: Initial Findings From the 48-Month Analysis. PMC12725329.

    Clarity AD OLE 4-year AAIC 2025 data (BioArctic): Latest data presented at AAIC 2025 reinforces lecanemab’s clinical effect. bioarctic.com. July 2025.

    SC maintenance approval (August 2025, Biogen): FDA Approves LEQEMBI IQLIK (lecanemab-irmb) Subcutaneous Injection for Maintenance Dosing. investors.biogen.com. August 2025.

    Amyloid biology in Alzheimer’s disease: Amyloid Beta and Alzheimer’s Disease. PMC7232739.

    Leqembi original full FDA approval (July 2023): FDA grants traditional approval to Alzheimer’s disease treatment. FDA.gov.

    NIA Alzheimer’s disease overview: Alzheimer’s Disease Fact Sheet. NIA.

    Leqembi prescribing information: LEQEMBI (lecanemab-irmb) and LEQEMBI IQLIK Prescribing Information. Eisai Co., Ltd. 2026.

    Leqembi approval history: Leqembi FDA Approval History. drugs.com.

    Patient resources: Alzheimer’s Association 24-hour helpline: 1-800-272-3900 | Alzheimer’s Drug Discovery Foundation | Eisai Leqembi patient support | BrightFocus Foundation Alzheimer’s resources | ClinicalTrials.gov: search lecanemab

    Disclaimer: Health Evidence Digest provides general information about FDA approvals and health research for educational purposes. This content is not a substitute for professional medical advice. Leqembi (lecanemab-irmb) and Leqembi Iqlik carry a boxed warning for amyloid-related imaging abnormalities (ARIA), including serious and life-threatening events. Treatment requires confirmation of amyloid pathology before initiating, baseline and periodic MRI monitoring during treatment, and assessment of ApoE4 genotype and anticoagulant use given their effect on ARIA risk. All treatment decisions for early Alzheimer’s disease, including the choice between SC and IV formulations, should be made in close collaboration with a board-certified neurologist or geriatric psychiatrist experienced in Alzheimer’s disease management.