Blog

  • For 25 Years, Cisplatin-Based Chemotherapy Before Bladder Removal Was the Only Regimen Shown to Improve Survival in Muscle-Invasive Bladder Cancer. A New Phase 3 Trial Just Surpassed It.

    For 25 Years, Cisplatin-Based Chemotherapy Before Bladder Removal Was the Only Regimen Shown to Improve Survival in Muscle-Invasive Bladder Cancer. A New Phase 3 Trial Just Surpassed It.

    The essentials: On July 10, 2026, the FDA approved Padcev (enfortumab vedotin-ejfv, Astellas Pharma/Pfizer) plus Keytruda (pembrolizumab, Merck) or Keytruda Qlex (pembrolizumab and berahyaluronidase alfa-pmph, Merck) as neoadjuvant treatment followed by adjuvant treatment after cystectomy for adults with muscle-invasive bladder cancer (MIBC), regardless of cisplatin eligibility. This is the first platinum-free perioperative regimen approved for all adults with MIBC who are candidates for cystectomy. Two trials supported this combined label coverage. For cisplatin-ineligible patients: Phase 3 KEYNOTE-905/EV-303 (NCT03924895), which supported the November 21, 2025 approval in the cisplatin-ineligible population. pCR 57.1% versus 8.6% (surgery alone; p less than 0.001); statistically significant EFS and OS improvement. For cisplatin-eligible patients: Phase 3 KEYNOTE-B15/EV-304 (NCT04700124), n=808, presented at ASCO GU 2026 and published in JCO, supporting the July 10, 2026 expansion. Primary endpoint: event-free survival (EFS) by BICR. Median EFS: not reached (EV plus pembro) versus 48.5 months (gemcitabine plus cisplatin); HR 0.53 (95% CI 0.41 to 0.70). 47% reduction in risk of an EFS event. pCR: 55.8% versus 32.5%; estimated difference 23.4 percentage points (95% CI 16.7 to 29.8; p less than 0.0001). OS: HR 0.65 (95% CI 0.48 to 0.89; p=0.0029). All three endpoints met. This is the first regimen to beat standard cisplatin-based neoadjuvant chemotherapy in cisplatin-eligible MIBC since platinum-based neoadjuvant therapy was established as standard nearly 25 years ago. The regimen covers the full treatment sequence: 4 cycles of neoadjuvant EV plus pembrolizumab, radical cystectomy with pelvic lymph node dissection, then 5 additional adjuvant cycles of EV plus continued pembrolizumab. Grade 3 or higher adverse events: 75.7% (EV plus pembro) versus 67.2% (gemcitabine plus cisplatin). No new safety signals; consistent with established profile. Key context: approximately half of all MIBC patients are cisplatin-ineligible. The November 2025 approval addressed them. The July 2026 approval addresses the other half, who are eligible for cisplatin but now have a superior platinum-free alternative.

    Bladder cancer is the fourth most common cancer in men in the United States and is diagnosed in approximately 84,000 Americans per year. The majority of bladder cancers are non-muscle-invasive at diagnosis and are managed with local resection and intravesical therapy. But when cancer invades the muscular wall of the bladder, the clinical calculus changes fundamentally. Muscle-invasive bladder cancer (MIBC) carries a 5-year overall survival rate of approximately 50 to 60% with optimal treatment, meaning that even with the best available care, roughly half of patients will die of the disease within five years.

    For nearly 25 years, the best available care in the neoadjuvant setting meant one thing: cisplatin-based chemotherapy before surgery. The combination of gemcitabine plus cisplatin administered before radical cystectomy produces pathologic complete response (pCR, meaning no residual tumor at surgery) in approximately 30 to 40% of patients and improves survival compared to surgery alone. That survival benefit, established in meta-analyses and multiple randomized trials, made neoadjuvant cisplatin the standard of care and kept it there for more than two decades.

    The problem: approximately half of patients with MIBC cannot receive cisplatin. Kidney function decline, hearing loss, neuropathy, and performance status limitations all contribute to cisplatin ineligibility in a patient population that skews older and commonly has significant comorbidities. For these patients, surgery alone had been the standard, with all the survival disadvantage that comes from not having neoadjuvant systemic therapy.

    Padcev (enfortumab vedotin-ejfv) plus Keytruda (pembrolizumab) has now closed both gaps. The November 2025 approval for cisplatin-ineligible patients, based on KEYNOTE-905/EV-303, gave that neglected population their first perioperative systemic therapy option. The July 10, 2026 approval, based on KEYNOTE-B15/EV-304, extends the same regimen to cisplatin-eligible patients, where it did not just match cisplatin but surpassed it: median EFS not reached with EV plus pembrolizumab versus 48.5 months with gemcitabine plus cisplatin, pCR rate 55.8% versus 32.5%, and an overall survival advantage. All three primary and key secondary endpoints met in a 808-patient randomized Phase 3 trial.

    As Dr. Matthew Galsky of the Icahn School of Medicine at Mount Sinai, who presented the KEYNOTE-B15 data at ASCO GU 2026, put it: this is a pivotal moment. For the first time since cisplatin-based neoadjuvant therapy was shown to improve outcomes in patients with MIBC almost 25 years ago, a non-platinum-based regimen has surpassed it.


    What Muscle-Invasive Bladder Cancer Is and Why Surgery Alone Is Not Enough

    Bladder cancer originates in the urothelium, the transitional epithelial lining of the urinary tract. Non-muscle-invasive bladder cancer (stages Ta, T1, and carcinoma in situ) involves only the superficial layers and can be managed with transurethral resection and intravesical agents. Muscle-invasive disease (stage T2 or higher) has penetrated the detrusor muscle of the bladder wall, dramatically increasing metastatic risk and fundamentally changing treatment strategy.

    MIBC is staged using the TNM system. Stage T2 invades the inner half of the muscle; T3 extends through the muscle into perivesical fat; T4 invades adjacent structures including the prostate, uterus, or pelvic wall. Lymph node status (N0/N1) is assessed at surgery. All patients with resectable MIBC without distant metastasis are candidates for radical cystectomy with pelvic lymph node dissection as the definitive surgical approach.

    Radical cystectomy is curative in approximately 60 to 70% of patients with organ-confined (T2) disease but in only about 25 to 35% of patients with T3 to T4 or node-positive disease. The primary driver of recurrence and death is occult micrometastatic disease that is present but not detectable at the time of surgery. Systemic therapy before surgery (neoadjuvant) attacks this micrometastatic burden while the tumor is still accessible and the patient has not yet undergone the physiological stress of a major operation.

    The concept of pathologic complete response is important in MIBC: patients who have no residual tumor at the time of cystectomy (pCR, or ypT0N0) after neoadjuvant therapy have substantially better long-term outcomes than those with residual disease. A pCR rate of 55.8% in KEYNOTE-B15 means that more than half of cisplatin-eligible MIBC patients treated with perioperative EV plus pembrolizumab had no viable tumor left at surgery, compared with approximately 1 in 3 patients on standard cisplatin-based chemotherapy.


    What Enfortumab Vedotin Is: The Nectin-4 ADC Mechanism

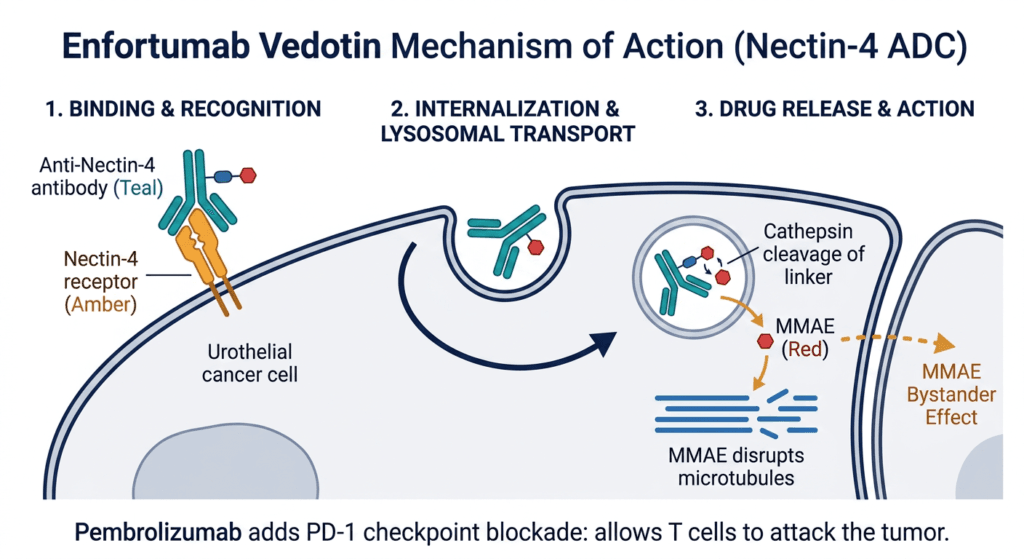
    Enfortumab vedotin-ejfv (Padcev) is an antibody-drug conjugate (ADC) that targets Nectin-4, a cell adhesion molecule that is highly expressed in urothelial carcinoma and in a variety of other cancer types, while having more limited expression in normal adult tissues. This differential expression creates a therapeutic window for tumor-directed drug delivery.

    The three components of enfortumab vedotin:

    The antibody: anti-Nectin-4. A fully human monoclonal antibody that binds with high affinity to Nectin-4 on the surface of urothelial cancer cells and is internalized through receptor-mediated endocytosis.

    The linker: protease-cleavable. A maleimide-based linker that is cleaved by cathepsins in the acidic lysosomal environment of the internalized cell, releasing the cytotoxic payload selectively inside the tumor cell. The linker also allows a bystander killing effect: free payload diffuses from the targeted cell to adjacent cancer cells, even those with lower Nectin-4 expression.

    The payload: MMAE (monomethyl auristatin E). A potent microtubule-disrupting agent that binds to tubulin and prevents polymerization, triggering G2/M cell cycle arrest and apoptosis. MMAE is approximately 100 to 1,000 times more potent than conventional chemotherapy on a per-molecule basis, which is why the ADC delivery format can produce activity at relatively low doses compared to systemic MMAE administration.

    Nectin-4 is expressed in more than 97% of urothelial carcinomas at moderate to high levels, making it one of the most broadly applicable ADC targets in any solid tumor type. This near-universal expression means that patient selection by Nectin-4 testing is not currently required: essentially all urothelial cancer patients are likely to have Nectin-4-expressing tumors.

    The Two-Trial Evidence Base: KEYNOTE-905 and KEYNOTE-B15

    The July 10, 2026 approval covers all MIBC patients regardless of cisplatin eligibility, resting on two separate Phase 3 trials that together cover the complete MIBC population.

    KEYNOTE-905/EV-303: The cisplatin-ineligible population (November 2025 approval)

    KEYNOTE-905/EV-303 (NCT03924895) enrolled 344 patients with MIBC who were ineligible for or declined cisplatin-based chemotherapy, randomized 1:1 to neoadjuvant EV plus pembrolizumab followed by cystectomy followed by adjuvant EV plus pembrolizumab, or immediate cystectomy alone.

    EndpointEV plus pembrolizumabSurgery aloneResult
    pCR (ypT0N0)57.1%8.6%p less than 0.001
    EFSStatistically significant improvementReferencePrespecified threshold met
    OSStatistically significant improvementReferencePrespecified threshold met

    Source: KEYNOTE-905/EV-303. NCT03924895.

    The 57.1% pCR rate in a cisplatin-ineligible population that had no approved perioperative systemic therapy option before this trial was the most striking finding from KEYNOTE-905. The November 2025 FDA approval made EV plus pembrolizumab the first perioperative regimen available to this half of the MIBC population.

    KEYNOTE-B15/EV-304: The cisplatin-eligible population (July 2026 approval)

    KEYNOTE-B15/EV-304 (NCT04700124) enrolled 808 patients with previously untreated MIBC who were eligible for cisplatin-based therapy and candidates for radical cystectomy with pelvic lymph node dissection. Patients required central pathology and imaging confirmation of clinical stage cT2 to T4aN0M0 or T1 to T4aN1M0 disease. They were randomized 1:1 to:

    EV plus pembrolizumab arm (n=405): 4 cycles of neoadjuvant EV 1.25 mg/kg on days 1 and 8 plus pembrolizumab 200 mg on day 1, every 3 weeks, followed by radical cystectomy plus PLND, then 5 additional cycles of adjuvant EV plus 13 additional cycles of adjuvant pembrolizumab (or pembrolizumab dosed 400 mg every 6 weeks for 7 cycles).

    Gemcitabine plus cisplatin arm (n=403): 4 cycles of neoadjuvant gemcitabine 1,000 mg/m2 on days 1 and 8 plus cisplatin 70 mg/m2 on day 1, every 3 weeks, followed by radical cystectomy plus PLND, then observation.

    The primary endpoint was EFS by blinded independent central review. Key secondary endpoints included pCR by central pathologist review and OS. The data were presented at the 2026 ASCO GU Symposium in San Francisco and published in the Journal of Clinical Oncology.

    EndpointEV plus pembrolizumabGemcitabine plus cisplatinResult
    Median EFS (primary, BICR)Not reached48.5 monthsHR 0.53 (95% CI 0.41 to 0.70)
    EFS risk reduction47%Reference—
    pCR rate (ypT0N0)55.8%32.5%Difference 23.4 pp (95% CI 16.7 to 29.8); p less than 0.0001
    OS (key secondary)ImprovementReferenceHR 0.65 (95% CI 0.48 to 0.89); p=0.0029
    Grade 3 or higher AEs75.7%67.2%Numerically higher with EV plus pembro

    Source: Galsky MD et al. KEYNOTE-B15/EV-304, JCO ASCO 2026 LBA630. doi:10.1200/JCO.2026.44.7_suppl.LBA630. NCT04700124.

    The primary endpoint finding of a 47% reduction in EFS risk, with median EFS not yet reached in the EV plus pembrolizumab arm versus 48.5 months in the cisplatin-based chemotherapy arm, is one of the most compelling perioperative oncology datasets in bladder cancer history. The EFS result was statistically significant and clinically substantial, meeting the primary endpoint convincingly.

    The pCR data further anchors the magnitude of the benefit: 55.8% of cisplatin-eligible patients treated with EV plus pembrolizumab had no residual viable tumor at cystectomy, compared with 32.5% on standard gemcitabine plus cisplatin. A 23-percentage-point improvement in pCR is a large absolute difference in a surgically curable disease where pCR is strongly associated with long-term disease-free survival.

    The OS benefit (HR 0.65, p=0.0029) is particularly significant. Overall survival advantages in the neoadjuvant setting in bladder cancer have historically required large meta-analyses to establish with the available single-trial data. Demonstrating a statistically significant OS advantage in a single 808-patient trial reflects the genuine magnitude of the EV plus pembrolizumab benefit over cisplatin-based standard of care.


    The Complete Treatment Sequence: What Perioperative Means in Practice

    The approved regimen covers three sequential phases for patients eligible for cystectomy, and understanding the full treatment timeline is essential for patient counseling and multidisciplinary care coordination.

    Phase 1 — Neoadjuvant (before surgery), 4 cycles (12 weeks):

    • Enfortumab vedotin 1.25 mg/kg (maximum 125 mg for patients at or above 100 kg) IV on days 1 and 8 of each 21-day cycle
    • Pembrolizumab 200 mg IV on day 1 every 3 weeks, or 400 mg IV every 6 weeks; or Keytruda Qlex subcutaneous on corresponding schedule
    • 4 total neoadjuvant cycles

    Surgery: Radical cystectomy with pelvic lymph node dissection, performed after completing the 4 neoadjuvant cycles.

    Phase 2 — Adjuvant (after surgery), continuation:

    • Enfortumab vedotin continues for 5 additional cycles (same dosing as neoadjuvant)
    • Pembrolizumab continues: 200 mg IV every 3 weeks for 13 total adjuvant cycles (approximately 39 weeks), or 400 mg every 6 weeks for 7 adjuvant cycles; or Keytruda Qlex equivalents

    The total treatment duration is approximately 12 weeks neoadjuvant plus the adjuvant phase, which extends approximately a year post-surgery for the full pembrolizumab course. This is a longer treatment commitment than neoadjuvant chemotherapy alone (which has no adjuvant component beyond surveillance), and the logistics of 18 months of combined therapy require careful coordination between the medical oncologist, urologic oncologist, and the patient’s support systems.

    A notable feature of the EV-304 trial is that 262 of 405 EV-plus-pembrolizumab patients started the adjuvant phase and 208 completed it, reflecting real-world dropout rates from the surgical pathway and treatment tolerance over a prolonged regimen. Understanding that not all patients who start neoadjuvant treatment will complete the full intended adjuvant course is important for setting expectations in clinical practice.


    The Cisplatin-Ineligibility Problem This Approval Resolves

    Understanding why “regardless of cisplatin eligibility” matters requires understanding why approximately half of MIBC patients cannot receive cisplatin to begin with.

    Cisplatin nephrotoxicity is the primary limiting factor. Standard cisplatin eligibility criteria require GFR at or above 50 to 60 mL/min/1.73m2 depending on the institutional protocol. Bladder cancer skews toward older adults and is associated with smoking-related comorbidities including cardiovascular and renal disease; many patients have renal function below this threshold at diagnosis. Other cisplatin eligibility barriers include hearing loss (cisplatin is ototoxic), peripheral neuropathy, Eastern Cooperative Oncology Group performance status of 2 or higher, and New York Heart Association class 3 or 4 heart failure.

    Before KEYNOTE-905, cisplatin-ineligible patients with MIBC had no approved perioperative systemic therapy option at all. They went directly to surgery without neoadjuvant treatment, accepting the survival disadvantage that came from operating on disease that neoadjuvant therapy might have downstaged or eliminated. KEYNOTE-905 gave this population their first approved option. KEYNOTE-B15 then went further, demonstrating that even patients who are eligible for cisplatin are better served by the ADC plus checkpoint inhibitor combination.

    The combined impact of both trials and both approvals means that MIBC patients in 2026 have a single effective perioperative regimen that is appropriate regardless of their renal function, hearing status, or other cisplatin eligibility criteria. The treatment algorithm has simplified: if a patient is a candidate for cystectomy, EV plus pembrolizumab is an appropriate perioperative treatment. The question of whether they can tolerate cisplatin is no longer the gating question for neoadjuvant therapy access.


    Safety: What the KEYNOTE-B15 Profile Shows

    The safety profile of EV plus pembrolizumab in KEYNOTE-B15 was consistent with the established safety experience from prior trials, with no new safety signals identified. The grade 3 or higher adverse event rate was 75.7% in the EV plus pembrolizumab arm versus 67.2% in the gemcitabine plus cisplatin arm, a numerically higher rate that requires clinical context.

    Enfortumab vedotin’s adverse event profile reflects both the MMAE payload and on-target skin effects from Nectin-4 expression in the epidermis:

    Boxed warnings for Padcev (enfortumab vedotin-ejfv):

    Skin reactions: Severe skin reactions including Stevens-Johnson syndrome and toxic epidermal necrolysis have been reported, some with fatal outcomes. Skin reactions are one of the most clinically significant toxicities unique to enfortumab vedotin. Patients should be monitored for new or worsening skin reactions. Grade 3 skin reactions require treatment interruption; Stevens-Johnson syndrome or TEN require permanent discontinuation.

    Hyperglycemia: Clinically significant hyperglycemia, including new-onset diabetes and diabetic ketoacidosis, has occurred. Monitor blood glucose before each infusion. Withhold for glucose greater than 250 mg/dL.

    Additional warnings and precautions:

    Safety itemDetailsClinical guidance
    Peripheral neuropathySensory and motor neuropathy from MMAE mechanism; grade 3 or higher in approximately 5 to 10% in trialsMonitor for neuropathy symptoms before each cycle; dose modification for grade 2 or higher
    PneumonitisInterstitial lung disease reported; potentially fatalMonitor for respiratory symptoms; grade 2 or higher requires treatment interruption
    Ocular toxicityDry eye, blurred vision, keratitisOphthalmologic evaluation if symptomatic
    Embryo-fetal toxicityMMAE can cause fetal harmEffective contraception required during treatment and for specified periods after last dose
    Pembrolizumab immune-mediated adverse eventsFull immune-related AE profile (pneumonitis, colitis, hepatitis, endocrinopathies, nephritis)Standard pembrolizumab immune-related AE monitoring and management applies

    The safety profile across the neoadjuvant and adjuvant EV plus pembrolizumab combination represents the superimposition of the two drugs’ individual toxicity profiles. Oncology teams experienced in managing ADC skin and neuropathy toxicities, and in managing checkpoint inhibitor immune-mediated adverse events, will find the combination manageable with established protocols. Teams less experienced with either drug class may benefit from multidisciplinary support, particularly for severe skin reactions and immune-mediated toxicities.


    Padcev’s Complete Indication Picture After July 2026

    IndicationSettingApproval date
    Locally advanced or metastatic urothelial cancer (with pembrolizumab)First-line, cisplatin-ineligibleDecember 2023
    Locally advanced or metastatic urothelial cancer (with pembrolizumab)First-line, regardless of cisplatin eligibilityApril 2024
    Locally advanced or metastatic urothelial cancer (monotherapy)Previously treated with platinum and PD-1/L1 inhibitorDecember 2019/2021
    MIBC, neoadjuvant plus adjuvant (with pembrolizumab)Perioperative, cisplatin-ineligibleNovember 21, 2025
    MIBC, neoadjuvant plus adjuvant (with pembrolizumab)Perioperative, regardless of cisplatin eligibilityJuly 10, 2026

    What This Means for Patients and Multidisciplinary Bladder Cancer Teams

    For patients with newly diagnosed MIBC who are candidates for cystectomy

    This approval means that for the first time, a single perioperative treatment regimen is appropriate and approved for all MIBC patients regardless of cisplatin eligibility. Patients who were previously told they could not receive chemotherapy before surgery because of kidney function, hearing, or other cisplatin barriers now have an effective neoadjuvant option.

    For patients who are cisplatin-eligible, the KEYNOTE-B15 data make a compelling case that EV plus pembrolizumab should be considered as the preferred perioperative approach over gemcitabine plus cisplatin, based on superior EFS, pCR, and OS. Clinical practice changes of this magnitude take time to be incorporated into guidelines and routine care, and the conversation with patients should honestly present the KEYNOTE-B15 data alongside the established cisplatin-based evidence. The higher grade 3 or higher AE rate with EV plus pembrolizumab (75.7% versus 67.2%) and the specific skin and neuropathy toxicity profile are relevant factors for shared decision-making.

    For patients whose surgeons and medical oncologists are now coordinating a perioperative regimen: the critical addition to the care pathway is pre-surgical integration of the neoadjuvant cycles, which now include 12 weeks of combination therapy before cystectomy, followed by surgical planning, and then the adjuvant phase. Patients should understand the full duration of treatment commitment before beginning.

    For urologic oncologists and medical oncologists

    KEYNOTE-B15 establishes EV plus pembrolizumab as a perioperative option that is superior to the standard gemcitabine plus cisplatin regimen in cisplatin-eligible MIBC on all three key endpoints: EFS, pCR, and OS. Dr. Christopher Hoimes of Duke Cancer Institute, a principal investigator for EV-304, described the data as supporting EV plus pembrolizumab as a novel treatment option and potential standard of care for MIBC patients regardless of cisplatin eligibility.

    Incorporating this into multidisciplinary tumor board discussions and treatment protocols requires coordination between urology, medical oncology, and supportive care teams, particularly given the skin reaction boxed warning and the monitoring requirements for neuropathy, hyperglycemia, and immune-mediated adverse events. Subspecialty dermatology access and ophthalmology evaluation pathways should be integrated into the perioperative care plan for patients starting EV.

    For related HED coverage on bladder cancer and checkpoint inhibitor combination approvals, see our post on Keytruda Qlex receiving its new first-line TNBC indication alongside Trodelvy and our post on Revtorpyk (gedatolisib) becoming the first targeted therapy for PIK3CA wild-type HR+/HER2- breast cancer.

    For patients and families navigating a muscle-invasive bladder cancer diagnosis, the Bladder Cancer Advocacy Network (bcan.org; 1-888-901-BCAN) and the American Cancer Society’s Bladder Cancer resource page maintain current treatment information and patient support resources.


    Sources

    FDA approval announcement: FDA approves pembrolizumab or pembrolizumab and berahyaluronidase alfa-pmph each with enfortumab vedotin-ejfv for muscle invasive bladder cancer. FDA.gov. July 10, 2026.

    Pfizer/Astellas press release: U.S. FDA Approves PADCEV plus Keytruda as Neoadjuvant and Adjuvant Treatment for Muscle-Invasive Bladder Cancer Regardless of Cisplatin Eligibility. Pfizer Inc. July 10, 2026.

    Astellas press release: U.S. FDA Approves PADCEV plus Keytruda as Neoadjuvant and Adjuvant Treatment for Muscle-Invasive Bladder Cancer Regardless of Cisplatin Eligibility. newsroom.astellas.com. July 10, 2026.

    Drugs.com approval news: U.S. FDA Approves Padcev plus Keytruda or Keytruda Qlex as Neoadjuvant and Adjuvant Treatment for Muscle-Invasive Bladder Cancer Regardless of Cisplatin Eligibility. drugs.com. July 10, 2026.

    KEYNOTE-B15/EV-304 JCO ASCO 2026 primary abstract: Galsky MD et al. Neoadjuvant and adjuvant enfortumab vedotin plus pembrolizumab for participants with MIBC who are eligible for cisplatin: randomized, open-label, phase 3 KEYNOTE-B15 study. JCO ASCO 2026 LBA630. doi:10.1200/JCO.2026.44.7_suppl.LBA630.

    KEYNOTE-B15 trial registration: NCT04700124. ClinicalTrials.gov.

    OncLive (EFS primary endpoint data, all three endpoints met): Perioperative Enfortumab Vedotin/Pembrolizumab Meets EFS, OS, pCR End Points in Cisplatin-Eligible MIBC. onclive.com. July 2026.

    Targeted Oncology (median EFS not reached versus 48.5 months): Enfortumab Vedotin/Pembrolizumab Redefines Neoadjuvant Therapy for MIBC. targetedonc.com. June 2026.

    GU Oncology Now (HR 0.53 EFS, Dr. Galsky quote): EV/Pembro Improved EFS, OS in Cisplatin-Eligible MIBC. guoncologynow.com. March 2026.

    Cancer Therapy Advisor (pCR 55.8% vs 32.5%, OS HR 0.65 exact data): ASCO GU 2026: Are Combinatorial Therapies the Future Standard of Care in RCC and MIBC? cancertherapyadvisor.com. February 2026.

    Urology Times (full trial design detail, Dr. Galsky presentation context): KEYNOTE-B15: EV/pembro sets new benchmark before cystectomy in MIBC. urologytimes.com. 2026.

    Pharmacy Times (cisplatin ineligibility context, global MIBC epidemiology): Phase 3 Data Back a New Perioperative Standard for Cisplatin-Eligible Muscle-Invasive Bladder Cancer. pharmacytimes.com. June 2026.

    UroToday (Dr. Hoimes investigator quote, Pfizer/Astellas/Merck collaboration context): U.S. FDA Approves PADCEV plus Keytruda as Neoadjuvant and Adjuvant Treatment for MIBC Regardless of Cisplatin Eligibility. urotoday.com. July 2026.

    KEYNOTE-905/EV-303 prior approval (November 2025): FDA approves pembrolizumab with enfortumab vedotin-ejfv for muscle invasive bladder cancer (cisplatin-ineligible). FDA.gov. November 21, 2025.

    KEYNOTE-905 trial registration: NCT03924895. ClinicalTrials.gov.

    Bladder cancer overview: Bladder Cancer. StatPearls. NCBI.

    Padcev prescribing information: PADCEV (enfortumab vedotin-ejfv) Prescribing Information. Astellas Pharma US, Inc. 2026.

    Padcev approval history: Padcev FDA Approval History. drugs.com.

    Patient resources: Bladder Cancer Advocacy Network: 1-888-901-BCAN | American Cancer Society Bladder Cancer resources | Pfizer Padcev patient support | ClinicalTrials.gov: search bladder cancer enfortumab

    Disclaimer: Health Evidence Digest provides general information about FDA approvals and health research for educational purposes. This content is not a substitute for professional medical advice. Padcev (enfortumab vedotin-ejfv) carries a boxed warning for severe skin reactions including Stevens-Johnson syndrome and toxic epidermal necrolysis, and for hyperglycemia. The perioperative regimen combining Padcev and Keytruda requires coordinated care across medical oncology and urologic oncology, with monitoring for enfortumab vedotin-specific toxicities and pembrolizumab immune-mediated adverse events. Treatment decisions for muscle-invasive bladder cancer, including the choice of perioperative regimen and surgical approach, should be made through a multidisciplinary team including a urologic oncologist and a medical oncologist experienced in urothelial carcinoma.
  • Seasonal Allergic Rhinitis in School-Age Children Is One of the Most Undertreated Conditions in Pediatrics. Ryaltris Just Became the First Fixed-Dose Antihistamine-Steroid Nasal Spray Approved for Children as Young as Six.

    Seasonal Allergic Rhinitis in School-Age Children Is One of the Most Undertreated Conditions in Pediatrics. Ryaltris Just Became the First Fixed-Dose Antihistamine-Steroid Nasal Spray Approved for Children as Young as Six.

    The essentials: On July 7, 2026, the FDA expanded the approval of Ryaltris (olopatadine hydrochloride 665 mcg and mometasone furoate 25 mcg nasal spray, Glenmark Pharmaceuticals) to include children aged 6 to less than 12 years with seasonal allergic rhinitis (SAR). The prior lower age limit was 12 years. Ryaltris is now approved for adults and pediatric patients aged 6 and older, making it the first fixed-dose antihistamine-corticosteroid nasal spray approved for this age group in the United States. What Ryaltris is: a fixed-dose combination (FDC) nasal spray containing olopatadine hydrochloride (an antihistamine, H1 receptor antagonist) at 665 mcg per spray and mometasone furoate (a corticosteroid) at 25 mcg per spray. Two sprays per nostril are used for the adult dose; for children aged 6 to 11, one spray per nostril twice daily is the approved pediatric dose. The two active ingredients address both the histamine-mediated and inflammatory components of SAR simultaneously in a single device. The clinical basis for the age expansion: Phase 3, randomized, double-blind, placebo-controlled trial, n=446, children aged 6 to less than 12 years with seasonal allergic rhinitis. Dosing: one spray in each nostril twice daily for 14 days. Primary endpoint: change from baseline in average AM and PM patient-reported 12-hour reflective Total Nasal Symptom Score (rTNSS) over the 14-day period. Result: statistically significant improvement in average AM and PM rTNSS versus placebo (p=0.001). Trial completion rate: 96.6% (431 of 446 patients). TEAEs: 10.4% (Ryaltris) versus 12.0% (placebo), comparable between arms. Most common TEAEs: dysgeusia 1.3% versus 0.0% placebo; headache 1.3% versus 0.5%; epistaxis 0.9% versus 2.3% (nosebleed rate actually lower with Ryaltris than placebo). The pediatric findings were consistent with the clinical trial experience in the more than 4,000 adults and adolescents studied in the Ryaltris Phase 3 program. Primary publication: Prenner BM et al. Ann Allergy Asthma Immunol. 2022. doi:10.1016/j.anai.2022.07.029. Key safety warnings: potential reduction in pediatric growth velocity with intranasal corticosteroid use; immunosuppression risks (consistent with corticosteroid class); epistaxis; nasal ulceration; septal perforation; hypersensitivity.

    Seasonal allergic rhinitis is, by prevalence, one of the most common chronic conditions affecting school-age children in the United States. Estimates consistently place the prevalence at 10 to 15% of children aged 6 to 11 years, with up to 40% of all children affected by some form of allergic rhinitis across their school years. The condition is responsible for missed school days, reduced academic performance, impaired sleep, and daytime fatigue that affects every aspect of a child’s functioning during allergy season. Pediatric allergists and primary care physicians who manage these children have solid options for their older adolescent patients; the treatment toolkit for the 6-to-11 age group has been meaningfully more limited.

    The standard treatment approach for pediatric SAR has historically combined a non-sedating antihistamine (oral or intranasal) with an intranasal corticosteroid, each addressing different aspects of the allergic response. This two-medication approach is effective but creates adherence challenges: two devices, two dosing regimens, and for a school-age child managing medications, more complexity than a single product requires.

    Ryaltris (Glenmark Pharmaceuticals) was approved in January 2022 as the first fixed-dose combination of an antihistamine (olopatadine) and a corticosteroid (mometasone furoate) in a single nasal spray for SAR. The July 7, 2026 expansion to children aged 6 to 11 is supported by Phase 3 data specifically generated in this population, not extrapolated from adult data, and demonstrates that the same fixed-dose combination approach is effective and well-tolerated at the reduced one-spray-per-nostril pediatric dose.


    What Seasonal Allergic Rhinitis Is and Why It Matters in Children

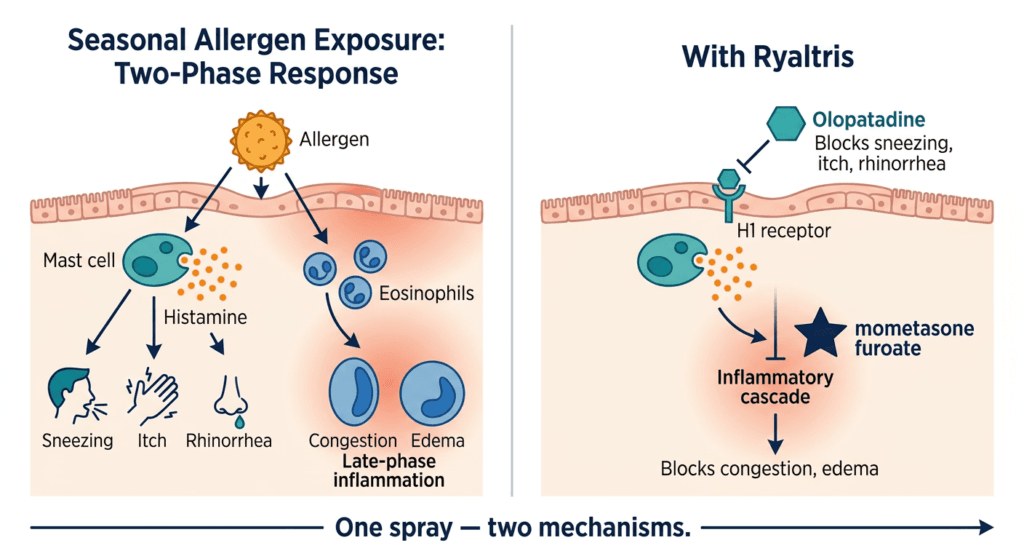
    Seasonal allergic rhinitis is an IgE-mediated hypersensitivity response to seasonal aeroallergens, most commonly tree pollen (spring), grass pollen (late spring and summer), and weed pollen including ragweed (late summer and fall). When a sensitized individual inhales these allergens, they bind to IgE antibodies on mast cells in the nasal mucosa. The mast cells degranulate, releasing histamine and other preformed mediators that produce the immediate symptoms of allergic rhinitis: sneezing, nasal itching, rhinorrhea, and watery eyes. A late-phase inflammatory response follows hours later, driven by eosinophils, basophils, and T cells, producing nasal congestion, mucosal edema, and the persistent stuffiness that dominates many patients’ experience of allergy season.

    The four nasal symptoms scored in the rTNSS, nasal congestion, rhinorrhea, nasal itching, and sneezing, capture both the histamine-mediated immediate response and the inflammatory late-phase response, which is why a drug that addresses only one pathway (antihistamine only, or corticosteroid only) may not address all four symptoms adequately.

    In children aged 6 to 11, SAR is not a minor inconvenience. Studies of SAR’s impact on school-age children consistently document:

    Sleep disruption from nighttime nasal congestion, with consequent daytime fatigue and difficulty concentrating. Poor school performance during peak allergy season, with documented effects on standardized testing scores in allergic versus non-allergic children during high-pollen days. Reduced participation in outdoor activities and physical education. Behavioral effects including irritability and reduced quality of life, reported by both children and their caregivers. Comorbidity with asthma, which is more likely to be poorly controlled in children with untreated or undertreated allergic rhinitis, through the unified airway model.

    Effective treatment of SAR in this age group is therefore not cosmetic or optional. It has direct implications for academic function, physical activity, sleep, and asthma control.


    How Ryaltris Works: The Two-Mechanism Fixed-Dose Combination

    Ryaltris addresses SAR through the complementary mechanisms of its two active ingredients, delivered simultaneously in a single nasal spray device.

    Olopatadine hydrochloride 665 mcg: the antihistamine component

    Olopatadine is a selective, relatively non-sedating H1 receptor antagonist that blocks histamine from binding to H1 receptors on nasal mucosal cells. When histamine is blocked at the H1 receptor, the immediate allergic response, sneezing, nasal itching, and rhinorrhea, is substantially reduced. Olopatadine also has mast cell-stabilizing properties, inhibiting the release of mediators from mast cells and thereby reducing both the immediate and the late-phase components of the allergic response.

    Intranasal olopatadine at 665 mcg is a higher dose than what was available in prior intranasal antihistamine products (azelastine, for example, is available at much lower per-spray concentrations but with a distinct pharmacological profile). The 665 mcg dose was selected through the Ryaltris development program to optimize the antihistamine contribution to the fixed-dose combination.

    Mometasone furoate 25 mcg: the corticosteroid component

    Mometasone furoate is a synthetic corticosteroid with high intranasal activity and very low systemic bioavailability when administered intranasally. Less than 1% of an intranasal mometasone dose reaches the systemic circulation, which is one of the reasons intranasal corticosteroids are considered safe for long-term use in allergic rhinitis at labeled doses.

    Corticosteroids reduce allergic inflammation through broad suppression of the inflammatory gene expression cascade: they reduce the production of cytokines, chemokines, and arachidonic acid-derived mediators from eosinophils, mast cells, and T cells in the nasal mucosa. This suppression of the late-phase inflammatory response addresses nasal congestion, a symptom that antihistamines alone do not adequately control, because congestion is driven primarily by inflammatory vasodilation and edema rather than by histamine directly.

    Why combining both in one spray is more than convenience

    The clinical rationale for fixed-dose combination therapy in SAR is not merely adherence convenience. The two active mechanisms are complementary, not redundant: the antihistamine addresses the immediate histamine-mediated response while the corticosteroid addresses the late-phase inflammatory response. Clinical studies of SAR treatment consistently show that patients on combination antihistamine plus corticosteroid therapy achieve better symptom control than those on either monotherapy, particularly for the congestion symptom that antihistamines address inadequately. The Ryaltris Phase 3 pivotal program in adults and adolescents directly compared Ryaltris to both component monotherapies (olopatadine-only and mometasone-only nasal sprays), demonstrating superiority over each monotherapy.

    Delivering both in a single device adds the practical benefit of a simplified regimen. For a school-age child who needs to use a nasal spray twice daily, the difference between one device and two devices is meaningful for adherence and for the practical management of a medication routine across a school day.


    The Phase 3 Pediatric Trial: What the Data Shows

    Design

    The Phase 3 pediatric trial was a randomized, double-blind, placebo-controlled parallel-group study enrolling 446 children aged 6 to less than 12 years with a documented history of seasonal allergic rhinitis and a positive skin prick test to a relevant seasonal allergen. Patients were required to have a nasal symptom score at screening consistent with at least moderate disease. Participants were randomized approximately 1:1 to Ryaltris one spray per nostril twice daily or placebo nasal spray for 14 days.

    The primary endpoint was the change from baseline in average morning (AM) and evening (PM) patient-reported 12-hour reflective Total Nasal Symptom Score (rTNSS) over the 14-day treatment period. The rTNSS is the sum of patient-rated severity (0 to 3 scale for each) across four nasal symptoms: nasal congestion, rhinorrhea, nasal itching, and sneezing, for a maximum score of 12. The reflective score captures symptoms over the prior 12 hours, covering the full day’s experience across both AM and PM assessment points.

    A pediatric-adapted quality of life questionnaire was used as a secondary endpoint, appropriate for the younger age group.

    Results

    EndpointRyaltrisPlaceboResult
    Primary: mean change from baseline in average AM/PM rTNSSStatistically significant improvementReferencep=0.001
    Trial completion rate——96.6% (431 of 446)
    TEAEs10.4%12.0%Comparable; lower rate with Ryaltris
    Dysgeusia (taste disturbance)1.3%0.0%Higher with Ryaltris (class effect of olopatadine)
    Headache1.3%0.5%Slight numeric difference
    Epistaxis (nosebleed)0.9%2.3%Lower with Ryaltris than placebo
    Quality of life (secondary)Positive impactReferenceConsistent with symptom improvement

    Source: Prenner BM et al. Olopatadine/mometasone furoate nasal spray in pediatric patients aged 6 to less than 12 years with seasonal allergic rhinitis. Ann Allergy Asthma Immunol. 2022. doi:10.1016/j.anai.2022.07.029.

    The primary endpoint result (statistically significant rTNSS improvement, p=0.001) confirms that the fixed-dose combination produces meaningful reduction in the four core nasal symptoms in children aged 6 to 11. The effect is described as clinically meaningful and statistically significant, consistent with the language from the adult and adolescent pivotal trials.

    The safety profile is notably favorable. The total TEAE rate was actually lower with Ryaltris (10.4%) than with placebo (12.0%), which is unusual and reflects that the active treatment may reduce some symptom-related adverse events (nosebleed rate was 0.9% with Ryaltris versus 2.3% with placebo, likely because better allergen symptom control reduces nasal mucosal trauma from excessive nose-blowing and sneezing). Dysgeusia, the most characteristic adverse effect of intranasal olopatadine from its pharmacological bitter taste profile, occurred in 1.3% of active-treated children, consistent with the known tolerability profile.

    The 96.6% trial completion rate in 6-to-11-year-olds over a 14-day double-blind treatment period is also noteworthy: it reflects high acceptability of the nasal spray device and administration regimen in this age group, suggesting the once-or-twice-daily spray routine is practical in pediatric clinical practice.


    Dosing: The Pediatric Dose Is Different From the Adult Dose

    This distinction is important for prescribing accuracy and for family counseling.

    PopulationDoseFrequencyRoute
    Adults and adolescents aged 12 and older2 sprays per nostrilTwice dailyIntranasal
    Children aged 6 to less than 121 spray per nostrilTwice dailyIntranasal

    Children aged 6 to 11 receive one spray per nostril (rather than the two-spray adult dose) twice daily. At the 665 mcg/25 mcg per spray concentration, this delivers 665 mcg olopatadine and 25 mcg mometasone furoate per nostril per dose, or a total of 1,330 mcg olopatadine and 50 mcg mometasone per dosing event across both nostrils. The dose differentiation was built into the clinical trial design specifically for the pediatric age group.

    Families and prescribers should be clear that a child using a caregiver’s Ryaltris prescription intended for an adult would receive double the labeled pediatric dose. This is a practical counseling point: prescriptions for children in this age group should specify the one-spray-per-nostril dose clearly, and shared medication between family members using different doses should be avoided.


    Safety: What Prescribers and Families Need to Know

    The Ryaltris safety profile in the pediatric population was consistent with the established adult profile, with the additional pediatric-specific considerations that apply to all intranasal corticosteroid products in children.

    Potential reduction in growth velocity: Intranasal corticosteroids, including mometasone furoate, have the potential to reduce growth velocity in pediatric patients. This is a class effect of systemic and topically-absorbed corticosteroids. At the doses used in Ryaltris, intranasal mometasone has very low systemic bioavailability (less than 1%), and long-term studies with mometasone furoate nasal spray at licensed doses have not demonstrated clinically significant effects on growth velocity or hypothalamic-pituitary-adrenal axis function. However, the prescribing information includes a standard precaution to monitor growth in pediatric patients on any intranasal corticosteroid-containing product with prolonged use, and to use the minimum effective dose.

    Systemic corticosteroid warnings: The prescribing information carries standard warnings regarding: immunosuppression with possible exacerbation of existing infections (patients with active or latent infections should be monitored); hypercorticism and adrenal suppression with misuse (exceeding recommended doses or using occlusive dressings over intranasal corticosteroids); and hypersensitivity reactions.

    Local nasal effects: Epistaxis, nasal ulcerations, septal perforation, and impaired wound healing are warnings for all intranasal corticosteroid products. These are uncommon at standard doses but warrant monitoring, particularly with prolonged use. As noted in the trial data, epistaxis occurred at a lower rate with Ryaltris than with placebo in the pediatric trial (0.9% versus 2.3%), likely reflecting better symptom control rather than any specific protective effect.

    Contraindication: Ryaltris is contraindicated in patients with known hypersensitivity to mometasone furoate, olopatadine, or any component of the formulation.

    Dysgeusia: The mild bitter taste that some patients experience from intranasal olopatadine (occurring in 1.3% of pediatric trial participants) is a recognized class characteristic of some intranasal antihistamines. It is not harmful, typically brief, and rarely leads to discontinuation. Advising children that a mild taste sensation after nasal spray use is normal can reduce parent anxiety about this symptom.


    The Ryaltris Indication Picture After July 2026

    IndicationPatient populationApproval date
    Seasonal allergic rhinitisAdults and pediatric patients aged 12 and olderJanuary 13, 2022
    Seasonal allergic rhinitisChildren aged 6 to less than 12July 7, 2026

    Where Ryaltris Fits in the Pediatric SAR Treatment Landscape

    Seasonal allergic rhinitis in children aged 6 to 11 has several approved treatment options, and understanding where Ryaltris fits requires situating it against the alternatives.

    Oral second-generation antihistamines (cetirizine, loratadine, fexofenadine, levocetirizine, desloratadine): approved for children as young as 2 to 6 years depending on the product. Effective for sneezing, itching, and rhinorrhea; less effective for nasal congestion. Convenient (once-daily oral dosing) but do not provide anti-inflammatory coverage for the late-phase response.

    Intranasal corticosteroids alone (fluticasone propionate, mometasone furoate, budesonide, triamcinolone acetonide): approved for children as young as 2 to 6 years depending on the product. Effective for all four nasal symptoms including congestion; require 1 to 2 weeks to reach full effect; excellent safety profile with very low systemic bioavailability.

    Intranasal antihistamines alone (azelastine, olopatadine): faster onset of action than intranasal corticosteroids; effective for immediate symptoms; the most common adverse effect is dysgeusia.

    Fixed-dose combination (Ryaltris): now the first FDC of antihistamine plus corticosteroid approved in a single nasal spray for children aged 6 to 11. Addresses both pathways simultaneously; backed by dedicated pediatric Phase 3 data; one device simplifies the regimen.

    For children whose symptoms are mild and who respond adequately to a once-daily oral antihistamine or intranasal corticosteroid monotherapy, there is no clinical imperative to switch to a fixed-dose combination. For children with moderate-to-severe SAR who have inadequate control on monotherapy, or for children starting treatment who are likely to need both antihistamine and corticosteroid coverage, Ryaltris now provides a pediatric-labeled fixed-dose option backed by dedicated trial data in this age group.

    Marc Kikuchi, President and Business Head, North America at Glenmark, noted that the approval expands access to Ryaltris for younger children with seasonal allergic rhinitis and allows closer engagement with healthcare professionals and patients as Glenmark assumes direct commercialization of Ryaltris in the United States, which it took over on April 1, 2026.

    For related HED coverage on pediatric allergic disease and respiratory treatments, see our post on Skyrizi (risankizumab-rzaa) becoming the first IL-23 inhibitor approved for pediatric plaque psoriasis and psoriatic arthritis in children aged 6 and older and our post on Zoryve (roflumilast) cream 0.3% extending plaque psoriasis treatment to children as young as age 2.


    Sources

    Glenmark FDA approval press release: Glenmark Receives U.S. FDA Approval to Expand the Use of Ryaltris Nasal Spray for Children Aged 6 to Less Than 12 Years. Glenmark Specialty S.A. July 21, 2026.

    Drugs.com approval news: Glenmark Receives U.S. FDA Approval to Expand the Use of Ryaltris Nasal Spray for Children Aged 6 to Less Than 12 Years. drugs.com. July 21, 2026.

    HCPLive clinical summary (safety warnings, dosing, FDA expansion date): FDA Approves Ryaltris for Children Aged 6 to 11 With Seasonal Allergic Rhinitis. hcplive.com. July 2026.

    Healio (publication reference, Annals of Allergy): FDA expands Ryaltris approval to include children aged 6 to 11 years. healio.com. July 2026.

    Medical Dialogues (Marc Kikuchi quote, direct commercialization context): USFDA Approves Expanded Pediatric Use of Glenmark’s RYALTRIS Nasal Spray. medicaldialogues.in. July 2026.

    Pulmonology Advisor (rTNSS endpoint, p=0.001, TEAE data, Dr. Rahman quote): Ryaltris Safe, Effective for Pediatric Patients in Seasonal Allergic Rhinitis Trial. pulmonologyadvisor.com.

    BioSpace (original Phase 3 pediatric data announcement, primary endpoint result, TEAE rates): Glenmark Pharmaceuticals Announces Results from a Phase 3 Study of Ryaltris in Patients Aged 6 to Under 12 Years. biospace.com. May 8, 2019.

    Prenner BM et al. Annals primary publication: Prenner BM et al. Efficacy and safety of olopatadine/mometasone furoate nasal spray in pediatric patients 6 to less than 12 years old with seasonal allergic rhinitis. Ann Allergy Asthma Immunol. 2022. doi:10.1016/j.anai.2022.07.029.

    Canada Regulatory Decision Summary (rTNSS range from adult pivotal trials context): Regulatory Decision Summary for Ryaltris. Health Canada HPFB.

    Ryaltris HCP website (adult rTNSS details): About Ryaltris. us.ryaltris.com.

    Ryaltris original FDA approval (January 13, 2022): FDA approves Ryaltris (mometasone furoate and olopatadine hydrochloride) nasal spray. FDA.gov.

    Ryaltris approval history: Ryaltris FDA Approval History. drugs.com.

    Seasonal allergic rhinitis overview: Allergic Rhinitis. StatPearls. NCBI.

    Ryaltris prescribing information: RYALTRIS (olopatadine hydrochloride and mometasone furoate) Prescribing Information. Glenmark Pharmaceuticals. 2026.

    Patient resources: American Academy of Allergy, Asthma and Immunology: aaaai.org | Asthma and Allergy Foundation of America: aafa.org | Glenmark Ryaltris patient information

    Disclaimer: Health Evidence Digest provides general information about FDA approvals and health research for educational purposes. This content is not a substitute for professional medical advice. Ryaltris (mometasone furoate and olopatadine hydrochloride) contains an intranasal corticosteroid; pediatric patients on this product should be monitored for growth velocity with long-term use. The pediatric dose (1 spray per nostril twice daily) differs from the adult dose (2 sprays per nostril twice daily) and must be prescribed and communicated accurately. Treatment decisions for seasonal allergic rhinitis in children should be made in consultation with a qualified healthcare provider, such as a board-certified allergist or pediatrician.
  • Von Willebrand Disease Is the Most Common Inherited Bleeding Disorder in the World. In Young Children With Severe Disease, Prophylactic Treatment Has Lacked Any FDA-Approved Option Until Now.

    Von Willebrand Disease Is the Most Common Inherited Bleeding Disorder in the World. In Young Children With Severe Disease, Prophylactic Treatment Has Lacked Any FDA-Approved Option Until Now.

    The essentials: On July 2, 2026, the FDA approved expanded use of Wilate (von Willebrand Factor/Coagulation Factor VIII Complex Human, Octapharma) for routine prophylaxis to reduce the frequency of bleeding episodes in pediatric patients with von Willebrand disease (VWD) who are younger than 6 years of age. The prior lower age limit for the prophylaxis indication was 6 years. This makes Wilate the first and only VWF concentrate approved for prophylactic treatment across all ages and all types of VWD, from early childhood through adulthood. What this approval is: a label expansion for an established, approved product adding the under-6 prophylaxis indication. Wilate has been approved since December 2009, with the prophylaxis indication for adults and children aged 6 and older added in December 2023. The July 2, 2026 action fills the youngest pediatric gap. The WIL-33 trial: Phase 3 open-label, multicenter, international trial (NCT04953884), 12 patients, median age 2.0 years (range 1.0 to 5.0), all with severe VWD (VWF:RCo below 20%). VWD types: type 2 (4 patients; 3 type 2A, 1 type 2B); type 3 (8 patients). Dosing: 30 to 50 IU/kg administered intravenously 2 to 3 times per week over 12 months. Primary endpoint: total annualized bleeding rate (TABR) during prophylaxis. Results: mean TABR 4.6 (standard deviation 6.1) in the full analysis set; 2.7 (SD 1.8) in the per-protocol robustness set. Mean spontaneous ABR 0.9 (SD 1.2), indicating very low spontaneous bleeding on prophylaxis. 98.2% of all 56 bleeding episodes during prophylaxis were minor in nature. 95.6% of treated bleeding episodes required only 1 infusion to control. Pharmacokinetics: VWF:RCo half-life 11.7 hours, within expected ranges for this age group. No thrombotic events or FVIII accumulation. ABR comparison across age groups in the prescribing information: 4.6 (younger than 6 years) versus 3.73 (6 to 12 years) versus 4.28 (12 to younger than 17 years), showing consistency across the full pediatric range. The approval fulfills FDA postmarketing requirement number 1 established following the December 2023 prophylaxis approval. This is also the first prospective, dedicated clinical trial of VWF prophylaxis in children under 6 years worldwide: prior to WIL-33, practice guidance for this age group was extrapolated from very small case series and adult data.

    This analysis was featured by Hemostasis Today in their clinical Insight series covering FDA‑approved therapies in hematology. Read the feature: https://hemostasistoday.com/insight/melina-rodriguez-70989

    Von Willebrand disease is frequently described as the most common inherited bleeding disorder in the world, and the description is accurate. Affecting an estimated 1 in 100 to 1 in 1,000 people depending on the diagnostic threshold used, VWD is far more prevalent than hemophilia. Yet it is substantially less visible in the public discourse, receives less research funding in proportion to its disease burden, and is diagnosed and managed less systematically, particularly at the severe end of the spectrum where the clinical consequences are most significant.

    For children with severe VWD, the bleeding risk is real and starts early. Nosebleeds that last hours. Bruising from minor contact. Mucosal bleeding that does not stop without intervention. In VWD type 3, the most severe form, joint bleeds can occur and cause the same progressive joint damage seen in hemophilia. The youngest children face these risks at a time when they are developmentally most active, most prone to minor trauma, and least able to communicate pain or bleeding symptoms to caregivers.

    Evidence-based guidelines have recommended prophylactic VWF replacement therapy for patients with severe, frequent bleeds since this approach was demonstrated to reduce bleeding rates substantially in older patients and adults. But until July 2, 2026, pediatric hematologists managing children younger than 6 years with severe VWD had no FDA-approved option for routine prophylaxis. They were extrapolating from older patient data, using off-label approaches, or treating on-demand only: waiting for a bleed to occur before intervening rather than preventing it.

    Wilate (Octapharma) is now approved for this purpose. The Phase 3 WIL-33 trial, the first dedicated prospective global trial of VWF prophylaxis specifically in children under 6 years, enrolled 12 children with a median age of 2 years and demonstrated that prophylaxis was safe, well-tolerated, and associated with low bleeding rates across all VWD types. The spontaneous bleeding rate was 0.9 events per year on average, 98.2% of all bleeds during prophylaxis were minor, and no thrombotic events occurred.

    For a broader look at the pediatric rare disease approval landscape in 2026, see our post on KRESLADI (marnetegragene autotemcel), the first gene therapy for Leukocyte Adhesion Deficiency Type I.


    What Von Willebrand Disease Is: The Disease and the Protein

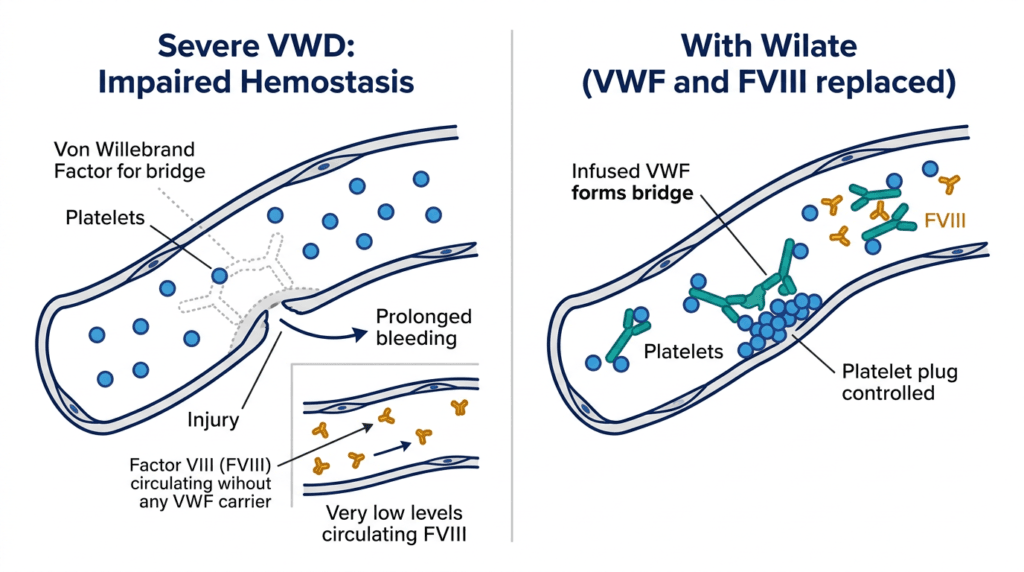
    Von Willebrand factor (VWF) is a large multimeric glycoprotein produced by endothelial cells and megakaryocytes and stored in Weibel-Palade bodies in the vascular endothelium and in platelet alpha granules. It serves two essential functions in hemostasis. The first is platelet adhesion: when a blood vessel is injured, VWF binds to exposed subendothelial collagen and then captures circulating platelets via the platelet surface receptor GPIb-IX-V, enabling primary platelet plug formation. The second is FVIII stabilization: VWF circulates in the blood as a carrier protein for coagulation factor VIII, protecting it from premature degradation and concentrating it at sites of vascular injury where coagulation is needed.

    Von Willebrand disease results from quantitative deficiency or qualitative dysfunction of VWF. The consequences of VWF deficiency are impaired platelet adhesion (reduced primary hemostasis) and reduced FVIII levels (impaired secondary coagulation), together producing a bleeding tendency that ranges from mild to severe.

    VWD is classified into three main types:

    Type 1 (approximately 60 to 80% of cases): Partial quantitative deficiency of VWF, with structurally normal protein but reduced levels. Typically mild, often not requiring regular treatment.

    Type 2 (approximately 15 to 30% of cases): Qualitative abnormality of VWF, with normal or near-normal quantities but dysfunctional protein. Divided into subtypes: type 2A (reduced high-molecular-weight multimers), type 2B (enhanced binding to platelet GPIb, which paradoxically depletes VWF and platelets), type 2M (reduced platelet-dependent function without loss of multimers), and type 2N (reduced binding affinity for FVIII).

    Type 3 (approximately 1 to 5% of cases): Severe quantitative deficiency of VWF, with virtual absence of the protein and correspondingly very low FVIII levels. This is the most severe form, producing significant spontaneous mucosal bleeding, joint bleeding, and surgical bleeding risk. The WIL-33 trial enrolled primarily type 3 patients (8 of 12) with 4 type 2 patients, reflecting the clinical priority of treating the highest-risk children.

    The clinical features of VWD reflect its primary hemostatic defect: mucosal bleeding is the dominant symptom. Nosebleeds that are prolonged, difficult to control, and recurrent. Gum bleeding. Easy bruising disproportionate to the trauma that caused it. In females with VWD, heavy menstrual bleeding is often the presenting complaint. Gastrointestinal bleeding. Postoperative bleeding. In type 3 and some type 2 subtypes, joint bleeding (hemarthrosis) occurs and can cause the same progressive arthropathy seen in hemophilia A and B.

    VWD affects approximately 3.2 million Americans at some level of severity, though most have mild type 1 disease. Approximately 20,000 to 40,000 people in the United States have type 3 or severe type 2 disease requiring regular treatment. The disease occurs across all racial and ethnic groups and affects males and females approximately equally, though females are more often diagnosed because of heavy menstrual bleeding bringing them to medical attention.


    Why Prophylaxis Matters: The Case for Prevention Over On-Demand Treatment

    The management of severe VWD has historically followed one of two approaches: on-demand treatment, in which VWF-containing product is administered only when a bleeding episode occurs or is anticipated, or prophylactic treatment, in which VWF is administered regularly to maintain hemostatic function and prevent bleeds from occurring in the first place.

    The evidence supporting prophylaxis over on-demand treatment in severe VWD is well-established for adults and older children. The prior pivotal trial program for Wilate’s prophylaxis indication (WIL-31, which supported the December 2023 approval for ages 6 and older) showed an 84% reduction in mean total annualized bleeding rate when patients switched from on-demand to prophylactic treatment. This magnitude of benefit is consistent with what has been shown for hemophilia prophylaxis: preventing bleeds prevents the cumulative damage from repeated tissue injury.

    For young children specifically, the case for early prophylaxis carries additional weight. Repeated mucosal bleeding events, even minor ones, cause pain, family anxiety, and healthcare utilization from infancy. More significantly, joint bleeding in type 3 VWD begins accumulating damage from the first events, and joint damage in childhood is progressive and irreversible. Starting prophylaxis before a pattern of bleeding-related complications develops, rather than after, is the logical application of the same principle that moved hemophilia management from on-demand to prophylaxis in the 1980s and 1990s.

    As Dr. Akshat Jain, MD, MPH, principal investigator of the WIL-33 trial, noted: prior research into prophylactic treatment for VWD has been very limited in this age group. Now there is pharmacokinetic data and clinical evidence to confirm that VWF prophylaxis is safe, effective, and well-tolerated in pediatric patients with VWD, including children younger than 6 years of age.

    Why treating VWD under age 6 has been so underdeveloped VWD in young children presents a compound challenge for clinical research. The disease is less visible than hemophilia, receives less funding, and its heterogeneity across types makes population-level study design complex. The youngest children, particularly those under 6, are also the hardest to enroll in clinical trials: they require pediatric-specific pharmacokinetic studies with appropriate dosing, they cannot report symptoms reliably, and their caregivers face significant logistical burdens in trial participation. The WIL-33 trial is, by the account of its investigators, the first prospective, dedicated global clinical trial of VWF prophylaxis specifically in children under 6 years with severe VWD. Previous practice guidance in this age range relied on extrapolation from adult and older pediatric data, small case series, and individual center experience. This evidentiary gap was the basis for the FDA’s postmarketing requirement number 1 established in 2023, requiring Octapharma to conduct and submit WIL-33 data. The July 2, 2026 approval reflects the completion of that commitment.

    What Wilate Is: The Product and Its Mechanism

    Wilate is a plasma-derived combination product containing von Willebrand factor and coagulation factor VIII, both derived from human plasma and manufactured by Octapharma using a proprietary purification process that includes two dedicated viral inactivation steps (solvent/detergent treatment and dry heat treatment at 100°C for 2 hours) and nanofiltration for pathogen safety.

    The combination of VWF and FVIII in a single product reflects the biological relationship between the two proteins. VWF carries FVIII in the circulation and protects it from premature clearance. In VWF-deficient patients, FVIII levels are also reduced (especially in type 3 VWD), because FVIII is rapidly degraded without its VWF carrier. Replacing VWF alone ultimately stabilizes endogenous and exogenous FVIII; replacing both together in a single dose addresses the immediate hemostatic deficiency more completely.

    The 1:1 ratio of VWF:RCo to FVIII in Wilate’s formulation is designed to reflect the physiological ratio of these proteins in circulation, providing balanced hemostatic support without excessive FVIII accumulation over time.

    The product’s full indication coverage after July 2026

    IndicationPatient populationApproval date
    On-demand treatment and control of bleeding episodes (VWD)Adults and pediatric patients, all agesDecember 4, 2009
    Perioperative management of bleeding (VWD)Adults and pediatric patients, all agesAugust 13, 2015
    Routine prophylaxis to reduce frequency of bleeding episodes (VWD)Adults and pediatric patients aged 6 and olderDecember 1, 2023
    On-demand treatment and control of bleeding episodes (hemophilia A)Adults and patients aged 12 and olderOctober 8, 2019
    Routine prophylaxis for bleeding episodes (hemophilia A)Adults and patients aged 12 and olderOctober 8, 2019
    Routine prophylaxis to reduce frequency of bleeding episodes (VWD)Pediatric patients younger than 6 yearsJuly 2, 2026

    The WIL-33 Trial: Full Data

    Design

    WIL-33 (NCT04953884) was a Phase 3, open-label, prospective, non-controlled, international, multicenter trial evaluating efficacy, pharmacokinetics, immunogenicity, and safety of Wilate prophylaxis in children younger than 6 years with severe VWD, defined as VWF ristocetin cofactor activity (VWF:RCo) below 20%. This is a clinically relevant threshold: VWF:RCo below 20% identifies the most severely affected patients, including virtually all type 3 patients and the most clinically significant type 2 subtypes.

    The 12 enrolled patients had a median age of 2.0 years (range 1.0 to 5.0 years), making this a genuinely very young cohort. Eight patients had type 3 VWD and four had type 2 VWD (3 type 2A and 1 type 2B). This distribution reflects the clinical priority: type 3 VWD carries the most severe bleeding risk and the most compelling need for prophylaxis.

    Wilate was administered intravenously at 30 to 50 IU/kg, two to three times per week, for 12 months. The primary endpoint was the total annualized bleeding rate (TABR) during prophylaxis, capturing spontaneous, traumatic, and other bleeds occurring between the first prophylactic dose and study completion.

    Efficacy results

    EndpointFull analysis set (n=12)Per-protocol robustness set (n=9)
    Mean total ABR (TABR)4.6 (SD 6.1)2.7 (SD 1.8)
    Mean TABR, type 2 VWD2.1 (SD 1.0)2.0 (SD 1.1)
    Mean TABR, type 3 VWD5.8 (SD 7.2)3.4 (SD 2.2)
    Mean spontaneous ABR0.9 (SD 1.2)1.0 (SD 1.3)
    Total bleeding episodes during prophylaxis56—
    Episodes classified as minor98.2% (55 of 56)—
    Treated bleeding episodes requiring only 1 infusion95.6% (43 of 45)—
    Median weekly prophylactic dose100 IU/kg (range 63 to 311, FAS); 92 IU/kg (range 63 to 130, PPR)—

    Source: WIL-33 ASH 2025 abstract. Blood. 2025;146(Supplement 1):4855. NCT04953884.

    The primary finding is a mean TABR of 4.6 in the full analysis set, falling to 2.7 in the per-protocol population that excluded patients with dosing deviations. The spontaneous ABR of 0.9 is particularly meaningful: spontaneous bleeds (those occurring without identifiable trauma or provocation) are the most clinically significant bleeding category in VWD, reflecting the adequacy of hemostatic protection during daily life. A mean of fewer than one spontaneous bleed per year in children aged 1 to 5 with severe VWD represents effective prophylactic coverage.

    An important contextual note: 22 of the 56 total bleeding episodes (39%) occurred in a single patient whose bleeds were attributed to allergic rhinitis rather than hemostatic failure. Allergic rhinitis causes mucosal inflammation that can trigger or exacerbate nosebleeds in VWD patients even on adequate prophylaxis. When this one patient’s unusual contribution to the total bleed count is considered, the underlying prophylaxis performance across the rest of the cohort is even more favorable.

    The per-protocol robustness set (n=9, excluding 3 patients with dosing deviations), with a mean TABR of 2.7 and type 3-specific rate of 3.4, likely represents the most informative dataset for predicting outcomes in a clinical practice setting where adherence to the recommended dosing protocol is achieved.

    Pharmacokinetics

    The mean VWF:RCo half-life in children under 6 was 11.7 hours, within the expected range established from data in older patients and adults and consistent with the pharmacokinetic modeling used to support the 2 to 3 times weekly dosing schedule. No clinically meaningful differences in pharmacokinetic parameters from older age groups were identified, supporting the extrapolation of the established dosing guidance to this youngest patient population.

    Comparison across age groups

    One of the most informative elements of the approved prescribing information is the cross-age ABR comparison:

    Age groupTotal ABR during prophylaxis
    Younger than 6 years (WIL-33)4.6
    6 to 12 years (WIL-31 pediatric cohort)3.73
    12 to younger than 17 years (WIL-31 adolescent cohort)4.28

    The consistency of the ABR values across age groups in the pediatric range is clinically reassuring: children under 6 on prophylaxis have bleeding rates comparable to older children on the same treatment. The slightly higher absolute ABR in the youngest group likely reflects their developmental stage (more minor trauma from active play and toddler activity) and the contribution of the single rhinitis patient, rather than a true pharmacodynamic age effect.

    Safety

    Wilate was well-tolerated in the WIL-33 population. No thrombotic events occurred. No FVIII accumulation was observed, consistent with the physiological 1:1 VWF:FVIII ratio in the product. No inhibitor formation (neutralizing antibodies against VWF or FVIII) was detected in the study period, though inhibitor development remains a potential risk of any VWF-containing product requiring ongoing monitoring.

    One patient discontinued prematurely due to adverse events that were not classified as treatment-emergent, and this patient was excluded from the per-protocol analysis set. The specific nature of these events is not described in the available publications.


    Safety: What the Prescribing Information Covers

    Wilate’s safety profile is well-characterized across its 17-year history of use since 2009, and the warnings applicable to the under-6 prophylaxis indication are consistent with the established class-level risks of plasma-derived VWF/FVIII concentrates.

    Hypersensitivity and anaphylaxis: Serious hypersensitivity reactions, including anaphylaxis, can occur with Wilate and with plasma-derived coagulation products generally. Type 2B VWD patients are particularly noted in the prescribing information because VWF infusion can cause platelet aggregation and thrombocytopenia in this subtype through enhanced binding of infused VWF to platelet GPIb. Close monitoring and platelet counts during treatment initiation are recommended for type 2B patients.

    Thromboembolic events: Thrombosis has been reported with VWF-containing products, particularly in patients with additional thrombotic risk factors or when products are used at high doses in perioperative settings. No thrombotic events occurred in WIL-33, but monitoring for signs and symptoms of thrombosis remains a prescribing information requirement.

    FVIII monitoring: Because Wilate contains FVIII in addition to VWF, plasma FVIII activity should be monitored, particularly during high-dose or prolonged use, to avoid supra-physiological FVIII levels that could increase thrombotic risk. In the WIL-33 pediatric prophylaxis setting at the recommended 30 to 50 IU/kg doses, FVIII accumulation was not observed.

    Inhibitor development: Development of neutralizing antibodies (inhibitors) against VWF or FVIII can occur with any plasma-derived or recombinant coagulation factor product, though it is less common with VWF products than with factor concentrates used in hemophilia. Immunogenicity monitoring was conducted in WIL-33 and no inhibitors were detected.

    Plasma-derived product risk: As with any product derived from human plasma, despite multiple viral inactivation and reduction steps, the theoretical risk of transmission of blood-borne infectious agents cannot be entirely eliminated. Patients and families should be counseled about this risk, which is considered very low given the manufacturing safeguards.


    What This Means for Pediatric Hematologists and Families

    For pediatric hematologists

    For pediatric hematologists managing VWD prophylaxis in children under 6, the practical implication of this approval is straightforward: children younger than 6 years with severe VWD (types 2 or 3) who have a documented history of frequent or severe bleeding episodes now have an FDA-approved option for routine prophylaxis. The WIL-33 dosing guidance, 30 to 50 IU/kg administered intravenously 2 to 3 times per week, is consistent with what has been used in older patients and can be initiated under the existing Wilate label without the need for off-label justification.

    The small sample size of WIL-33 (n=12) is the most important interpretive limitation. The trial was designed and sized as a dedicated pediatric PK and safety study, not a large-scale efficacy trial. The bleeding rate data support efficacy at a clinical level, but the confidence intervals around the mean TABR are wide given the sample size, and the contribution of one outlier patient to total bleed count is substantial. Clinical practice should incorporate this context when counseling families about expected outcomes.

    The cross-age ABR consistency in the prescribing information, showing comparable values across pediatric age groups, is the most practically useful data point for framing treatment expectations: children under 6 on Wilate prophylaxis achieve bleeding control comparable to older children on the same regimen.

    For patients with type 2B VWD specifically, the enhanced VWF-platelet interaction that characterizes this subtype warrants careful monitoring during treatment initiation, including platelet counts, consistent with the prescribing information.

    For another first-ever hematologic approval from the same August 2026 period, see our post on Imaavy (nipocalimab), the first FDA-approved treatment for warm autoimmune hemolytic anemia.

    For families

    If your child is younger than 6 and has been diagnosed with severe VWD (type 2 or type 3) and experiences frequent or significant bleeding episodes, Wilate prophylaxis is now an FDA-approved option. The discussion with your child’s pediatric hematologist about whether prophylaxis is appropriate should include your child’s bleeding history, the frequency and severity of episodes, and whether the venous access and infusion frequency (2 to 3 times weekly by intravenous infusion) are practical given your child’s age and individual circumstances.

    For very young children requiring regular IV infusions, central venous access devices (port-a-cath or implanted port) are sometimes considered to facilitate consistent treatment. This is a decision made by the treating hematologist in consultation with the family, weighing the benefits of reliable venous access against the procedural and infection risks of central line placement.

    Patient support resources for VWD families include the National Hemophilia Foundation (hemophilia.org; 1-800-42-HANDI), which provides information on both hemophilia and VWD across all ages, and the VWD Connect Foundation, which focuses specifically on the VWD community.

    For related HED coverage on rare pediatric hematologic disease and gene therapy, see our post on Casgevy (exagamglogene autotemcel) expanding to patients as young as age 2 with sickle cell disease and transfusion-dependent beta thalassemia and our post on Hympavzi (marstacimab-hncq) becoming available to children aged 6 to 11 and to patients with hemophilia inhibitors.


    Sources

    Octapharma FDA approval press release: Octapharma USA Announces Expanded FDA Approval of wilate for von Willebrand Disease Prophylaxis in Children Younger Than 6 Years. PRNewswire. July 8, 2026.

    BioSpace press release: Octapharma USA Announces Expanded FDA Approval of wilate for von Willebrand Disease Prophylaxis in Children Younger Than 6 Years. biospace.com. July 8, 2026.

    Drugs.com approval news: Octapharma USA Announces Expanded FDA Approval of Wilate for von Willebrand Disease Prophylaxis in Children Younger Than 6 Years. drugs.com. July 8, 2026.

    BioPharm International (PMR context, safety summary): FDA Approves Expanded Use of Wilate for Von Willebrand Disease Prophylaxis in Children Under Age 6. biopharminternational.com. July 2026.

    AJMC (first dedicated prospective trial context, Dr. Jain and Nielsen quotes): FDA Expands Approval for VWD Prophylaxis in Children Younger Than 6. ajmc.com. July 2026.

    Hematology Advisor (WIL-33 full data table, ABR breakdown by type, spontaneous ABR): FDA Expands Wilate Approval for VWD Prophylaxis in Children Under 6. hematologyadvisor.com. July 2026.

    Hematology Advisor (WIL-33 interim data, first prospective trial): First Prospective Global Trial Demonstrates Benefit of VWF Prophylaxis in Young Children With Severe VWD. hematologyadvisor.com. December 2025.

    Pharmacy Times (cross-age ABR comparison data from PI, treated episode infusion data): FDA Expands Wilate Approval for Routine Prophylaxis in Children Younger Than 6 With von Willebrand Disease. pharmacytimes.com. July 2026.

    Pharmacally (PMR fulfillment detail): FDA Expands WILATE Prophylaxis Approval to Children Under 6 With von Willebrand Disease. pharmacally.com. July 2026.

    Healio (Dr. Kaushal expansion statement): FDA expands Casgevy approval to children 2 years and older with sickle cell disease. healio.com.

    WIL-33 ASH 2025 abstract (Blood): Plasma-derived VWF/FVIII prophylaxis in children under 6 with VWD: First results from WIL-33. Blood. 2025;146(Supplement 1):4855. doi:10.1182/blood-2025-219636.

    WIL-33 trial registration: NCT04953884. ClinicalTrials.gov.

    VWD overview: Von Willebrand Disease. StatPearls. NCBI.

    CDC VWD facts: Von Willebrand Disease Data and Statistics. CDC.

    Original Wilate FDA approval (December 2009): FDA Approves Wilate, the First Replacement Therapy Developed Specifically for Von Willebrand Disease. Octapharma. December 2009.

    Wilate prescribing information: WILATE Prescribing Information. Octapharma. 2026.

    Wilate approval history: Wilate FDA Approval History. drugs.com.

    Patient resources: National Hemophilia Foundation: 1-800-42-HANDI | VWD Connect Foundation | Octapharma Wilate patient information

    Disclaimer: Health Evidence Digest provides general information about FDA approvals and health research for educational purposes. This content is not a substitute for professional medical advice. The WIL-33 trial enrolled 12 patients; the relatively small sample size should be considered when interpreting bleeding rate estimates and their precision. Decisions about initiating routine prophylaxis with Wilate in children younger than 6 years with von Willebrand disease should be made in consultation with a board-certified pediatric hematologist with expertise in bleeding disorders, taking into account the individual child’s VWD type, bleeding history, and the practical considerations of regular intravenous infusion in young children.
  • The World’s First CRISPR Gene Therapy Was Approved in 2023 for Patients 12 and Older. On July 1, 2026, It Became Available to Children as Young as Age Two. Here Is What That Means.

    The World’s First CRISPR Gene Therapy Was Approved in 2023 for Patients 12 and Older. On July 1, 2026, It Became Available to Children as Young as Age Two. Here Is What That Means.

    The essentials: On July 1, 2026, the FDA granted supplemental approval to Casgevy (exagamglogene autotemcel, Vertex Pharmaceuticals and CRISPR Therapeutics) for patients aged 2 years and older with either sickle cell disease (SCD) with recurrent vaso-occlusive crises (VOCs) or transfusion-dependent beta thalassemia (TDT). For the parallel story of another one-time liver-directed gene therapy approved the same month, see our post on Genglycos (pariglasgene brecaparvovec) receiving the first FDA-approved treatment for glycogen storage disease type Ia. The prior lower age limit was 12 years. Casgevy is now the first gene therapy approved for young children with SCD and the first CRISPR-based gene editing therapy to reach patients as young as age 2 in either condition. This expansion makes approximately 5,500 additional children in the United States newly eligible for this one-time therapy. What Casgevy is: an autologous CRISPR/Cas9 genome-edited hematopoietic stem cell-based gene therapy that edits the patient’s own CD34-positive stem cells ex vivo to reactivate fetal hemoglobin (HbF) production. The edited cells are infused back into the patient in a single dose following myeloablative conditioning. Fetal hemoglobin, which does not sickle and is not affected by beta-thalassemia mutations, compensates for the defective adult hemoglobin and prevents the downstream complications of both diseases. The evidence base for the age expansion rests on two distinct evidentiary components: for children aged 5 to younger than 12 years: Phase 3 CLIMB-151 (NCT05329649 for SCD) and Phase 3 CLIMB-141 (for TDT), with clinical trial data presented at EHA 2026 and simultaneously published in the New England Journal of Medicine. CLIMB-151 SCD cohort (ages 5 to 11, n=11 dosed): 100% of patients (8 of 8) with sufficient follow-up achieved VF12 (freedom from VOCs for at least 12 consecutive months); mean VOC-free duration 19.0 months (range 13.2 to 30.1 months). CLIMB-141 TDT cohort (ages 5 to 11, n=15 dosed): 100% of patients (8 of 8) with sufficient follow-up achieved TI12 (transfusion independence for at least 12 consecutive months while maintaining weighted average hemoglobin at or above 9 g/dL); mean transfusion-free duration 23.4 months (range 13.3 to 28.5 months). For children aged 2 to younger than 5 years: approval based on product characteristics and extrapolated clinical study data; CLIMB-141 and CLIMB-151 are ongoing for this youngest cohort. Long-term adult/adolescent data (CLIMB-121/CLIMB-111/CLIMB-131 as of April 2025): SCD: 100% of patients (45 of 45) achieved VF12; mean VOC-free duration 35.3 months (range 12.9 to 67.7 months). TDT: 98.2% of patients (55 of 56) achieved TI12; mean transfusion-free duration 41.4 months (range 13 to 72.3 months). Safety in children ages 5 to 11: consistent with myeloablative conditioning and autologous transplant as established in older patients. Most common grade 3 or 4 non-laboratory adverse reactions: mucositis and febrile neutropenia (SCD and TDT); decreased appetite (TDT). One death in the CLIMB-141 TDT cohort from severe veno-occlusive disease attributed to busulfan conditioning, not to Casgevy.

    Sickle cell disease and transfusion-dependent beta thalassemia are diseases that begin damaging the body in early childhood. The sickling crises that define SCD can begin as early as the first year of life. The transfusion burden of TDT typically starts before age two. Organ damage, stroke risk, growth delay, developmental disruption, and the cumulative physical and psychological toll of years of medical management all accumulate from the earliest years onward.

    For a one-time curative gene therapy, the question of when to treat matters profoundly. Treating a child at age eight who has already spent years hospitalized with pain crises and organ damage prevents further damage but cannot reverse what has already occurred. Treating a child at age two, before years of disease burden have accumulated, offers the possibility of a genuinely different life trajectory rather than a rescue from an already-damaged one.

    When the FDA first approved Casgevy in December 2023 as the world’s first CRISPR-based gene therapy, the lower age limit was 12 years. That was appropriate given the evidence available at the time. But it left the children most vulnerable to early-onset disease complications, those under 12, without access to a therapy that might prevent those complications before they developed.

    The July 1, 2026 supplemental approval, expanding Casgevy to patients aged 2 and older, is supported by Phase 3 data in children aged 5 to 11 showing the same complete response rates in SCD and TDT that have been observed in adults and adolescents. In the CLIMB-151 SCD trial, every child with sufficient follow-up was free from vaso-occlusive crises. In CLIMB-141 for TDT, every child with sufficient follow-up achieved transfusion independence. And the long-term data in adults and adolescents continues to show durable fetal hemoglobin expression and disease-free survival approaching six years in some patients.


    What Sickle Cell Disease and Transfusion-Dependent Beta Thalassemia Are

    Sickle cell disease

    Sickle cell disease is caused by a point mutation in the HBB gene encoding the beta-globin subunit of hemoglobin. The most common and severe form, sickle cell anemia (HbSS), results from homozygous inheritance of the HbS allele. The abnormal HbS hemoglobin polymerizes when deoxygenated, deforming red blood cells into the rigid, crescent-shaped “sickle” morphology that gives the disease its name.

    These sickled cells have a much shorter lifespan than normal red cells (10 to 20 days versus 120 days), causing chronic hemolytic anemia. They are also rigid and adhesive, obstructing blood flow in small vessels and triggering the vaso-occlusive crises (VOCs) that are the hallmark of severe SCD. A vaso-occlusive crisis is a period of intense pain caused by ischemia in the affected tissue. Episodes last hours to days, frequently require hospitalization and opioid analgesia, and represent the leading cause of emergency department visits and hospitalizations for patients with SCD.

    The cumulative damage from repeated VOCs is devastating. Strokes occur in approximately 11% of children with SCD before age 20 without preventive treatment. Pulmonary hypertension, kidney disease, avascular necrosis of the joints, chronic pain, and progressive organ failure accumulate over years and decades. Life expectancy, though improved by modern management, is shortened by 20 to 30 years compared to the general population.

    Approximately 100,000 Americans are affected by SCD, with the disease disproportionately impacting people of African descent. Approximately 1 in 365 Black Americans is born with SCD. The disease is also prevalent in Hispanic, Mediterranean, Middle Eastern, and South Asian populations. In the U.S., newborn screening detects SCD at birth, meaning the diagnosis is typically established in infancy.

    Transfusion-dependent beta thalassemia

    Beta thalassemia results from mutations in the HBB gene that reduce or eliminate beta-globin production. In transfusion-dependent beta thalassemia (the most severe form, also called thalassemia major), both copies of the HBB gene are severely affected, resulting in near-total absence of normal adult hemoglobin. Red blood cells are small, fragile, and short-lived. Without intervention, the resulting severe anemia is life-threatening.

    The standard treatment for TDT is lifelong regular blood transfusions, typically every 3 to 5 weeks, to maintain hemoglobin levels adequate for normal function. These transfusions come with their own burden: over years and decades, iron accumulates in tissues from transfused red blood cells, causing iron overload that damages the heart, liver, and endocrine organs. Iron chelation therapy is required alongside transfusions to manage this accumulation. The combined burden of regular transfusions, chelation therapy, and monitoring defines the life of a child with TDT from the first years onward.

    Approximately 1,000 Americans have TDT, with substantially higher global prevalence in the Mediterranean basin, the Middle East, and South and Southeast Asia.

    Why early treatment matters more than it might seem

    The case for treating SCD and TDT as early as possible is straightforward. These are not diseases that begin causing harm in adolescence. A child with severe SCD is at risk for stroke from the first years of life. A child with TDT begins accumulating iron overload from the first transfusions. The organ damage that reduces life expectancy and quality of life is cumulative. Every year of exposure to the underlying disease, without disease modification, represents irreversible damage.

    The prior lower age limit of 12 years for Casgevy meant that a child diagnosed with SCD at birth would not be eligible for this one-time curative therapy until 12 years of disease burden had accumulated. For a therapy that can potentially eliminate VOCs and transfusion dependence with a single treatment, treating earlier means preventing more cumulative harm.

    For a related example of how closing a pediatric treatment age gap changes the clinical timeline, see our post on Wilate receiving its first FDA approval for VWD prophylaxis in children under 6.


    How CRISPR/Cas9 Gene Editing Works in Casgevy: The Science

    Casgevy is the first approved therapeutic use of CRISPR/Cas9 (clustered regularly interspaced short palindromic repeats and CRISPR-associated protein 9) technology in humans. Understanding what it does requires understanding why the target it edits matters.

    The fetal hemoglobin solution

    Adult human hemoglobin consists of two alpha-globin and two beta-globin chains. The beta-globin gene is the site of mutation in both SCD and TDT. During fetal development, the body produces a different form of hemoglobin: fetal hemoglobin (HbF), which uses gamma-globin chains instead of beta-globin. HbF is the oxygen-carrying hemoglobin of the fetus and newborn; it is gradually replaced by adult hemoglobin (HbA) during the first year of life as the gamma-globin genes are switched off.

    HbF does not sickle. The alpha-gamma chains of HbF do not polymerize in response to deoxygenation the way HbS chains do. And HbF compensates for absent or deficient beta-globin in TDT, because its gamma-globin chains pair with alpha-globin to form functional hemoglobin molecules. People who retain elevated HbF production into adult life due to a genetic variant called hereditary persistence of fetal hemoglobin (HPFH) are protected from sickle cell disease symptoms even when they carry the HbS allele.

    The therapeutic insight behind Casgevy is to reactivate HbF production by editing the gene that normally switches it off. The primary switch for HbF silencing in adult life is a transcriptional repressor called BCL11A. BCL11A binds to an erythroid enhancer region and suppresses gamma-globin gene expression, reducing HbF to the low levels seen in most adults. Deleting or disrupting this BCL11A erythroid enhancer through CRISPR editing allows gamma-globin expression to resume and HbF to accumulate in adult red cells.

    The ex vivo editing process

    The gene editing in Casgevy does not occur inside the patient. It occurs in the manufacturing laboratory, and the process follows a sequence of steps:

    Mobilization and collection: The patient receives growth factor medications (G-CSF and plerixafor) to mobilize hematopoietic stem and progenitor cells (HSPCs) from the bone marrow into the peripheral blood, where they are collected by apheresis.

    Ex vivo CRISPR/Cas9 editing: The collected CD34-positive HSPCs are taken to a manufacturing facility where CRISPR/Cas9 components are delivered into the cells. The Cas9 protein, guided by a specifically designed guide RNA, creates a targeted double-strand DNA break at the BCL11A erythroid enhancer sequence. The cells’ natural DNA repair mechanism introduces small insertions or deletions at the cut site, disrupting the enhancer function and relieving BCL11A-mediated HbF repression. The editing is verified for efficiency and safety before the product is released.

    Myeloablative conditioning: Before reinfusion, the patient undergoes full myeloablative conditioning, typically high-dose busulfan chemotherapy, to clear the bone marrow and create space for the edited cells to engraft. This conditioning is the primary source of short-term treatment-related toxicity, not the gene editing itself.

    For another gene therapy that also uses myeloablative conditioning as part of the treatment process, see our post on Tregzi (marnetegragene autotemcel), the first precision-engineered cell therapy for allogeneic stem cell transplantation.

    Single-dose infusion: The edited cells are returned to the patient in a single intravenous infusion. They travel to the bone marrow, engraft, and begin producing red blood cells expressing high levels of HbF. As the edited cell population expands, HbF levels rise, sickling is prevented, and transfusion requirements fall.

    The editing is permanent. Because the modified HSPCs continue to self-renew and produce HbF-expressing red blood cells for life, the effect is lifelong, not temporary. This is why Casgevy is described as a one-time treatment rather than an ongoing therapy.


    The Clinical Evidence: What the CLIMB Trials Show

    The Casgevy clinical program is called CLIMB (CRISPR Therapeutics and Vertex-authored studies in blood diseases). The evidence base for the July 2026 age expansion comes from two distinct bodies of data.

    Adult and adolescent data (ages 12 to 35): the established foundation

    The long-term dataset from the pivotal CLIMB-111 (TDT) and CLIMB-121 (SCD) trials, with ongoing follow-up in the CLIMB-131 long-term extension study, provides the most mature evidence base for Casgevy’s durability.

    As of April 2025, the most recent data cutoff reported:

    SCD (CLIMB-121/CLIMB-131): 100% of patients (45 of 45) achieved VF12, defined as freedom from severe VOCs for at least 12 consecutive months. The mean duration of VOC-free status was 35.3 months (range 12.9 to 67.7 months). The longest-treated patients have now been VOC-free for more than 5 years.

    TDT (CLIMB-111/CLIMB-131): 98.2% of patients (55 of 56) achieved TI12, defined as transfusion independence for at least 12 consecutive months while maintaining weighted average hemoglobin at or above 9 g/dL. The mean duration of transfusion independence was 41.4 months (range 13 to 72.3 months). One patient did not achieve TI12 due to disease-related complications unrelated to the gene therapy product.

    These durability data, showing sustained HbF expression and disease-free status approaching six years in some adults, are the foundation on which the pediatric expansion rests.

    CLIMB-151 (SCD, ages 5 to 11): the primary new evidence

    CLIMB-151 (NCT05329649) is an ongoing Phase 3 open-label trial evaluating Casgevy in patients aged 2 to 11 years with SCD and recurrent VOCs. The approval for ages 5 to younger than 12 with SCD was based on data from this trial, as presented at the European Hematology Association Congress in June 2026 and simultaneously published in the New England Journal of Medicine.

    OutcomeCLIMB-151 (SCD, ages 5 to 11)
    Patients dosed11
    Patients achieving VF12 (sufficient follow-up)8 of 8 (100%)
    All patients free from any VOC after infusionYes (0 VOC events across all 11 patients post-infusion)
    Mean VOC-free duration among VF12 achievers19.0 months (range 13.2 to 30.1 months)
    Consistency with adult/adolescent profileConfirmed

    Source: CLIMB-151 data, EHA 2026 and NEJM June 2026. NCT05329649.

    Every child with sufficient follow-up was free from vaso-occlusive crises for at least a year, and no child experienced any VOC at any point after Casgevy infusion. The complete response rate is consistent with the 100% VF12 rate observed in adults and adolescents, confirming that the mechanism operates as effectively in younger children.

    CLIMB-141 (TDT, ages 5 to 11): the TDT pediatric evidence

    CLIMB-141 is the parallel trial for TDT in the 2 to 11 age range. The most recent interim data (EHA 2026) enrolled 15 children, of whom 8 had sufficient follow-up to assess TI12.

    OutcomeCLIMB-141 (TDT, ages 5 to 11)
    Patients dosed15
    Patients achieving TI12 (sufficient follow-up)8 of 8 (100%)
    All TI12 achievers maintained transfusion independence throughout follow-upYes
    Mean transfusion-free duration among TI12 achievers23.4 months (range 13.3 to 28.5 months)

    Source: CLIMB-141 interim data, EHA 2026 and NEJM June 2026.

    Again, the 100% primary endpoint achievement rate in children is consistent with the 98.2% TI12 rate observed in adults and adolescents.

    Ages 2 to younger than 5: the extrapolation basis

    For the youngest children in the expanded indication (ages 2 to younger than 5), the FDA approved Casgevy based on product characteristics and extrapolated clinical study data, not on completed efficacy data from this specific age group. CLIMB-141 and CLIMB-151 are continuing to enroll and dose children aged 2 to 4, and clinical trial data from this cohort will be forthcoming. The extrapolation approach is appropriate when the biological mechanism is age-independent (the BCL11A enhancer disruption and HbF reactivation operate the same way in a 3-year-old’s stem cells as in a 15-year-old’s), and when pharmacokinetic and safety data support equivalent treatment in the younger age range.

    This extrapolation for ages 2 to 4 is the most important interpretive nuance in this approval for clinicians counseling families. The therapy is approved, the mechanism is sound, and the 5-to-11 data strongly support efficacy across the pediatric range. But formal efficacy data specifically in the 2-to-4 age group are not yet available and will emerge from the ongoing trials.


    The Treatment Process: What Families Need to Know Before Deciding

    The decision to pursue Casgevy is among the most consequential a family of a child with SCD or TDT will face, and it is genuinely complex. This is not a medication taken daily or a treatment given in an outpatient clinic. It is a months-long medical process with significant procedural risks alongside transformative potential.

    The treatment timeline

    The full Casgevy treatment process, from initial preparation to recovery, typically spans 6 to 12 months and involves the following phases:

    Preparation and eligibility evaluation (weeks to months before treatment): Comprehensive baseline assessment including organ function, prior treatment history, infectious disease screening (hepatitis B, hepatitis C, HIV), and confirmation that the patient is clinically stable and appropriate for myeloablative conditioning. Prior hydroxyurea use is required before Casgevy treatment in SCD. Patients cannot have received prior allogeneic HSCT.

    Cell collection (mobilization and apheresis): Growth factors are administered to mobilize HSPCs into the bloodstream; cells are then collected by apheresis. Multiple collection sessions may be required.

    Manufacturing (4 to 6 months, approximately): The collected cells are shipped to Vertex/CRISPR Therapeutics’ manufacturing facility where CRISPR editing occurs. Quality testing verifies editing efficiency, sterility, and product release criteria. This step takes several months and cannot be accelerated, meaning the timing of the overall process is largely determined by manufacturing.

    Myeloablative conditioning: High-dose busulfan is administered to destroy the patient’s existing bone marrow. This is the most medically intense phase of the treatment, requiring inpatient hospitalization and carrying risks including mucositis, febrile neutropenia, veno-occlusive disease of the liver, and other conditioning-related toxicities.

    Casgevy infusion: The edited cells are returned as a single intravenous infusion. Engraftment takes several weeks, during which the patient is vulnerable to infection and requires intensive inpatient supportive care.

    Recovery and monitoring: Patients are monitored for engraftment, HbF levels, and safety outcomes over months following infusion. All patients are enrolled in CLIMB-131, the 15-year long-term follow-up study, which is a post-marketing commitment to characterize long-term safety including any potential oncogenic risk from the CRISPR editing or lentiviral vector integration (Casgevy uses CRISPR rather than a lentiviral vector, but insertional mutagenesis from off-target editing remains a theoretical risk requiring long-term surveillance).

    The risk that requires honest discussion: VOD from busulfan

    Among the most clinically significant safety findings in the CLIMB-141 TDT pediatric trial was one death, in a child with TDT who developed severe veno-occlusive disease (VOD) of the liver from busulfan conditioning. This death was attributed to the conditioning regimen rather than to Casgevy itself, and VOD is a known risk of busulfan-based myeloablative conditioning. But the event underscores that the myeloablative conditioning required before Casgevy infusion carries real and serious risks, separate from any risks attributable to the gene editing.

    Families and clinicians considering Casgevy for young children must have an explicit discussion about the risks of the conditioning regimen. VOD prophylaxis with ursodiol and careful busulfan pharmacokinetic monitoring (to individualize dosing and reduce over-exposure) are standard at experienced transplant centers and reduce but do not eliminate the risk. The treatment should be undertaken at centers with dedicated expertise in myeloablative conditioning and pediatric hematopoietic stem cell transplantation.


    Who Is Newly Eligible: Approximately 5,500 Additional U.S. Children

    Vertex estimates that approximately 5,500 additional children in the United States are now eligible for Casgevy following the age expansion. These are children aged 2 to 11 with:

    SCD with recurrent VOCs: the indication requires a documented history of recurrent severe vaso-occlusive crises. Specific thresholds (typically at least 2 protocol-defined severe VOCs in the preceding 2 years) apply and are specified in the prescribing information.

    Transfusion-dependent beta thalassemia: the indication covers patients requiring regular red blood cell transfusions to maintain adequate hemoglobin for normal function.

    Both indications carry additional eligibility requirements including negative hepatitis B, hepatitis C, and HIV screening; no prior allogeneic HSCT; clinical stability appropriate for myeloablative conditioning; and for SCD, prior or documented intolerance to hydroxyurea.

    Access and the cost reality

    Casgevy carries a list price of approximately $2.2 million per treatment. This is a one-time cost for a one-time treatment, and cost-effectiveness modeling that accounts for avoided hospitalizations, transfusions, chelation therapy, and long-term organ damage supports the economic case for the price at a population level. But the logistics of prior authorization, payer coverage, and access to qualified treatment centers create real-world barriers that do not dissolve because the therapy is clinically compelling.

    For families navigating coverage, Vertex’s patient support program and the Sickle Cell Disease Association of America and Cooley’s Anemia Foundation both maintain access resources. Medicaid covers Casgevy in most states for eligible patients, which is significant given the disproportionate enrollment of SCD patients in Medicaid programs.

    The therapy is available exclusively at authorized treatment centers. Finding a qualified center experienced in both pediatric stem cell transplantation and gene therapy is a prerequisite for access. Vertex maintains a directory of authorized treatment centers on casgevy.com.

    Dr. Megha Kaushal, acting deputy director of the Office of Therapeutic Products at FDA’s Center for Biologics Evaluation and Research, noted that these disorders carry a heavy burden for children and their families, affecting growth, development, and long-term health in profound ways. The FDA’s approval, she said, provides pediatric patients as young as age 2 with access to a critical additional treatment option.

    For the complete 2026 gene therapy approval picture, also see our posts on Casgevy’s companion rare pediatric disease approval, Genglycos for GSD1a and Pasatru (garetosmab) for fibrodysplasia ossificans progressiva.

    For families living with SCD or TDT, the Sickle Cell Disease Association of America (sicklecelldisease.org; 1-800-421-8453) and the Thalassemia International Federation maintain current patient resources, treatment center directories, and peer support networks. In the United States, Cooley’s Anemia Foundation (thalassemia.org; 1-800-522-7222) provides comprehensive TDT support.


    Sources

    FDA supplemental approval announcement: FDA Approves First Gene Therapy for Young Children with Sickle Cell Disease. FDA.gov. July 1, 2026.

    Vertex FDA approval press release: Vertex Announces US FDA Approval for Expanded Use of CASGEVY for the Treatment of People Ages 2 Years and Older With Sickle Cell Disease or Transfusion-Dependent Beta Thalassemia. BusinessWire. July 1, 2026.

    Vertex newsroom: Vertex Announces US FDA Approval for Expanded Use of CASGEVY. news.vrtx.com. July 1, 2026.

    Drugs.com approval news: Vertex Announces FDA Approval for Expanded Use of Casgevy for the Treatment of People Ages 2 Years and Older With Sickle Cell Disease or Transfusion-Dependent Beta Thalassemia. drugs.com. July 1, 2026.

    CLIMB-151 and CLIMB-141 EHA 2026 and NEJM publication (ages 5 to 11): Vertex Presents New Data on CASGEVY, Including First European Presentation of Data in Children Ages 5–11, at the European Hematology Association Congress. Vertex/BusinessWire. June 10, 2026.

    CLIMB-151 and CLIMB-141 ASH 2025 (ages 5 to 11, first-ever pediatric data): Vertex Presents New Data on CASGEVY, Including First-Ever Data in Children Ages 5-11 Years, at the American Society of Hematology Annual Meeting. Vertex/BusinessWire. December 6, 2025.

    CLIMB-151 trial registration (SCD ages 2 to 11): NCT05329649. ClinicalTrials.gov.

    CLIMB-131 long-term follow-up trial registration: NCT04208529. ClinicalTrials.gov.

    HCPLive (first CRISPR therapy for ages 2+ context): FDA Expands Exa-Cel Gene Therapy Approval to Children 2 Years and Up With SCD or beta-Thalassemia. hcplive.com. July 2026.

    Pharmacy Times (VF12 ages 5 to 11 complete data, busulfan VOD death detail): FDA Expands Casgevy Approval to Children as Young as 2 Years With Sickle Cell Disease or Transfusion-Dependent beta-Thalassemia. pharmacytimes.com. July 2026.

    Clinical Advisor and Hematology Advisor (age 2 to 4 extrapolation clarification): Gene Therapy Casgevy Approved for Younger SCD and TDT Patients. clinicaladvisor.com. July 2026.

    Healio (Dr. Kaushal FDA quote): FDA expands Casgevy approval to children 2 years and older with sickle cell disease. healio.com. July 2026.

    Casgevy original December 2023 FDA approval: FDA approves exagamglogene autotemcel for sickle cell disease. FDA.gov.

    CRISPR/Cas9 mechanism overview: CRISPR/Cas9 Gene Editing Technology. PMC6107701.

    SCD overview: Sickle Cell Disease. StatPearls. NCBI.

    Beta thalassemia overview: Beta Thalassemia. StatPearls. NCBI.

    SCD data: CDC Sickle Cell Disease Data.

    Casgevy prescribing information: CASGEVY (exagamglogene autotemcel) Prescribing Information. Vertex Pharmaceuticals. 2026.

    Casgevy approval history: Casgevy FDA Approval History. drugs.com.

    Patient resources: Sickle Cell Disease Association of America: 1-800-421-8453 | Cooley’s Anemia Foundation: 1-800-522-7222 | Thalassemia International Federation | Vertex Casgevy patient support | National Heart, Lung, and Blood Institute: Sickle Cell Disease

    Disclaimer: Health Evidence Digest provides general information about FDA approvals and health research for educational purposes. This content is not a substitute for professional medical advice. Casgevy (exagamglogene autotemcel) is a complex gene therapy requiring myeloablative conditioning and administration at specialized authorized treatment centers. The approval for children aged 2 to younger than 5 years is based on product characteristics and extrapolated data; direct efficacy data in this youngest cohort are forthcoming from ongoing trials. The treatment carries serious risks including those related to myeloablative conditioning. All decisions about gene therapy for sickle cell disease or transfusion-dependent beta thalassemia must be made in close collaboration with a board-certified hematologist and a center with expertise in pediatric hematopoietic stem cell transplantation and gene therapy.
  • PCSK9 Inhibitors Have Been Among the Most Effective Cholesterol Drugs Ever Developed. They Have Also Required Injections Every Two to Four Weeks. Lipfendra Is the First One That Is Just a Pill.

    PCSK9 Inhibitors Have Been Among the Most Effective Cholesterol Drugs Ever Developed. They Have Also Required Injections Every Two to Four Weeks. Lipfendra Is the First One That Is Just a Pill.

    The essentials: On July 16, 2026, the FDA approved Lipfendra (enlicitide, Merck) 20 mg tablets as an adjunct to diet and exercise to reduce low-density lipoprotein cholesterol (LDL-C) in adults with hypercholesterolemia, including heterozygous familial hypercholesterolemia (HeFH). Lipfendra is the first FDA-approved oral PCSK9 inhibitor in history. Every other approved PCSK9 inhibitor is administered by subcutaneous injection (evolocumab/Repatha, alirocumab/Praluent) or intravenous infusion (inclisiran/Leqvio). What enlicitide is: a novel macrocyclic peptide that binds directly to PCSK9 and prevents it from binding to LDL receptors on liver cells, allowing more LDL receptors to remain on the cell surface and remove more LDL-C from the blood. The macrocyclic peptide format is what enables oral bioavailability that conventional peptide PCSK9 inhibitors cannot achieve. Dosing: 20 mg once daily by mouth. No food restriction, no injection, no clinic visit required for administration. The clinical basis: two pivotal Phase 3 trials. CORALreef Lipids (NCT05952856, n=2,912, adults with hypercholesterolemia at elevated ASCVD risk on stable statin therapy): placebo-adjusted LDL-C reduction of 55.8% at week 24 (95% CI minus 60.9 to minus 50.7; p less than 0.001); reduction sustained at 47.6 percentage points versus placebo at week 52. 70.3% of patients achieved LDL-C below 70 mg/dL with at least 50% reduction; 67.5% achieved LDL-C below 55 mg/dL with at least 50% reduction. Broad lipid benefits: non-HDL-C down 53.4 percentage points; apolipoprotein B (ApoB) down 50.3 percentage points; lipoprotein(a) down 28.2 percentage points (median) versus placebo at week 24. CORALreef HeFH (NCT05952869, n=303, adults with HeFH on stable statin therapy): placebo-adjusted LDL-C reduction of 59% at week 24. Mean baseline LDL-C 119 mg/dL. Safety: in CORALreef Lipids, adverse event frequency was similar between enlicitide and placebo. In CORALreef HeFH, the most common adverse reactions occurring at higher frequencies than placebo were diarrhea (7% versus 2%) and dizziness (9% versus 4%). Adherence in both trials: 97% adherence to study intervention; 96% adherence to dosing instructions, among the highest adherence rates reported in any cardiovascular outcomes trial program. The critical unanswered question: cardiovascular outcomes. Does LDL-C lowering with enlicitide reduce heart attacks, strokes, and cardiovascular death? The large CORALreef Outcomes trial (NCT06008756, over 14,500 patients enrolled, projected completion December 2029) will answer this. Without those data, the cardiovascular event reduction benefit is inferred from the class effect of injectable PCSK9 inhibitors rather than directly demonstrated for enlicitide.

    The injectable PCSK9 inhibitor story has been one of the most impressive in cardiovascular medicine to treat low-density lipoprotein cholesterol. When evolocumab and alirocumab received FDA approval in 2015, they produced LDL-C reductions in the range of 50 to 60% on top of maximally tolerated statin therapy, far exceeding what any other oral lipid-lowering agent could achieve. The subsequent cardiovascular outcomes trials, FOURIER for evolocumab and ODYSSEY OUTCOMES for alirocumab, confirmed that these LDL reductions translated into meaningful reductions in heart attacks, strokes, and cardiovascular death. The mechanism worked exactly as predicted.

    But the drugs required injections. Subcutaneous self-injection every two weeks for evolocumab and alirocumab, or an intravenous infusion every six months for inclisiran. For many of the patients who would benefit most from PCSK9 inhibition, including patients already managing complex medication regimens for established cardiovascular disease, this route-of-administration requirement was the primary reason they were not using the drug. Studies of real-world PCSK9 inhibitor prescribing consistently showed that injection burden, needle anxiety, and the practical difficulty of adding a biologic self-injection routine to an already complex daily regimen contributed to low adoption in eligible populations.

    Lipfendra (enlicitide, Merck) is the first oral PCSK9 inhibitor. Not a modified injectable. Not a new small-molecule working through a different mechanism. A once-daily tablet that directly inhibits PCSK9 with the same mechanism as the approved injectables, producing LDL-C reductions of 56 to 59% in Phase 3 trials, and doing so with an adverse event profile that was essentially indistinguishable from placebo in the large general population trial.

    The most important limitation is the one that matters most: cardiovascular outcomes data. Whether enlicitide reduces heart attacks and strokes has not yet been established in a completed randomized trial. The LDL-C reduction is real, large, and consistent. Whether it translates into event reduction, as the class effect strongly predicts it should, will be confirmed by CORALreef Outcomes in 2029.


    What LDL Cholesterol Is and Why Reducing It Matters

    Low-density lipoprotein cholesterol is the primary atherogenic lipoprotein in human blood. LDL particles carry cholesterol from the liver to peripheral tissues, and when LDL-C levels are elevated, excess LDL particles deposit in arterial walls, where they are oxidized and trigger the inflammatory cascade that drives plaque formation. This atherosclerotic process underlies the most common causes of heart attack and stroke, collectively known as atherosclerotic cardiovascular disease (ASCVD).

    The relationship between LDL-C and ASCVD risk is one of the most robust dose-response relationships in medicine, established through decades of Mendelian randomization studies, statin trials, and PCSK9 inhibitor outcomes trials. The Cholesterol Treatment Trialists’ Collaboration meta-analysis of over 170,000 participants in statin trials found that each 1 mmol/L (approximately 38.7 mg/dL) reduction in LDL-C reduces the risk of major vascular events by approximately 22%. Lower is better, with no observed threshold at which further LDL-C reduction stops providing benefit.

    Current cardiovascular guidelines from the American College of Cardiology and American Heart Association define LDL-C targets based on individual ASCVD risk: below 70 mg/dL for patients with established ASCVD, and below 55 mg/dL for very high-risk patients including those with multiple ASCVD events or ASCVD plus additional high-risk features. Many patients on maximally tolerated statin therapy do not reach these targets, particularly those with familial hypercholesterolemia or those who are statin-intolerant.


    What PCSK9 Is and How Inhibiting It Works

    PCSK9 (proprotein convertase subtilisin/kexin type 9) is a liver-produced protein that serves as a natural regulator of LDL receptors. LDL receptors sit on the surface of liver cells and capture circulating LDL-C particles, drawing them inside the cell for processing. PCSK9 binds to LDL receptors and directs them to be degraded inside the cell rather than recycled back to the cell surface. When PCSK9 levels are high, fewer LDL receptors are available to clear LDL-C, so blood LDL-C levels rise. When PCSK9 is blocked, more LDL receptors return to the cell surface, LDL-C clearance increases, and blood LDL-C levels fall substantially.

    The importance of PCSK9 in LDL-C regulation was first recognized through the discovery of gain-of-function mutations in the PCSK9 gene that cause severe familial hypercholesterolemia, and loss-of-function mutations that produce lifelong LDL-C levels 28% lower than average and a corresponding 88% reduction in coronary heart disease risk over a lifetime. Human genetics established the principle; the therapeutic agents confirmed it at scale.

    The approved injectable PCSK9 inhibitors, evolocumab and alirocumab, are large monoclonal antibody proteins that bind to PCSK9 in the bloodstream and prevent it from interacting with LDL receptors. Inclisiran is an RNA interference agent that reduces PCSK9 production in the liver. All three require non-oral administration because of their molecular size or chemistry.

    Enlicitide takes a fundamentally different approach at the molecular level, and that difference is what makes oral delivery possible.


    What a Macrocyclic Peptide Is and Why It Changes Everything

    The challenge with making a PCSK9 inhibitor orally available is the same challenge that has historically prevented oral biologics: large molecules are degraded in the gastrointestinal tract before they can be absorbed into the bloodstream, and even when absorption occurs, the efficiency is too low to achieve therapeutic concentrations.

    Enlicitide is a macrocyclic peptide, a specific class of molecules that occupies a chemical space between conventional small molecules and large biologics. Macrocyclic peptides are larger than typical small-molecule drugs but far smaller than monoclonal antibodies. Their defining feature is a cyclic (ring) structure: the ends of the peptide chain are connected to each other, creating a closed loop rather than an open linear chain.

    This cyclic architecture is what enables oral bioavailability for a PCSK9 binding agent. The ring structure provides several properties that linear peptides lack:

    The cyclic conformation is more rigid and compact, reducing the peptide’s surface area exposure to the digestive enzymes that would otherwise rapidly cleave it. The ring also reduces the number of exposed hydrogen bond donors and acceptors, which improves membrane permeability and allows the molecule to cross intestinal epithelial cells more efficiently. And the specific chemical modifications incorporated into enlicitide’s structure (it is supplied as enlicitide decanoate, meaning a fatty acid ester modification that further improves oral absorption) optimize the pharmacokinetic profile for once-daily dosing.

    The result is a molecule that, despite binding the same PCSK9 protein target as the large injectable antibodies, is small enough and chemically stable enough to survive gastric acid, be absorbed through the intestinal wall, and achieve blood concentrations sufficient to meaningfully inhibit PCSK9 activity throughout a 24-hour dosing interval.

    As Merck’s president of Research Laboratories, Dr. Dean Y. Li, described it: enlicitide was designed to deliver antibody-like efficacy in the form of a once-daily oral tablet, leveraging macrocyclic peptide technology to achieve what conventional peptide chemistry could not.


    The CORALreef Trials: Complete Data

    CORALreef Lipids (NCT05952856): The Primary Pivotal Trial

    CORALreef Lipids was a Phase 3, multicenter, randomized, double-blind, placebo-controlled trial conducted across 168 sites in 14 countries. It enrolled 2,912 adults aged 18 years and older with hypercholesterolemia and either a history of a major ASCVD event (with LDL-C at or above 55 mg/dL) or intermediate-to-high risk for a first ASCVD event (with LDL-C at or above 70 mg/dL). All patients were required to be on stable lipid-lowering therapy including at least a moderate- or high-intensity statin, or have documented statin intolerance.

    Participants were randomized 2:1 to enlicitide 20 mg orally once daily (n=1,942) or placebo (n=970) for 52 weeks. The primary endpoint was mean percent change in LDL-C from baseline at week 24. The primary results were published in the New England Journal of Medicine in 2026.

    EndpointEnlicitidePlaceboDifference/result
    Mean percent change in LDL-C at week 24 (primary)Approximately minus 57% from baselineApproximately minus 1% from baselinePlacebo-adjusted minus 55.8 percentage points (95% CI minus 60.9 to minus 50.7); p less than 0.001
    Mean percent change in LDL-C at week 52SustainedSustainedPlacebo-adjusted minus 47.6 percentage points; p less than 0.001
    Non-HDL-C change at week 24——Placebo-adjusted minus 53.4 percentage points
    ApoB change at week 24——Placebo-adjusted minus 50.3 percentage points
    Lipoprotein(a) change at week 24——Placebo-adjusted minus 28.2 percentage points (median)
    LDL-C below 70 mg/dL plus at least 50% reduction at week 2470.3%—Guideline goal achievement (ACC/AHA secondary prevention target)
    LDL-C below 55 mg/dL plus at least 50% reduction at week 2467.5%—Guideline goal achievement (very high risk target)
    Treatment adherence97%97%Comparable, exceptionally high

    Source: CORALreef Lipids NEJM 2026 publication; Merck press release November 8, 2025.

    The 55.8 percentage-point placebo-adjusted LDL-C reduction at 24 weeks is clinically comparable to the LDL-C reductions achieved by injectable PCSK9 inhibitors in their pivotal trials (evolocumab reduced LDL-C by approximately 59% in FOURIER; alirocumab by approximately 62% in ODYSSEY OUTCOMES). Achieving this magnitude of reduction from an oral daily tablet represents a genuine pharmacological advance.

    The guideline goal attainment numbers are particularly meaningful. More than two-thirds of patients (67.5%) on enlicitide achieved both LDL-C below 55 mg/dL and at least a 50% reduction from baseline, meeting the most stringent ACC/AHA guideline target for very high-risk patients. This degree of goal attainment is not achievable with statins alone in most high-risk patients and has historically required injectable PCSK9 inhibitors to reach reliably.

    The week 52 data (47.6 percentage-point reduction versus placebo) shows some attenuation from the week 24 peak, a common finding in lipid-lowering trials that reflects a combination of regression to the mean and possibly some pharmacokinetic variability over extended follow-up. The reduction remains clinically substantial at one year.

    CORALreef HeFH (NCT05952869): The Familial Hypercholesterolemia Trial

    CORALreef HeFH was a Phase 3, randomized, double-blind, placebo-controlled trial enrolling 303 adults with heterozygous familial hypercholesterolemia who had a history of or were at risk for major ASCVD events, on stable background statin therapy. Patients were randomized 2:1 to enlicitide 20 mg daily or placebo. The mean baseline LDL-C was 119 mg/dL, reflecting the high residual LDL-C burden that persists in HeFH patients despite maximally tolerated statin therapy.

    EndpointResult
    Placebo-adjusted LDL-C change at week 24 (primary)Minus 59%
    LDL-C change at week 52Statistically significant (maintained)
    Non-HDL-C, ApoB, Lp(a) at week 24Statistically significant improvements (all secondary endpoints met)
    Treatment adherence97%

    The 59% LDL-C reduction in HeFH patients on top of existing statin therapy represents a clinically transformative magnitude of effect for this population. HeFH, caused by loss-of-function mutations in the LDL receptor gene or other genes in the LDL-C clearance pathway, drives markedly elevated LDL-C from birth and substantially increases the lifetime risk of premature ASCVD events. Many HeFH patients cannot achieve guideline-recommended LDL-C targets even on high-intensity statins plus ezetimibe, and have historically required injectable PCSK9 inhibitors to do so. An oral once-daily alternative that produces comparable LDL-C reduction is a meaningful practical advance for this population.


    The PCSK9 Inhibitor Landscape After July 2026

    DrugCompanyMechanismRouteDosing frequencyLDL-C reduction
    Repatha (evolocumab)AmgenAnti-PCSK9 monoclonal antibodySC injectionEvery 2 weeks or monthlyApproximately 59%
    Praluent (alirocumab)Sanofi/RegeneronAnti-PCSK9 monoclonal antibodySC injectionEvery 2 weeks or monthlyApproximately 62%
    Leqvio (inclisiran)NovartissiRNA targeting PCSK9 mRNASC injection (clinician-administered)Twice yearlyApproximately 50 to 52%
    Lipfendra (enlicitide)MerckMacrocyclic peptide binding PCSK9Oral tabletOnce dailyApproximately 56 to 59%

    Lipfendra is not more effective than the injectable PCSK9 inhibitors by LDL-C reduction alone. The magnitude of LDL-C lowering is comparable across the class. What Lipfendra provides is route-of-administration convenience that fundamentally changes the accessibility and scalability of PCSK9 inhibition.


    The Unanswered Question: Cardiovascular Outcomes

    The most important clinical limitation of the July 16, 2026 approval is the one that cannot yet be answered: whether LDL-C reduction with enlicitide translates into fewer heart attacks, strokes, and cardiovascular deaths.

    For the injectable PCSK9 inhibitors, this question has been answered:

    The FOURIER trial (evolocumab, n=27,564) showed a 15% relative risk reduction in the composite primary endpoint of cardiovascular death, heart attack, stroke, hospitalization for unstable angina, or coronary revascularization (HR 0.85; 95% CI 0.79 to 0.92; p less than 0.001).

    The ODYSSEY OUTCOMES trial (alirocumab, n=18,924) showed a 15% relative risk reduction in the primary composite endpoint of death from coronary heart disease, nonfatal heart attack, ischemic stroke, or unstable angina requiring hospitalization (HR 0.85; 95% CI 0.78 to 0.93; p less than 0.001).

    Both trials also showed dose-dependent mortality benefits in certain high-risk subgroups with very high baseline LDL-C.

    Enlicitide does not have this data yet. The CORALreef Outcomes trial (NCT06008756), with over 14,500 participants enrolled, is the ongoing cardiovascular outcomes study. It has a projected completion date of December 2029. Until those data are available, the cardiovascular event reduction benefit of enlicitide is inferred from the class effect of PCSK9 inhibition and from the known relationship between LDL-C reduction and ASCVD event reduction, both of which are scientifically robust. But they are inferences, not demonstrated outcomes for this specific drug.

    As the AJMC noted in coverage of the approval, the degree to which the reduction in LDL cholesterol levels with enlicitide will translate into a reduction in cardiovascular events is being tested in the ongoing CORALreef Outcomes trial, with a projected completion date of December 2029.

    For patients and prescribers making treatment decisions now: the LDL-C reduction is established and clinically comparable to the injectable class. The cardiovascular outcomes evidence is pending but scientifically predicted. The FDA’s approval of enlicitide based on LDL-C reduction as the primary efficacy endpoint, while CORALreef Outcomes completes, follows the same standard applied to the injectable PCSK9 inhibitors at their initial approvals.


    Safety: What the CORALreef Data Shows

    The safety profile of enlicitide in the pivotal trials is one of the most favorable features of the approval. In CORALreef Lipids, the large general population trial, adverse event frequency was essentially identical between enlicitide and placebo. Discontinuation due to adverse events was similar across arms. No class-level safety concern emerged from this 2,912-patient, 52-week dataset.

    In CORALreef HeFH, the HeFH-specific trial, two adverse reactions occurred at modestly higher frequencies with enlicitide than placebo:

    • Diarrhea: 7% (enlicitide) versus 2% (placebo)
    • Dizziness: 9% (enlicitide) versus 4% (placebo)

    Both were predominantly mild in severity, and discontinuation rates due to adverse events were similar between groups despite the higher rate of these events. The mechanism underlying the diarrhea and dizziness signals in the HeFH population but not the general population trial is not fully characterized; it may reflect the smaller sample size of CORALreef HeFH making individual adverse event comparisons more variable, or it may reflect the HeFH population’s distinct disease and comorbidity profile.

    No hepatotoxicity signal, no significant renal signal, no immune-mediated adverse events, and no injection site reactions (because there are no injections) were reported. The oral route eliminates the local tolerability issues that affect a proportion of patients on subcutaneous injectable PCSK9 inhibitors.

    Key safety information from the Lipfendra prescribing information:

    No boxed warning. The prescribing information requires disclosure of the most common adverse reactions occurring at higher rates than placebo (diarrhea and dizziness, from the HeFH trial). The absence of a boxed warning and the favorable adverse event profile in the large general population trial reflect a genuinely clean safety signal across 52 weeks in nearly 3,000 patients.

    Embryo-fetal toxicity language is included in the label because all lipid-lowering therapies carry a contraindication in pregnancy due to the theoretical risk from lipid pathway perturbation and the known safety of discontinuing lipid-lowering therapy for the duration of pregnancy in most patients.


    What This Means for Patients and Prescribers

    For patients with high LDL-C who have not been prescribed a PCSK9 inhibitor

    Several well-established barriers have limited PCSK9 inhibitor prescribing despite their efficacy. Insurance prior authorization requirements have been restrictive and time-consuming. Injection anxiety and the practical burden of self-injection have deterred many patients. And in some cases, the specialty pharmacy workflow required for injectable biologics has added friction to prescribing.

    Lipfendra is a tablet. It does not require a specialty pharmacy in the same way. It does not require injection training. It can be prescribed by a primary care physician without the same hurdles as a biologic self-injection device. Whether these practical advantages translate into substantially higher PCSK9 inhibitor uptake in eligible patients will depend heavily on formulary placement, prior authorization criteria, and pricing, none of which have been fully established at the time of writing.

    For patients already on injectable PCSK9 inhibitors who are satisfied with their treatment and tolerating their regimen well: the LDL-C reduction with enlicitide is comparable but not superior. There is no clinical imperative to switch for efficacy reasons. Patients who have struggled with injections, have injection site reactions, or who have found the biologic self-injection workflow burdensome are candidates for a conversation about switching.

    For patients with HeFH

    HeFH is a genetic condition affecting approximately 1 in 250 people, yet the majority of affected individuals are undiagnosed, and among those who are diagnosed and treated, many do not reach guideline-recommended LDL-C targets on statins alone. The 59% LDL-C reduction from enlicitide on top of stable statin therapy brings most HeFH patients to within or near guideline targets with a once-daily pill, a meaningful practical change from the every-2-week or monthly self-injection schedule of injectable PCSK9 inhibitors.

    For prescribers

    The conversation about PCSK9 inhibitor therapy for eligible patients is now different. The oral option removes several of the friction points that have historically limited uptake. The LDL-C reduction magnitude is comparable to the injectable class. The safety profile through 52 weeks is favorable. The cardiovascular outcomes data are pending but the class effect is established.

    The CORALreef Outcomes results, expected around 2029, will be one of the most closely watched trials in cardiovascular medicine. If the event reduction mirrors what was seen with evolocumab in FOURIER and alirocumab in ODYSSEY OUTCOMES, the case for wide uptake of oral PCSK9 inhibition will be definitive.

    Dr. Ann Marie Navar, a cardiologist at UT Southwestern Medical Center, noted that for the first time, patients have an oral PCSK9 inhibitor for LDL lowering, a significant development for a class that has struggled with adoption despite proven efficacy.

    For related HED coverage on cardiovascular risk and lipid management, see our post on Awiqli (insulin icodec-abae), the first once-weekly basal insulin approved for adults with type 2 diabetes and our coverage of the daraxonrasib RASolute 302 data from ASCO 2026 showing a 60% reduction in risk of death in previously treated metastatic pancreatic cancer.


    Sources

    FDA approval announcement: FDA approves first oral therapy that inhibits proprotein convertase subtilisin/kexin type 9 (PCSK9) to lower bad cholesterol in adults with high cholesterol. FDA.gov. July 16, 2026.

    Merck FDA approval press release: Merck’s Lipfendra (enlicitide) is the First and Only Once-Daily Oral PCSK9 Inhibitor Approved by the U.S. FDA to Reduce LDL-C in Adults with Hypercholesterolemia. Merck. July 16, 2026.

    Drugs.com approval news: FDA Approves Lipfendra (enlicitide) Oral PCSK9 Inhibitor to Reduce LDL-C in Adults with Hypercholesterolemia. drugs.com. July 16, 2026.

    AJMC competitive landscape and Dr. Navar quote: FDA Approves Enlicitide, First Oral PCSK9 for High Cholesterol. ajmc.com. July 2026.

    AJMC CORALreef Lipids detailed data: Oral PCSK9 Inhibitor Enlicitide Lowers LDL by 57% at 24 Weeks. ajmc.com.

    Patient Care Online (HeFH baseline LDL-C, adverse reactions): FDA Approves First Oral PCSK9 Inhibitor to Reduce LDL-C in Adults With Hypercholesterolemia. patientcareonline.com. July 2026.

    Pharmacy Times (CORALreef Lipids full data, mechanism detail): Enlicitide Meaningfully Lowers LDL-C at 24 Weeks in Patients At Risk for ASCVD Events. pharmacytimes.com.

    Biopharma News / AppliedXL (CORALreef design, 2:1 randomization, 168 sites): FDA approves Merck’s oral PCSK9 inhibitor Lipfendra for high cholesterol. appliedxl.com. July 2026.

    Merck CORALreef Lipids data press release (November 8, 2025): Merck’s Enlicitide Decanoate Significantly Reduced LDL-C in Phase 3 CORALreef Lipids Trial. BusinessWire. November 8, 2025.

    Merck CORALreef HeFH data press release (November 9, 2025): Merck’s Enlicitide Decanoate Significantly Reduced LDL-C in Adults with HeFH in Phase 3 CORALreef HeFH Trial. Merck. November 9, 2025.

    The Cardiology Advisor (macrocyclic peptide mechanism detail): Oral PCSK9 Inhibitor Enlicitide Reduces LDL-C in Adults With Hypercholesterolemia. thecardiologyadvisor.com.

    FCS Hematology Oncology Review (goal attainment data detail): CORALreef Lipids data table.

    Family Heart Foundation (HeFH patient resources): FDA Approves Merck’s LIPFENDRA as First Once-Daily Oral PCSK9 Inhibitor. familyheart.org. July 2026.

    CORALreef Lipids trial registration: NCT05952856. ClinicalTrials.gov.

    CORALreef HeFH trial registration: NCT05952869. ClinicalTrials.gov.

    CORALreef Outcomes trial registration: NCT06008756. ClinicalTrials.gov.

    CORALreef Lipids primary NEJM publication: CORALreef Lipids. New England Journal of Medicine. 2026.

    FOURIER cardiovascular outcomes trial (evolocumab): Sabatine MS et al. Evolocumab and Clinical Outcomes in Patients with Cardiovascular Disease. NEJM. 2017;376(18):1713-1722.

    ODYSSEY OUTCOMES trial (alirocumab): Schwartz GG et al. Alirocumab and Cardiovascular Outcomes after Acute Coronary Syndrome. NEJM. 2018;379(22):2097-2107.

    PCSK9 biology overview: PCSK9 and LDL Receptor Regulation. PMC9290282.

    ACC/AHA Cholesterol Guidelines (LDL targets): Grundy SM et al. 2018 AHA/ACC/AACVPR/AAPA/ABC/ACPM/ADA/AGS/APhA/ASPC/NLA/PCNA Guideline on the Management of Blood Cholesterol. JACC. 2019.

    LDL-C and ASCVD risk (NHLBI): LDL Cholesterol. NHLBI.

    Lipfendra prescribing information: LIPFENDRA (enlicitide) Prescribing Information. Merck Sharp and Dohme LLC. 2026.

    Lipfendra approval history: Lipfendra FDA Approval History. drugs.com.

    Patient resources: American Heart Association: Know Your Numbers | Family Heart Foundation (HeFH resources) | National Lipid Association | Merck Lipfendra patient support

    Disclaimer: Health Evidence Digest provides general information about FDA approvals and health research for educational purposes. This content is not a substitute for professional medical advice. Lipfendra (enlicitide) is approved to reduce LDL-C; it has not yet been established in a completed randomized trial that enlicitide reduces cardiovascular events such as heart attacks and strokes. The CORALreef Outcomes cardiovascular trial is ongoing with results expected around 2029. All decisions about lipid-lowering therapy should be made in consultation with a qualified healthcare provider who can evaluate individual ASCVD risk, lipid levels, current medications, and treatment goals.
  • Sixty Percent of HR+/HER2- Breast Cancer Patients Who Progress on CDK4/6 Inhibitors Have PIK3CA Wild-Type Disease. Until Now, They Had No Approved Targeted Therapy. Revtorpyk Just Changed That.

    Sixty Percent of HR+/HER2- Breast Cancer Patients Who Progress on CDK4/6 Inhibitors Have PIK3CA Wild-Type Disease. Until Now, They Had No Approved Targeted Therapy. Revtorpyk Just Changed That.

    The essentials: On July 14, 2026, the FDA approved Revtorpyk (gedatolisib, Celcuity Inc.) in combination with fulvestrant, with or without palbociclib (Ibrance), for the treatment of adults with HR-positive, HER2-negative locally advanced or metastatic breast cancer without a PIK3CA mutation (PIK3CA wild-type), following progression on or after at least one line of endocrine therapy in the metastatic setting. Revtorpyk is the first FDA-approved multi-target PI3K/AKT/mTOR (PAM pathway) inhibitor, and the first targeted therapy approved for PIK3CA wild-type HR+/HER2- advanced breast cancer. What “PIK3CA wild-type” means and why it matters: approximately 40% of HR+/HER2- breast cancers carry activating PIK3CA mutations, for which alpelisib (Piqray) is approved. The remaining approximately 60% have PIK3CA wild-type disease, meaning no activating PIK3CA mutation is detected. This larger population has had no approved targeted inhibitor of the PI3K pathway because existing approved agents (alpelisib, inavolisib) require a PIK3CA mutation for indication. Gedatolisib works across both PIK3CA mutant and wild-type disease by targeting the pathway more comprehensively than PI3K-alpha-specific inhibitors. Mechanism: gedatolisib is a potent, pan-PI3K and mTORC1/2 inhibitor that blocks all four class I PI3K isoforms (alpha, beta, delta, gamma) plus both mTOR complexes simultaneously, providing comprehensive PAM pathway suppression that cannot be bypassed through isoform switching or mTOR feedback loops that limit single-target inhibitors. Administration: intravenous infusion over 30 minutes on days 1, 8, and 15 of a 28-day cycle. Lyophilized powder reconstituted before administration. The clinical basis: VIKTORIA-1 Study 1 (NCT05501886), Phase 3, open-label, randomized. PIK3CA wild-type cohort results published in JCO in March 2026. Median PFS: 9.3 months (gedatolisib plus palbociclib plus fulvestrant, triplet) versus 2.0 months (fulvestrant monotherapy); HR 0.24 (95% CI 0.17 to 0.35); p less than 0.001. 76% reduction in risk of progression or death with the triplet. Median PFS: 7.4 months (gedatolisib plus fulvestrant, doublet) versus 2.0 months; HR 0.33 (95% CI 0.24 to 0.48); p less than 0.001. 67% reduction in risk of progression or death with the doublet. ORR: approximately 32% (triplet) and 28.3% (doublet) versus approximately 1% (fulvestrant). Median DOR: 11.4 months (triplet) and 12.0 months (doublet). Regulatory pathway: NDA submitted November 2025 under the Real-Time Oncology Review (RTOR) program; Priority Review granted January 2026; Breakthrough Therapy Designation and Fast Track Designation previously granted. PIK3CA mutant indication: an sNDA for gedatolisib in PIK3CA-mutant HR+/HER2- breast cancer is planned for Q3 2026 submission, based on the PIK3CA-mutant cohort of VIKTORIA-1 (Study 2), presented at ASCO 2026.

    HR-positive, HER2-negative breast cancer is the most common subtype of metastatic breast cancer, accounting for approximately 70% of all advanced cases. The treatment landscape has been transformed over the past decade by CDK4/6 inhibitors paired with endocrine therapy, which have extended median survival to several years for many patients. But the disease almost always progresses, and what comes after CDK4/6 inhibitor-based treatment is one of the most actively contested questions in breast oncology.

    The PI3K/AKT/mTOR pathway is one of the most important drivers of endocrine resistance in HR+ breast cancer. Activating mutations in PIK3CA, the gene encoding the PI3K alpha catalytic subunit, are present in approximately 40% of HR+/HER2- tumors and lead to constitutive PI3K activation that drives cell proliferation regardless of hormone availability. For this 40%, alpelisib (Piqray) provides an approved PI3K-alpha-specific targeted option.

    But 60% of HR+/HER2- breast cancers have PIK3CA wild-type disease. No activating mutation. No approved PI3K-directed targeted therapy. Until July 14, 2026.

    Revtorpyk (gedatolisib, Celcuity Inc.) is the first drug approved for this population, and its approval rests on a biological insight that distinguishes it from every prior PI3K inhibitor: the PAM pathway drives endocrine resistance not only when PIK3CA is mutated but across the broader population, and blocking the pathway comprehensively rather than at a single node produces clinical benefit even in the absence of a defining mutation. The Phase 3 VIKTORIA-1 data in PIK3CA wild-type patients, with a 76% reduction in risk of progression with the triplet regimen versus fulvestrant monotherapy, are among the most striking efficacy numbers produced in post-CDK4/6 inhibitor breast cancer trials to date.


    The HR+/HER2- Treatment Landscape After CDK4/6 Inhibitor Progression

    HR-positive, HER2-negative breast cancer is driven primarily by estrogen receptor signaling. Endocrine therapy blocks this signaling, and the addition of CDK4/6 inhibitors (palbociclib, ribociclib, abemaciclib) to endocrine therapy has produced median progression-free survival of 25 to 30 months or more in the first-line metastatic setting, a major advance over endocrine therapy alone.

    After CDK4/6 inhibitor-based first-line therapy progresses, the standard approach depends on disease characteristics. For patients with ESR1 mutations (which develop in approximately 30 to 40% of patients on aromatase inhibitor-based therapy), elacestrant (Orserdu) or other agents targeting mutant ESR1 are options. For patients with PIK3CA mutations, alpelisib (and more recently inavolisib) provide PI3K-directed options. For patients with BRCA1/2 mutations, PARP inhibitors are relevant.

    The PIK3CA wild-type population, approximately 60% of all post-CDK4/6 inhibitor HR+/HER2- patients, has had none of these mutation-matched targeted options. The available treatments are additional endocrine therapy combinations, everolimus (mTOR inhibitor)-based regimens, and increasingly antibody-drug conjugates like sacituzumab govitecan. Everolimus specifically targets mTORC1 in isolation, and its clinical benefit in this setting has been partial, limited by the feedback reactivation of PI3K that occurs when mTORC1 alone is blocked.

    Gedatolisib’s approval provides this population’s first approved targeted inhibitor of the PAM pathway.


    The Science: Why Pan-PI3K Plus Dual mTOR Inhibition Is Mechanistically Different

    The PI3K/AKT/mTOR pathway is a master regulator of cell growth, survival, and metabolism. Its dysregulation is among the most common events in human cancer. In HR+ breast cancer, the pathway drives endocrine resistance through multiple mechanisms: it activates estrogen receptor independently of ligand, promotes cell cycle re-entry through CDK4/6 activation, and drives antiapoptotic signaling that keeps tumor cells alive despite endocrine blockade.

    The pathway architecture is a cascade: growth factor signals activate PI3K (which phosphorylates PIP2 to PIP3), which activates AKT, which activates mTORC1 and mTORC2, which drive downstream transcription and protein synthesis for proliferation and survival. The cascade also includes a critical negative feedback loop: mTORC1 inhibition (as produced by everolimus) triggers PI3K reactivation through relief of the S6K1-IRS-1 feedback, partially undercutting the intended therapeutic effect.

    Gedatolisib addresses the pathway comprehensively:

    All four class I PI3K isoforms (alpha, beta, delta, gamma): In PIK3CA wild-type disease, other PI3K isoforms (PI3K-beta particularly) can compensate when PI3K-alpha alone is blocked by an alpha-specific inhibitor. By blocking all four isoforms simultaneously, gedatolisib prevents isoform switching that would otherwise allow the pathway to remain active.

    Both mTOR complexes (mTORC1 and mTORC2): mTORC2 phosphorylates AKT at Ser473, maintaining AKT activity even when upstream PI3K is partially inhibited. By blocking mTORC2 as well as mTORC1, gedatolisib closes the reactivation loop that limits the efficacy of mTORC1-selective inhibitors like everolimus.

    The result is a mechanistic approach that suppresses the PAM pathway more completely and more durably than any single-target inhibitor, and that does so regardless of which specific mutation (or absence of mutation) is driving pathway activation. This is why gedatolisib produces clinical benefit in PIK3CA wild-type patients, where no single-node inhibitor has succeeded: the wild-type pathway remains abnormally activated through other mechanisms (receptor tyrosine kinase signaling, loss of PTEN, AKT mutations), and comprehensive blockade addresses these regardless of which upstream event is present.

    Dr. Sara Hurvitz, principal investigator for VIKTORIA-1, stated that the trial validates the PAM pathway as a molecular driver in HR+/HER2- advanced breast cancer regardless of PIK3CA mutation status, meaning the approach of comprehensive pathway blockade is supported across the full population rather than requiring a specific mutation.

    Why PIK3CA wild-type disease still has an active PAM pathway The intuition that PIK3CA wild-type disease lacks meaningful PI3K pathway activation is incorrect. Multiple mechanisms drive abnormal PAM pathway activity without a PIK3CA mutation: overactivation of receptor tyrosine kinases (HER3, IGF-1R, FGFR) that signal through PI3K; loss of PTEN (the phosphatase that opposes PI3K activity), present in 15 to 30% of HR+ breast cancers regardless of PIK3CA status; activating mutations in AKT1 or other pathway components; and post-CDK4/6 inhibitor adaptive changes that upregulate pathway activity as a resistance mechanism. Gedatolisib’s clinical activity in PIK3CA wild-type disease confirms that the pathway is biologically active and targetable in this population even without a defining PIK3CA mutation.

    The VIKTORIA-1 Study 1 Trial: Full Data for the Wild-Type Cohort

    Design

    VIKTORIA-1 (NCT05501886) is a Phase 3, multicenter, open-label, randomized trial with two independently powered cohorts: Study 1 (PIK3CA wild-type) and Study 2 (PIK3CA-mutant). The two cohorts were analyzed separately. The approval and this post cover Study 1.

    Study 1 enrolled adults with HR-positive, HER2-negative locally advanced or metastatic breast cancer with PIK3CA wild-type disease (no activating PIK3CA mutation detected by an FDA-authorized companion diagnostic assay) who had progressed on or after at least one line of endocrine therapy in the metastatic setting. The vast majority of enrolled patients had received prior CDK4/6 inhibitor-based therapy.

    Patients were randomized 1:1:1 to three arms:

    • Gedatolisib plus palbociclib plus fulvestrant (triplet arm)
    • Gedatolisib plus fulvestrant (doublet arm)
    • Fulvestrant monotherapy (control arm)

    Gedatolisib was administered as a 30-minute IV infusion on days 1, 8, and 15 of each 28-day cycle. Palbociclib was given at 125 mg orally on days 1 to 21 of each cycle. Fulvestrant was given at standard dosing (500 mg IM on days 1 and 15 of cycle 1, then day 1 of each subsequent cycle). The primary endpoint was progression-free survival (PFS) by blinded independent central review (BICR) in each gedatolisib-containing arm versus fulvestrant. Results were published in the Journal of Clinical Oncology in March 2026.

    Primary efficacy results at median follow-up 12.8 months

    EndpointGedatolisib tripletGedatolisib doubletFulvestrant
    Median PFS (BICR)9.3 months7.4 months2.0 months
    Hazard ratio versus fulvestrant0.24 (95% CI 0.17 to 0.35)0.33 (95% CI 0.24 to 0.48)Reference
    p-value versus fulvestrantp less than 0.001p less than 0.001—
    Risk reduction in progression or death76% (triplet)67% (doublet)—
    PFS incremental improvement7.3 months5.4 months—

    Source: Hurvitz SA et al. VIKTORIA-1 trial of gedatolisib plus fulvestrant with or without palbociclib in HR+/HER2-/PIK3CA wild-type advanced breast cancer. JCO. 2026. doi:10.1200/JCO-25-02643. NCT05501886.

    The magnitude of these PFS improvements is exceptional for the post-CDK4/6 inhibitor setting, where standard second-line endocrine combinations typically produce median PFS of 4 to 6 months. A median PFS of 9.3 months for the triplet and 7.4 months for the doublet, compared to 2.0 months for fulvestrant alone, represents a clinically dramatic separation of the curves. The control arm median PFS of 2.0 months reflects the biological reality of post-CDK4/6 inhibitor PIK3CA wild-type disease: fulvestrant monotherapy provides very limited benefit in this setting, confirming the extent of endocrine resistance and the unmet need.

    Response and durability

    EndpointGedatolisib tripletGedatolisib doubletFulvestrant
    Objective response rate (ORR)Approximately 32%28.3%Approximately 1%
    Median duration of response (DOR)11.4 months12.0 monthsNot determinable (only 1 response)

    The ORR of approximately 32% for the triplet and 28% for the doublet versus approximately 1% for fulvestrant reflects a real tumor-shrinking activity in a population where endocrine monotherapy produces almost no responses. The durability of approximately 11 to 12 months in responders is consistent with meaningful clinical benefit.

    VIKTORIA-1 Study 2: The PIK3CA-Mutant Data at ASCO 2026

    Though the July 14, 2026 approval covers only the PIK3CA wild-type population based on Study 1, Celcuity presented the PIK3CA-mutant cohort (Study 2) results at the 2026 ASCO Annual Meeting as a late-breaking abstract (LBA1008). The data showed statistically significant and clinically meaningful PFS improvements with both gedatolisib combinations versus standard of care in PIK3CA-mutant patients as well, with hazard ratios in the same directionally strong range as the wild-type cohort. An sNDA for the mutant indication is planned for Q3 2026 submission. This means gedatolisib, if that sNDA is approved, will ultimately cover the full HR+/HER2- post-endocrine therapy population regardless of PIK3CA mutation status, making mutation testing a guide to which comparator benchmark to use rather than a gating criterion for eligibility.


    The VIKTORIA-1 Study 1 Design: What Makes the Control Arm Comparison Meaningful

    One important interpretive context for the VIKTORIA-1 data: the control arm is fulvestrant monotherapy, not an active CDK4/6 inhibitor combination or another targeted agent. This is an appropriate and clinically grounded comparator for the post-CDK4/6 inhibitor PIK3CA wild-type setting, where physicians currently have no approved targeted option beyond fulvestrant. But it means the absolute PFS numbers should be interpreted as comparison to the current clinical standard (fulvestrant) rather than to other active agents that are also used in this setting.

    No head-to-head trial has compared gedatolisib directly to other agents used in this line (such as sacituzumab govitecan or everolimus/exemestane). Those comparisons will emerge from clinical experience and real-world data over time.


    Dosing and Administration

    Revtorpyk is supplied as a lyophilized powder that requires reconstitution before administration. This manufacturing form reflects the formulation chemistry needed to maintain stability of the compound; it is reconstituted by pharmacy personnel and administered to the patient as a ready-to-use infusion.

    Dosing schedule:

    • Gedatolisib: reconstituted and administered as a 30-minute IV infusion on days 1, 8, and 15 of each 28-day cycle
    • Palbociclib (in the triplet): 125 mg orally once daily on days 1 to 21 of each 28-day cycle, with 7 days off
    • Fulvestrant (in both regimens): 500 mg IM on days 1 and 15 of cycle 1, then day 1 of each subsequent cycle

    The weekly infusion schedule (3 infusions per 4-week cycle) is the most notable practical consideration for patients. This is more frequent clinical contact than the every-2-to-3-week infusion schedules of some other IV-administered oncology drugs, and it represents a meaningful time commitment for patients managing advanced breast cancer. The 30-minute infusion duration is relatively short compared to some IV biologics, but the weekly schedule means patients visit an infusion center three times every four weeks indefinitely.

    PIK3CA testing requirement:

    The approved indication specifies PIK3CA wild-type disease, meaning testing to confirm the absence of an activating PIK3CA mutation is required before initiating treatment. An FDA-authorized companion diagnostic assay must be used. This is a companion diagnostic requirement that should be incorporated into the workup for all patients with HR+/HER2- advanced breast cancer progressing on CDK4/6 inhibitor therapy, both to confirm gedatolisib eligibility and to identify the approximately 40% of patients who may instead be eligible for alpelisib, inavolisib, or the future PIK3CA-mutant gedatolisib indication.


    Safety: The VIKTORIA-1 Profile

    The safety profile of gedatolisib in VIKTORIA-1 is consistent with the known class effects of PAM pathway inhibition, with stomatitis and hyperglycemia as the most pharmacologically characteristic adverse events, and neutropenia as the dominant toxicity in the triplet arm due to the addition of palbociclib.

    Grade 3 or higher treatment-related adverse events in Study 1

    Adverse eventGedatolisib tripletGedatolisib doubletFulvestrant
    Neutropenia62.3%0.8%0.8%
    Stomatitis19.2%12.3%0%
    Rash4.6%5.4%0%
    Hyperglycemia2.3%2.3%0%
    Diarrhea1.5%0.8%0%
    Nausea3.8%0.8%0%
    Leukopenia (grade 4)0.8%0%0%
    Pneumonitis (grade 4)0%0.8%0%
    Treatment discontinuation due to TRAEs2.3%3.1%—

    Source: Hurvitz SA et al. JCO. 2026. PMC13075786.

    Stomatitis: The most characteristic and commonly discussed gedatolisib-specific toxicity. Grade 3 stomatitis occurred in 19.2% (triplet) and 12.3% (doublet) of patients. Importantly, among patients who did develop stomatitis, the majority experienced grade 1 as their first event (57 of 90 in the triplet arm; 48 of 74 in the doublet arm), with fewer progressing to grade 2 or 3 as their initial presentation. Stomatitis is a class effect of PI3K and mTOR inhibitors and is managed with prophylactic mouthwash protocols, dose modifications, and patient education on early symptom reporting. The treatment discontinuation rate due to stomatitis alone was low (overall discontinuation for any TRAE was 2.3% in the triplet and 3.1% in the doublet).

    Neutropenia in the triplet: The high grade 3 or higher neutropenia rate of 62.3% in the triplet arm is driven primarily by the palbociclib component, consistent with palbociclib’s established neutropenia profile in all of its approved regimens. CBC monitoring before each cycle and dose modification per the Revtorpyk and palbociclib prescribing information apply. The neutropenia rate in the doublet (0.8%) confirms that gedatolisib itself does not substantially contribute to bone marrow suppression; this is a palbociclib effect in the triplet.

    Hyperglycemia: PI3K inhibition affects insulin signaling, and hyperglycemia is a known class effect. Grade 3 hyperglycemia occurred in 2.3% of patients in both gedatolisib arms. Blood glucose monitoring before treatment initiation and periodically during treatment, with dose modification and antidiabetic medication management as appropriate, follows the established management framework for PAM pathway inhibitors. Patients with pre-existing diabetes should be closely monitored.

    Pneumonitis: Grade 4 pneumonitis occurred in 0.8% of doublet-treated patients. Pneumonitis is a known and serious risk associated with PI3K and mTOR inhibitors as a class. Patients should be monitored for new or worsening pulmonary symptoms; grade 2 or higher pneumonitis typically requires treatment interruption and corticosteroid management, with permanent discontinuation for grade 3 or higher.

    Key warnings and precautions (from Revtorpyk prescribing information):

    WarningClinical guidance
    HyperglycemiaFasting glucose before initiating and periodically during treatment; dose modification for grade 3 or higher; may require antidiabetic medication initiation or dose adjustment
    StomatitisOral hygiene and prophylactic mouthwash regimens recommended before initiating; dose modification for grade 2 or higher; patient education on early reporting
    PneumonitisMonitor for pulmonary symptoms; hold for grade 2 pneumonitis; permanently discontinue for grade 3 or higher
    Embryo-fetal toxicityGedatolisib can cause fetal harm; effective contraception during treatment and for at least the period specified in prescribing information after last dose
    Neutropenia (triplet)CBC at baseline and before each cycle; dose modifications per palbociclib and Revtorpyk prescribing information for grade 3 or higher neutropenia

    What This Means in Clinical Practice

    For patients with HR+/HER2- PIK3CA wild-type advanced breast cancer

    If you have HR-positive, HER2-negative metastatic breast cancer, your tumor has been tested and does not have a PIK3CA mutation, and your disease has progressed on or after prior endocrine therapy (including CDK4/6 inhibitor-based regimens), you are now in the patient population for which Revtorpyk is approved. This is the first targeted agent specifically approved for your PIK3CA status in this disease.

    The treatment involves weekly IV infusions (three per four-week cycle) plus fulvestrant injections and, in the triplet, oral palbociclib. The clinical decision between the triplet and doublet depends on your prior therapy, current blood counts, and your oncologist’s assessment of the most appropriate regimen for your situation. Patients who have previously received a CDK4/6 inhibitor may or may not be candidates for the triplet re-challenge with palbociclib depending on the reasons for prior CDK4/6 inhibitor discontinuation.

    For oncologists

    VIKTORIA-1 Study 1 establishes gedatolisib plus fulvestrant, with or without palbociclib, as a new evidenced-based option for post-CDK4/6 inhibitor PIK3CA wild-type HR+/HER2- advanced breast cancer. The hazard ratios of 0.24 (triplet) and 0.33 (doublet) represent strong clinical benefit signals in a population with historically limited targeted options.

    The companion diagnostic testing requirement adds a testing step to the treatment planning workflow that should now be standardized for all HR+/HER2- advanced breast cancer patients progressing on CDK4/6 inhibitor therapy, covering both PIK3CA mutation testing (to identify alpelisib/inavolisib-eligible patients) and confirming wild-type status for gedatolisib eligibility. ESR1 mutation testing for elacestrant eligibility remains a parallel testing requirement that the same blood sample or tissue can typically address.

    The weekly infusion schedule is a meaningful practical factor in patient selection and treatment planning. Patients whose performance status, transportation access, and support systems make weekly clinic visits feasible are appropriate candidates; for patients where this frequency is a significant barrier, the clinical conversation should include the doublet, which has the same visit schedule but without the oral palbociclib complexity.

    Dr. Joyce O’Shaughnessy of Baylor University Medical Center noted that in her opinion, this could be immediately practice changing, given the PFS data in both the PIK3CA wild-type and PIK3CA-mutant populations being consistently better than the control arm.

    The upcoming sNDA for the PIK3CA-mutant indication (planned Q3 2026 submission) is the next major regulatory event to watch. If approved, gedatolisib will cover the full HR+/HER2- post-endocrine therapy population and PIK3CA testing will guide regimen selection and comparator benchmarking rather than drug eligibility.

    For related HED coverage on HR+/HER2- breast cancer approvals, see our post on palbociclib (Ibrance) receiving its first HER2-positive breast cancer approval for HR+/HER2+ maintenance and our post on Trodelvy (sacituzumab govitecan) receiving two new first-line approvals for metastatic TNBC.

    For patients and families navigating an HR-positive metastatic breast cancer diagnosis, the National Breast Cancer Foundation (nationalbreastcancer.org), the Susan G. Komen Foundation (komen.org; 1-877-GO-KOMEN), and the LBBC (Living Beyond Breast Cancer) maintain current resources on treatment options, clinical trials, and financial assistance.


    Sources

    FDA approval announcement: FDA approves gedatolisib with fulvestrant, with or without palbociclib, for HR-positive, HER2-negative locally advanced or metastatic breast cancer. FDA.gov. July 14, 2026.

    Celcuity FDA approval press release: Celcuity Announces FDA Approval of REVTORPYK (gedatolisib) for the Treatment of HR+/HER2-, PIK3CA Wild-Type Locally Advanced or Metastatic Breast Cancer. GlobeNewswire. July 14, 2026.

    Drugs.com approval news: FDA Approves Revtorpyk (gedatolisib) for the Treatment of HR+/HER2-, PIK3CA Wild-Type Locally Advanced or Metastatic Breast Cancer. drugs.com. July 14, 2026.

    VIKTORIA-1 Study 1 JCO primary publication (March 2026): Hurvitz SA et al. VIKTORIA-1 trial of gedatolisib plus fulvestrant with or without palbociclib in hormone receptor-positive/HER2-/PIK3CA wild-type advanced breast cancer. Journal of Clinical Oncology. 2026. doi:10.1200/JCO-25-02643.

    VIKTORIA-1 trial registration: NCT05501886. ClinicalTrials.gov.

    Celcuity JCO publication press release (March 9, 2026): Celcuity Announces Publication of Results from PIK3CA Wild-Type Cohort of Phase 3 VIKTORIA-1 Study. GlobeNewswire. March 9, 2026.

    CancerNetwork full efficacy and clinical context (with Dr. O’Shaughnessy quote): FDA Approves Gedatolisib for HR+, HER2- PIK3CA Wild-Type Advanced Breast Cancer. cancernetwork.com. July 2026.

    Targeted Oncology (RTOR, Breakthrough Therapy designation, ASCO context): FDA Approves Gedatolisib for HR+/HER2-, PIK3CA Wild-Type Advanced Breast Cancer. targetedonc.com. July 2026.

    Pharmacy Times (full safety table, mechanism detail): Gedatolisib Combination Approved for PIK3CA Wild-Type HR+, HER2- Breast Cancer. pharmacytimes.com. July 2026.

    CURE (patient-facing dosing and administration detail): FDA Approves Revtorpyk for Advanced HR-Positive, HER2-Negative Breast Cancer. curetoday.com. July 2026.

    VIKTORIA-1 ESMO 2025 presentation (Celcuity PDF): VIKTORIA-1 PIK3CA WT ESMO Presentation. celcuity.com. October 2025.

    CancerNetwork VIKTORIA-1 Study 2 ASCO 2026 data (mutant cohort): VIKTORIA-1 Regimen Shows Efficacy in PIK3CA+ Breast Cancer. cancernetwork.com. June 2026.

    VIKTORIA-1 Study 2 ASCO 2026 abstract: Hurvitz SA et al. VIKTORIA-1 Study 2. J Clin Oncol. 44, 2026 (suppl 17; abstr LBA1008). doi:10.1200/JCO.2026.44.17_suppl.LBA1008.

    FCS Hematology Oncology Review (complete grade 3/4 safety table): VIKTORIA-1 Trial of Gedatolisib Plus Fulvestrant With or Without Palbociclib. fcshemoncreview.com.

    PI3K/AKT/mTOR pathway biology: PI3K/AKT/mTOR Signaling in Cancer. PMC7734386.

    Breast cancer overview: Breast Cancer. StatPearls. NCBI.

    Alpelisib FDA approval (PIK3CA-mutant reference): FDA approves alpelisib for breast cancer. FDA.gov.

    Revtorpyk prescribing information: REVTORPYK (gedatolisib) Prescribing Information. Celcuity Inc. 2026.

    Revtorpyk approval history: Revtorpyk FDA Approval History. drugs.com.

    Patient resources: National Breast Cancer Foundation | Susan G. Komen Foundation: 1-877-GO-KOMEN | Living Beyond Breast Cancer | Celcuity Revtorpyk patient support

    Disclaimer: Health Evidence Digest provides general information about FDA approvals and health research for educational purposes. This content is not a substitute for professional medical advice. Revtorpyk (gedatolisib) requires PIK3CA wild-type confirmation by an FDA-authorized companion diagnostic assay before initiating treatment. Treatment decisions for HR-positive, HER2-negative advanced breast cancer, including regimen selection following CDK4/6 inhibitor-based therapy, should be made in close collaboration with a board-certified medical oncologist experienced in breast cancer management and familiar with the full clinical context including prior therapy, mutation status, and performance status.
  • Topical Steroids Cannot Be Used Long-Term on a Two-Year-Old’s Face or Skin Folds. For Children That Young With Plaque Psoriasis, There Has Been Almost Nothing Else. Zoryve Cream Just Changed That.

    Topical Steroids Cannot Be Used Long-Term on a Two-Year-Old’s Face or Skin Folds. For Children That Young With Plaque Psoriasis, There Has Been Almost Nothing Else. Zoryve Cream Just Changed That.

    The essentials: On June 29, 2026, the FDA expanded the approval of Zoryve (roflumilast) cream 0.3% (Arcutis Biotherapeutics) to include children aged 2 years and older with plaque psoriasis, including intertriginous areas. The prior lower age limit was 6 years. The new approval makes Zoryve cream 0.3% the first once-daily, steroid-free topical treatment for plaque psoriasis approved down to age 2, and the only topical PDE4 inhibitor approved for plaque psoriasis in children under 6. This is not a new drug. Roflumilast is the active molecule in Zoryve cream 0.3%, a topical phosphodiesterase 4 (PDE4) inhibitor that has been approved for plaque psoriasis in patients 12 and older since July 2022, extended to ages 6 to 11 in October 2023, and now extended to ages 2 to 5. The indication, including application to intertriginous (skin fold) areas, is now continuous from age 2 through adulthood with no restrictions on duration of use. Formulation: Zoryve cream 0.3% is steroid-free, does not contain PEG, propylene glycol, ethanol, or fragrances, and is applied once daily to affected areas. Supplied in a 60 g tube. The clinical basis for the ages 2 to 5 expansion: Phase 2 open-label MUSE study (ARQ-151-216; NCT04746911), 4 weeks, evaluating pharmacokinetics, safety, tolerability, and exploratory efficacy in children aged 2 to 5 years with plaque psoriasis involving at least 2% BSA; and long-term open-label trial (ARQ-151-306; NCT04286607) providing supportive safety, tolerability, and efficacy data through 24 weeks. At week 4 in the MUSE 2-to-5 cohort (n=10): IGA success 90%; PASI-75 90%; Worst Itch NRS success 90% (caregiver-reported). Safety consistent with the established profile in older patients. Systemic absorption detected but within acceptable bounds under maximal-use conditions, consistent with prior adult and adolescent pharmacokinetic observations. AAD designation: strong recommendation for Zoryve cream 0.3% in pediatric atopic dermatitis ages 6 and older in the AAD’s first-ever pediatric atopic dermatitis guidelines (April 2026). National Psoriasis Foundation Seal of Recognition awarded to Zoryve cream 0.3% and Zoryve foam 0.3%, the first FDA-approved prescription brand to receive this honor.

    The first thing most people need to understand about psoriasis in very young children is that it looks and behaves differently from psoriasis in adults, and the places it appears most commonly are precisely the places where standard treatment is most constrained. A two-year-old with plaque psoriasis is not just a smaller version of a forty-year-old with plaque psoriasis. The disease in toddlers and preschool-age children frequently involves the face, including the hairline and ears, and the skin folds: the diaper area, groin, axillae, and neck creases. These are all areas where topical corticosteroids, the standard of care for decades, carry the highest risk of local adverse effects with extended use.

    Topical corticosteroids applied to the face and intertriginous areas of young children can cause skin atrophy, striae, telangiectasia, and with potent or prolonged application, suppression of the hypothalamic-pituitary-adrenal axis. Guidelines do not support their long-term use in these locations. But pediatric plaque psoriasis is a chronic disease. It does not resolve after a four-week course of cream. Families managing it need a treatment that can be applied consistently, anywhere on the body, for as long as the disease requires. For children under six, there has been essentially nothing that meets that description.

    Zoryve cream 0.3% (roflumilast, Arcutis Biotherapeutics) received FDA approval on June 29, 2026, for the treatment of plaque psoriasis in children as young as age 2, making it the first once-daily steroid-free treatment for plaque psoriasis approved in this age group. The approval closes a real prescribing gap rather than an incremental one: the drug is now labeled for use anywhere on the body including intertriginous areas, with no restrictions on duration, from age 2 through adulthood.


    The Pediatric Psoriasis Treatment Gap: Why This Age Range Matters

    Pediatric psoriasis affects approximately 1% of children and accounts for roughly 30% of all psoriasis cases when considered across lifetime onset. Onset in the first five years of life is not uncommon, and early-onset disease is often associated with a chronic relapsing course that extends into adulthood.

    For children under six, the practical treatment options before this approval were:

    Emollients and moisturizers: Appropriate for all pediatric psoriasis as supportive care but not therapeutic in moderate disease.

    Mild topical corticosteroids: Acceptable for short-term use on the body in young children, but guidance against extended use on the face, skin folds, and genital area is consistent across dermatology guidelines. The very areas most commonly affected by psoriasis in toddlers are the areas most restricted for steroid use.

    Topical calcineurin inhibitors (tacrolimus, pimecrolimus): Approved for atopic dermatitis but carry an FDA boxed warning about a theoretical cancer risk that has made many families and clinicians reluctant to use them long-term, despite the fact that current evidence does not substantiate the concern. Not approved for psoriasis.

    Coal tar preparations: Older, generally well-tolerated, but cosmetically challenging and with limited acceptability in daily use on young children.

    Systemic therapy: Not appropriate for most toddlers with mild-to-moderate plaque psoriasis, and options for systemic therapy in children under 6 are even more constrained than for older children.

    The result: families of young children with chronic plaque psoriasis have often cycled through short courses of topical steroids, periods without effective treatment, and repeated conversations with pediatric dermatologists about what to do next. This is the clinical reality that the Zoryve cream 0.3% approval for ages 2 to 5 addresses.

    As Dr. Lisa Swanson, a board-certified pediatric dermatologist at Ada West Dermatology and a clinical trial investigator, noted: “Young children with plaque psoriasis face unique challenges, including disease involvement on sensitive skin, such as the face and skin folds. In clinical studies, Zoryve cream 0.3% demonstrated consistent safety and efficacy in improving the signs and symptoms of plaque psoriasis as seen in adults and adolescents, and was safe and well tolerated in children as young as age 2.”

    For context on the pediatric inflammatory skin disease approval landscape in 2026, see our post on Ryaltris receiving its first approval for children aged 6 to 11 with seasonal allergic rhinitis.


    What Roflumilast Is: The PDE4 Inhibitor Mechanism in Skin Disease

    Roflumilast is a selective inhibitor of phosphodiesterase type 4 (PDE4), a family of intracellular enzymes responsible for degrading cyclic AMP (cAMP). PDE4 is the dominant phosphodiesterase in immune and inflammatory cells, including T cells, neutrophils, eosinophils, macrophages, and keratinocytes.

    Under normal signaling conditions, cAMP acts as an intracellular second messenger that inhibits pro-inflammatory activity in immune cells. When PDE4 degrades cAMP, this anti-inflammatory brake is released and inflammatory mediators are produced. By inhibiting PDE4, roflumilast prevents cAMP degradation, allowing cAMP to accumulate intracellularly, which suppresses the production of pro-inflammatory cytokines including TNF-alpha, IL-2, IL-4, IL-5, IL-12, IL-13, IL-17, and IL-23. These are precisely the cytokines that drive psoriatic skin inflammation.

    The clinical consequence of this mechanism in psoriasis is anti-inflammatory activity that reduces plaque thickness, erythema, and scaling without the structural effects of corticosteroids on the skin. Roflumilast does not thin the skin, does not cause striae, and does not suppress adrenal function. These properties are what enable its use without restrictions on body site or treatment duration.

    Roflumilast in oral form (Daliresp) has been approved since 2011 for COPD, where it reduces systemic inflammation. The topical formulations used in dermatology are chemically the same molecule but delivered in cream and foam vehicles designed to maximize skin penetration while minimizing systemic absorption.

    The Zoryve cream formulation is notable for what it does not contain alongside the active ingredient: no PEG, no propylene glycol, no ethanol, and no fragrances. These are common irritants and sensitizers that make many topical preparations inappropriate for inflamed or sensitive skin in young children. The absence of these excipients is a meaningful formulation attribute for the ages 2 to 5 population, where skin barrier function may already be compromised by psoriatic inflammation.


    How Zoryve Cream 0.3%’s Approval History Has Expanded: Age by Age

    Understanding this approval requires understanding where Zoryve cream 0.3% stands in the broader Zoryve portfolio and how its age indication has been systematically extended.

    ApprovalDateIndicationAge range
    Original Zoryve cream 0.3%July 29, 2022Plaque psoriasis including intertriginous areasAges 12 and older
    Age expansionOctober 9, 2023Plaque psoriasis including intertriginous areasAges 6 and older (added 6 to 11)
    Zoryve cream 0.15%July 9, 2024Mild-to-moderate atopic dermatitisAges 6 and older
    Zoryve cream 0.05%October 2025Mild-to-moderate atopic dermatitisAges 2 to 5
    This approvalJune 29, 2026Plaque psoriasis including intertriginous areasAges 2 and older (added 2 to 5)

    For the Skyrizi pediatric expansion approved the same week, covering IL-23 inhibition for plaque psoriasis in children aged 6 and older, see our post on Skyrizi becoming the first IL-23 inhibitor approved down to age 6.

    The Zoryve portfolio now covers plaque psoriasis and atopic dermatitis across overlapping pediatric age ranges with different concentrations tailored to the inflammation depth and pharmacokinetic considerations relevant to each age group. For plaque psoriasis specifically, Zoryve cream 0.3% now covers from age 2 through adulthood in a continuous, unrestricted indication.

    Zoryve foam 0.3%, approved separately for scalp and body plaque psoriasis, is indicated for adults and patients aged 12 and older and has not been extended to younger children in this action.


    The MUSE Study and Supporting Data: What the Evidence Shows

    The FDA approval for ages 2 to 5 is based on two clinical studies specifically conducted in this age group, supported by the larger efficacy database in older patients.

    MUSE study (ARQ-151-216; NCT04746911)

    The MUSE study was a Phase 2, open-label trial evaluating roflumilast cream 0.3% in children aged 2 to 5 years (n=10) with plaque psoriasis involving at least 2% body surface area. This was a maximal usage systemic exposure study, meaning the drug was applied to the maximum amount of affected skin to evaluate pharmacokinetics and confirm that systemic absorption under worst-case conditions remained within acceptable safety limits.

    At 4 weeks:

    EndpointResult (ages 2 to 5, n=10)
    IGA success (clear or almost clear, plus at least 2-grade improvement)90%
    PASI-75 (at least 75% improvement in PASI)90%
    WI-NRS success (at least 4-point reduction in worst itch, caregiver-reported for children under 8)90%

    Source: HCPLive MUSE data summary. June 2026. NCT04746911.

    Evidence of systemic absorption of roflumilast and its active N-oxide metabolite was detected in most participants, consistent with prior Phase 3 pharmacokinetic data in adults and adolescents. The pharmacokinetic profiles were within the acceptable range established by the broader adult and adolescent safety database.

    Long-term open-label study (ARQ-151-306; NCT04286607)

    The long-term study provided supportive safety and efficacy data through up to 24 weeks of treatment in children aged 2 to 5 years. Results showed the safety and efficacy of roflumilast cream 0.3% in patients 2 years and older were generally consistent with those observed in clinical trials involving pediatric patients aged 6 to 11 years, adolescents, and adults.

    Interpreting the small-n MUSE data honestly

    The MUSE cohort for ages 2 to 5 enrolled 10 patients. This is a small sample, and the 90% response rates at 4 weeks should be interpreted in that context: with n=10, each patient accounts for 10 percentage points of any rate. The open-label, single-arm design without a placebo comparator also means the observed rates include the natural course of psoriasis during the observation period alongside the drug effect.

    The FDA’s decision to approve based on this data rests on several established principles for pediatric drug development. The efficacy of roflumilast cream 0.3% has been established in large, well-controlled Phase 3 trials in adults and adolescents (DERMIS-1 and DERMIS-2). The mechanism of action and pharmacokinetics are well-characterized across multiple age groups. The MUSE study’s role was primarily to confirm that systemic exposure in the youngest children does not differ meaningfully from the established safety-relevant exposure range in older patients, and that the clinical response is directionally consistent with what has been observed in the rest of the population. Both were confirmed.

    The single most important limitation to acknowledge: long-term pharmacokinetic surveillance in children aged 2 to 5 with real-world application patterns is not available from the clinical trial program. The MUSE design was built for maximal use conditions over 4 weeks. Whether extended real-world use in this age group produces different systemic exposure patterns will be learned over time in clinical practice.


    The Established Phase 3 Efficacy Base: DERMIS-1 and DERMIS-2

    Because the ages 2 to 5 approval relies on consistency with the broader efficacy database, understanding that broader database is essential context for clinicians and families.

    DERMIS-1 (NCT04211363) and DERMIS-2 (NCT04211389) were the pivotal Phase 3 trials supporting the original roflumilast cream 0.3% approvals. Both were 8-week, randomized, double-blind, vehicle-controlled trials in patients aged 2 years and older (the trials were designed with the full age range in mind, though the youngest age group’s formal approval has come in stages).

    At week 8, significantly more roflumilast-treated than vehicle-treated patients achieved PASI-75 (40.3% versus 6.5%; p less than 0.0001). Using the more sensitive PASI-HD endpoint, which captures finer changes in plaque thickness, erythema, and scaling, 59.9% versus 17.9% achieved the threshold at week 8 (p less than 0.0001).

    Among patients with intertriginous psoriasis, IGA success in the affected intertriginous area was achieved in 73% of roflumilast 0.3%-treated patients versus 29% of vehicle-treated patients. This intertriginous-specific response rate is clinically significant given how commonly this body site is affected in young children with psoriasis.

    These are the efficacy data that anchor the confidence in the younger age group approval: a drug with well-demonstrated efficacy in adults and older children, consistent pharmacokinetic behavior across age groups in the MUSE studies, and directionally consistent response rates in the 2-to-5 cohort.

    For a detailed look at how the psoriatic disease treatment landscape has expanded for pediatric patients with systemic biologics, see our post on Skyrizi (risankizumab) receiving its pediatric plaque psoriasis and PsA approvals.


    Zoryve’s Full Current Indication Coverage After June 2026

    ProductIndicationAge range
    Zoryve cream 0.3%Plaque psoriasis, including intertriginous areasAges 2 and older
    Zoryve foam 0.3%Plaque psoriasis, scalp and bodyAges 12 and older
    Zoryve cream 0.15%Mild-to-moderate atopic dermatitisAges 6 and older
    Zoryve cream 0.05%Mild-to-moderate atopic dermatitisAges 2 to 5

    Zoryve is also approved for seborrheic dermatitis in foam formulation in adults. The portfolio now represents the broadest age coverage of any topical PDE4 inhibitor franchise in the United States.


    Safety: What Prescribers and Caregivers Need to Know

    The safety profile of Zoryve cream 0.3% in the ages 2 to 5 population was consistent with the established profile in older patients and adults. No new safety signals emerged in the MUSE study or the long-term extension study.

    Contraindication: Zoryve cream 0.3% is contraindicated in patients with moderate-to-severe liver impairment (Child-Pugh B or C). This reflects the hepatic metabolism of roflumilast and is standard across all roflumilast formulations.

    Common adverse reactions (occurring in at least 1% of patients in clinical trials of Zoryve cream 0.3% for plaque psoriasis): diarrhea, headache, insomnia, nausea, application site pain, upper respiratory tract infection, and urinary tract infection. These reflect low-level systemic exposure to roflumilast even from a topical formulation, consistent with the known pharmacology of PDE4 inhibition.

    Systemic absorption in young children: Roflumilast is absorbed to a small degree through the skin. In the MUSE study, systemic exposure was detected in most participants aged 2 to 5 under maximal-use conditions. The FDA considered this acceptable based on consistency with adult and adolescent exposure levels. For clinical practice, applying the drug to the minimum area necessary to control disease, rather than liberally to all skin regardless of activity, is appropriate practice in any age group.

    No boxed warning, no restriction on duration, no restriction on body site including face, skin folds, and genitalia. These are the specific label attributes that make roflumilast cream 0.3% suitable as a long-term topical option in young children with psoriasis in locations where corticosteroids cannot be used indefinitely.

    Driving and machinery: Not relevant for the ages 2 to 5 population. The adverse event of headache, nausea, and insomnia noted in clinical trials are worth monitoring; caregivers should report persistent systemic symptoms to the treating dermatologist.


    What This Means for Pediatric Dermatologists and Families

    For pediatric dermatologists

    This approval fills a specific prescribing gap that has been documented in the literature for years: children aged 2 to 5 with moderate plaque psoriasis involving the face and intertriginous areas, where corticosteroids are inappropriate for long-term use, now have an FDA-approved once-daily steroid-free option. The label explicitly covers these body sites, which removes any ambiguity about whether the approval supports use in the locations most relevant to this age group.

    The MUSE data should be interpreted in the context of the broader Phase 3 efficacy database and the established pharmacokinetic consistency across age groups, rather than as a standalone primary efficacy study. The response signals in the 2-to-5 cohort were directionally strong (90% IGA success at 4 weeks), but the n=10 sample size means these numbers carry wide uncertainty bounds.

    The AAD’s strong recommendation for various Zoryve formulations in pediatric atopic dermatitis, combined with this psoriasis indication expansion, makes roflumilast a versatile topical option for pediatric inflammatory skin disease broadly, with age-appropriate concentrations and indications mapped across the full pediatric range.

    For families

    If your child is aged 2 to 5 and has been diagnosed with plaque psoriasis, and particularly if their disease involves the face, diaper area, groin, or other skin folds where you have been told steroid creams cannot be used long-term, Zoryve cream 0.3% is now an FDA-approved option that your child’s pediatric dermatologist can prescribe.

    The cream is applied once daily to affected areas. It does not need to be washed off before bedtime. It can be applied to skin folds. There is no defined treatment duration limit. It is steroid-free and does not contain common skin irritants.

    Because Zoryve cream 0.3% is a specialty prescription product, insurance prior authorization is typically required. Arcutis operates a patient support program, Arc+, that provides insurance and access support for patients prescribed Zoryve. A specialty pharmacy familiar with Arcutis products can help navigate the prior authorization process.

    For related HED coverage on pediatric dermatology and biologic approvals for psoriatic disease in children, see our post on Skyrizi (risankizumab-rzaa) becoming the first IL-23 inhibitor approved for children aged 6 and older with plaque psoriasis and psoriatic arthritis, approved four days before this Zoryve action on June 26, 2026.


    Sources

    Arcutis FDA approval press release: FDA Approves Arcutis’ ZORYVE (roflumilast) Cream 0.3% for the Treatment of Plaque Psoriasis in Children as Young as Age 2. Arcutis Biotherapeutics. June 29, 2026.

    BusinessWire press release: FDA Approves Arcutis’ ZORYVE (roflumilast) Cream 0.3% for the Treatment of Plaque Psoriasis in Children as Young as Age 2. BioSpace. June 29, 2026.

    Drugs.com approval news: FDA Approves Arcutis’ Zoryve (roflumilast) Cream 0.3% for the Treatment of Plaque Psoriasis in Children as Young as Age 2. drugs.com. June 29, 2026.

    HCPLive (MUSE data with exact response rates, age-by-age context): FDA Approves Roflumilast 0.3% Cream for PsO in Children 2-5 Years. hcplive.com. June 2026.

    Dermatology Advisor (clinical summary and Dr. Swanson quote): FDA Expands Zoryve Cream 0.3% Approval for Plaque Psoriasis Down to Age 2. dermatologyadvisor.com. June 2026.

    Dermatology Times (ARQ-151-306 long-term study reference): FDA Approves Roflumilast Cream 0.3% for Plaque Psoriasis Down to Age 2. dermatologytimes.com. June 2026.

    Patient Care Online (adverse reaction list, contraindication): FDA Expands Roflumilast Cream 0.3% Approval for Plaque Psoriasis in Children Aged 2 Years and Older. patientcareonline.com. June 2026.

    Medscape (approval timeline context): Topical Roflumilast Approval Expanded to Include Children Ages 2-5 With Psoriasis. medscape.com. June 2026.

    Healio (prescribing gap narrative and Dr. Swanson commentary): FDA expands approval for Zoryve cream 0.3% to children with psoriasis as young as 2 years. healio.com. June 2026.

    Clinical Trial Vanguard (PK limitation analysis, competitive context): FDA Approves Roflumilast Cream for Plaque Psoriasis in Children Age 2+. clinicaltrialvanguard.com. June 2026.

    Contemporary Pediatrics (sNDA acceptance and MUSE/long-term study context): FDA accepts roflumilast cream 0.3% sNDA to treat plaque psoriasis in children 2 to 5 years. contemporarypediatrics.com. 2025.

    DERMIS-1 and DERMIS-2 pooled PASI data (PMC): Roflumilast Cream 0.3% in Patients with Chronic Plaque Psoriasis: Pooled PASI and PASI-HD Results from the DERMIS Phase III Trials. PMC12619852.

    DERMIS Phase 2 adult trial NEJM publication: Lebwohl MG et al. Trial of Roflumilast Cream for Chronic Plaque Psoriasis. NEJM. 2020;383(3):229-239.

    DERMIS-1 trial registration: NCT04211363. ClinicalTrials.gov.

    DERMIS-2 trial registration: NCT04211389. ClinicalTrials.gov.

    MUSE 2-to-5 trial registration: NCT04746911. ClinicalTrials.gov.

    Long-term open-label trial registration: NCT04286607. ClinicalTrials.gov.

    Zoryve cream 0.3% prescribing information: ZORYVE (roflumilast) Cream 0.3% Prescribing Information. Arcutis Biotherapeutics. 2026.

    Zoryve approval history: Zoryve FDA Approval History. drugs.com.

    Pediatric psoriasis and plaque psoriasis overview: Psoriasis. StatPearls. NCBI.

    National Psoriasis Foundation: npf.org

    Patient resources: National Psoriasis Foundation: 1-800-723-9166 | Society for Pediatric Dermatology | Arcutis Arc+ patient support program | American Academy of Dermatology Find-a-Derm (pediatric dermatologists)

    Disclaimer: Health Evidence Digest provides general information about FDA approvals and health research for educational purposes. This content is not a substitute for professional medical advice. The expansion of Zoryve cream 0.3% to children aged 2 to 5 years is based on data from a small open-label pharmacokinetic study (n=10) and a long-term extension study in this age group, supported by the established efficacy and safety database in older patients. Treatment decisions for pediatric plaque psoriasis should be made in consultation with a board-certified pediatric dermatologist who can evaluate disease severity, body site involvement, and the full range of treatment options appropriate for the individual child.
  • Polycythemia Vera Requires Decades of Treatment. Besremi Is the Only Drug That Can Reduce the Mutant Clone Driving the Disease. The Besremi Pen Makes That Long-Term Commitment Easier to Keep.

    Polycythemia Vera Requires Decades of Treatment. Besremi Is the Only Drug That Can Reduce the Mutant Clone Driving the Disease. The Besremi Pen Makes That Long-Term Commitment Easier to Keep.

    The essentials: On June 26, 2026, the FDA approved the BESREMi Pen (ropeginterferon alfa-2b-njft, PharmaEssentia) as a new dosage form for the treatment of adult patients with polycythemia vera (PV). This is not a new drug, a new indication, or a new mechanism. The active molecule, the approved indication, and the dosing regimen are unchanged from the original Besremi pre-filled syringe approved in November 2021. What changed: the delivery device. The BESREMi Pen is a pre-filled pen injector supplied as 500 mcg in 0.5 mL solution, offering an alternative self-administration option to the pre-filled syringe. Both the pen and the pre-filled syringe remain commercially available. The pen does not require reconstitution, provides a simpler self-injection experience than a conventional syringe, and is expected to support treatment consistency and adherence in a disease that requires years of ongoing therapy. Dosing is unchanged: subcutaneous injection once every 2 weeks (with option to extend to every 4 weeks in maintenance). Injection sites: lower abdomen at least 2 inches from the navel, or upper thigh. The clinical case for Besremi itself rests on the Phase 3 PROUD-PV (NCT01949805) and Phase 3b extension CONTINUATION-PV (NCT02218047) trials, spanning more than 7 years of follow-up. Key long-term findings: 54.6% complete hematologic response (CHR) rate versus 34.9% for hydroxyurea or best available treatment at 3 years (rate ratio favoring ropeginterferon); 61% CHR at 7.5 years in the ropeginterferon arm; 80% hematologic response by laboratory criteria at extended follow-up; JAK2V617F allele burden reduced to less than 1% in 20.7% of ropeginterferon-treated patients versus 1.4% of controls at 6 years (p=0.0001); statistically significant advantage in event-free survival at maximum follow-up of 7.3 years (log-rank p=0.04). Besremi holds Orphan Drug Designation in the United States for PV. The BESREMi Pen commercial availability was expected in the weeks following the June 26 approval.

    Polycythemia vera is a cancer, but it does not behave the way most people think cancer behaves. It does not announce itself with a tumor. It does not typically cause pain or visible changes in the body in the early stages. It grows slowly, often over decades, in the bone marrow. What it does is overproduce blood cells, particularly red blood cells, at a pathological rate, thickening the blood and dramatically increasing the risk of life-threatening blood clots. And it does not go away. Once diagnosed, polycythemia vera requires management for life.

    For most of the past several decades, management meant controlling the blood count with phlebotomy and hydroxyurea, the latter being an oral chemotherapy agent that reduces cell production but does not touch the underlying mutant clone driving the disease. Patients on hydroxyurea have lower blood counts, lower thrombosis risk, and better near-term outcomes. What they do not have is any realistic prospect of disease modification at the genetic level.

    Besremi (ropeginterferon alfa-2b-njft, PharmaEssentia) changed that when it was approved in November 2021. It is the only FDA-approved therapy for PV with demonstrated ability to reduce the JAK2V617F mutant allele burden, the specific genetic driver of the disease in more than 95% of patients, in a sustained way over years of treatment. In a meaningful proportion of patients, the mutant clone approaches undetectable levels, a depth of molecular response that does not occur with hydroxyurea.

    The June 26, 2026 BESREMi Pen approval does not change the molecule, the indication, or the evidence base. It changes how patients get the drug from the vial into their bodies, and in a disease that demands consistent subcutaneous self-injection every 2 weeks for years, that matters more than it might sound.


    What Polycythemia Vera Is and Why It Is More Dangerous Than It Often Appears

    Polycythemia vera is a clonal myeloproliferative neoplasm arising from a disease-initiating hematopoietic stem cell in the bone marrow. The word “myeloproliferative” means that it causes excess production of blood cells; “clonal” means that this excess production originates from a single abnormal stem cell whose progeny progressively outcompete normal hematopoietic cells. The result is a chronic elevation of red blood cells (erythrocytosis), and usually also white blood cells and platelets.

    The elevated red cell mass increases blood viscosity, the thickness of the blood flowing through vessels. Thicker blood clots more readily, and the primary clinical consequence of untreated or inadequately controlled PV is thrombosis: blood clots that can cause strokes, heart attacks, deep vein thrombosis, pulmonary embolism, and abdominal vein thrombosis (Budd-Chiari syndrome), among others. These thromboembolic events are responsible for most of the early mortality in PV patients.

    PV is rare but not as rare as it is sometimes perceived. The incidence is approximately 2 to 3 per 100,000 persons per year, with prevalence estimated at approximately 44 to 57 per 100,000. In the United States, this represents tens of thousands of people living with the diagnosis at any given time. The condition is more common in adults over 60, though it can occur at any age, and is slightly more common in men than women.

    The JAK2V617F mutation: what it is and why it matters

    More than 95% of PV patients carry a specific somatic mutation in the JAK2 gene: JAK2V617F, a single nucleotide substitution at codon 617 that converts valine to phenylalanine. This mutation causes constitutive activation of the JAK-STAT signaling pathway, which normally requires growth factor binding to drive blood cell production. With the mutation, JAK2 is permanently switched on, driving uncontrolled proliferation of erythroid, myeloid, and megakaryocytic cell lines without needing the normal growth factor signal.

    The JAK2V617F mutation is the molecular diagnostic criterion for PV (alongside a markedly elevated erythropoietin threshold) and is also the therapeutic target for ropeginterferon. Measuring the JAK2V617F allele burden, the proportion of the patient’s hematopoietic cells carrying the mutant rather than normal JAK2, provides a quantitative measure of how much of the bone marrow has been taken over by the malignant clone. Reducing allele burden toward zero is the closest thing to remission that PV patients can currently achieve.

    Disease progression: why control matters beyond blood counts

    PV can transform over time to two more aggressive conditions: secondary myelofibrosis, in which the bone marrow becomes scarred and fibrotic and loses the ability to produce normal blood cells, and acute myeloid leukemia (AML), which carries a very poor prognosis. These transformations are more likely in patients with higher baseline JAK2V617F allele burden, longer disease duration, and inadequate control of the malignant clone.

    This transformation risk is one of the most important arguments for pursuing disease-modifying therapy rather than count control alone. Hydroxyurea reduces blood counts effectively but does not reduce JAK2V617F allele burden meaningfully and does not appear to reduce transformation risk. Ropeginterferon does both.


    How Ropeginterferon Works: The Interferon Mechanism in PV

    Interferon alpha has been used to treat PV for more than 30 years. The early rationale was its ability to suppress abnormal blood cell production and reduce thrombosis risk. What emerged over time from clinical observation was that interferon also seemed to reduce the JAK2V617F allele burden, suggesting an effect on the malignant stem cell clone itself, not just its downstream progeny.

    The molecular mechanism is not fully elucidated, but current evidence suggests interferon alpha activates interferon signaling pathways in hematopoietic stem cells that selectively impair JAK2V617F-mutant stem cell proliferation and survival while being better tolerated by normal (wild-type) stem cells. This relative selectivity creates a competitive advantage for the normal stem cell pool over time, allowing normal hematopoiesis to re-emerge as the mutant clone is progressively suppressed.

    Ropeginterferon alfa-2b is a next-generation mono-pegylated interferon specifically engineered for PV. The “pegylation” refers to attachment of a polyethylene glycol (PEG) chain to the interferon molecule, which extends the drug’s half-life substantially by slowing its clearance. Earlier pegylated interferons used multi-branched PEG chains (polyethylene glycol branched). Ropeginterferon uses a single linear PEG chain attached specifically at the proline amino acid, producing a more uniform molecular structure with improved pharmacokinetics and a longer half-life.

    The practical consequence: ropeginterferon achieves therapeutic interferon exposure with dosing every 2 weeks rather than the 2 to 3 times weekly dosing of conventional interferon alpha, and can extend to every 4 weeks in maintenance for well-controlled patients. This dramatically reduces the injection burden compared to older interferon formulations and makes long-term treatment feasible in a way that 3-times-weekly interferon injections were not.


    The Clinical Evidence: PROUD-PV and CONTINUATION-PV

    The FDA approval of Besremi in 2021 was supported primarily by data from the Phase 3 PROUD-PV trial (NCT01949805) and its Phase 3b extension, CONTINUATION-PV (NCT02218047). Together, these studies provide the most comprehensive long-term dataset for any cytoreductive treatment in PV, with follow-up extending to more than 7 years.

    PROUD-PV: Phase 3 randomized trial (12 months)

    PROUD-PV enrolled 254 adults with JAK2V617F-positive PV who were either hydroxyurea-naive or had received hydroxyurea for less than 3 years without achieving complete response, or with resistance or intolerance. Patients were randomized 1:1 to ropeginterferon alfa-2b or hydroxyurea for 12 months. The primary endpoint was complete hematologic response without progressive disease at 12 months.

    At 12 months, the response rates were similar between arms (non-inferiority met), consistent with the design intent of demonstrating that ropeginterferon was at least as effective as the established standard of care at 1 year while providing the potential for greater benefit over longer-term follow-up.

    CONTINUATION-PV: Long-term extension data

    Patients completing PROUD-PV were offered enrollment in CONTINUATION-PV, where ropeginterferon-treated patients continued the same drug and hydroxyurea-treated patients received best available treatment (hydroxyurea or other standard first-line therapy). This design allowed prospective observation of outcomes over years of ongoing treatment.

    OutcomeRopeginterferon alfa-2bHydroxyurea / best available treatmentFollow-up
    Complete hematologic response54.6%34.9%Year 3
    Complete hematologic response61%Not specified at this timepoint7.5 years
    Hematologic response by lab criteria80%Not separately reportedExtended follow-up
    JAK2V617F allele burden less than 1%20.7%1.4%Year 6; p=0.0001
    Event-free survival advantageYesReferenceMaximum 7.3 years; log-rank p=0.04

    Sources: Gisslinger H et al. Leukemia. 2022. Gisslinger H et al. Leukemia. 2023. PROUD-PV NCT01949805. CONTINUATION-PV NCT02218047.

    The 7.5-year data represent one of the longest prospective follow-up datasets for any treatment in PV. The CHR rate of 61% at 7.5 years in the ropeginterferon arm, combined with 80% achieving hematologic response by laboratory criteria, reflects durable disease control maintained over nearly a decade of treatment in many patients.

    The JAK2V617F allele burden finding is the most scientifically significant result in this dataset. At 6 years, 20.7% of ropeginterferon-treated patients had reduced their mutant allele burden to below 1%, essentially undetectable by standard assays, compared with only 1.4% of patients on hydroxyurea or best available treatment (p=0.0001). In a small subset of patients whose allele burden fell below 10% during treatment, discontinuation of ropeginterferon has been followed by persistent hematologic response, a degree of treatment-free remission that is not achievable with any other currently approved PV therapy.

    The event-free survival advantage, defined as time to disease transformation, thromboembolic events, or death, reached statistical significance at a maximum follow-up of 7.3 years (log-rank p=0.04), providing the first prospective evidence that ropeginterferon may alter the natural course of PV beyond blood count control.


    The BESREMi Pen: What It Is and Why the Delivery Change Matters

    The BESREMi Pen does not change anything about the drug, its indication, its mechanism, or its dosing schedule. What it changes is the physical experience of self-injection, and for patients with PV who will need subcutaneous injections every 2 to 4 weeks for years or decades, that experience matters.

    What the pen is

    The BESREMi Pen is a pre-filled single-dose pen injector containing 500 mcg of ropeginterferon alfa-2b-njft in 0.5 mL solution, the same concentration and dose as the existing pre-filled syringe. It is administered subcutaneously into the lower abdomen (at least 2 inches from the navel) or the upper thigh, rotating injection sites.

    A pre-filled pen injector differs from a conventional pre-filled syringe in several practically meaningful ways:

    The pen conceals the needle until the moment of injection. For patients with needle anxiety, not seeing the needle before and during injection reduces psychological distress and may reduce injection-related avoidance or delay.

    The pen delivers the injection with a single button press or cap removal mechanism rather than requiring the patient to manually depress a plunger. This reduces the manual dexterity required, which is relevant for older patients or patients with arthritis or hand tremor who may find syringe plunger depression difficult.

    The pen holds a consistent dose with less opportunity for dosing error than manual syringe loading. Because Besremi is supplied as a pre-filled device in both formats, dose accuracy is already well-controlled with the syringe; the pen adds a layer of simplicity in the injection step itself.

    The pen format is familiar to many patients with chronic conditions who have used insulin pens, growth hormone pens, or other biologic pens, and the learning curve for patients already familiar with pen injectors is lower than for patients switching from the syringe.

    Why adherence is the central clinical issue in PV

    Dr. John Mascarenhas, Director of the Center of Excellence for Blood Cancers and Myeloid Disorders at Mount Sinai, noted: “Treatment consistency is critical for managing PV, and this device has the potential to make a meaningful positive impact on patients’ lives by simplifying self-administration and supporting better adherence.”

    That statement identifies the core clinical problem the BESREMi Pen addresses. The PROUD-PV and CONTINUATION-PV long-term data show that the molecular and hematologic benefits of ropeginterferon deepen progressively over years of treatment. The JAK2V617F allele burden reduction that reaches near-undetectable levels at 6 years did not appear at 1 year or 2 years. These results required patients to continue injecting consistently for many years to accumulate.

    A patient who finds the injection process burdensome, painful, anxiety-provoking, or technically difficult is more likely to delay, skip, or discontinue injections. In PV, where the standard treatment is indefinite and the disease-modifying benefit is cumulative, every missed injection is a missed opportunity for allele burden reduction. Device improvements that reduce injection barriers directly serve the clinical goals of the treatment.


    Dosing: What Patients and Prescribers Need to Know

    The dosing regimen for Besremi is the same regardless of whether the pen or the syringe is used. The FDA approval of the BESREMi Pen does not introduce a new titration scheme; it provides the same drug in a different delivery format.

    The standard starting and maintenance approach for Besremi depends on whether the patient is receiving concomitant hydroxyurea at treatment initiation:

    Patients not on hydroxyurea: Start at 100 mcg subcutaneously every 2 weeks. Titrate the dose every 2 weeks based on hematologic response, targeting normalization of hematocrit below 45%, platelet count, and white blood cell count. Once stable control is achieved, dosing interval may be extended to every 4 weeks in some patients.

    Patients transitioning from hydroxyurea: Initiate Besremi alongside hydroxyurea, then taper hydroxyurea gradually as ropeginterferon takes effect, ultimately discontinuing hydroxyurea when blood counts are well-controlled on ropeginterferon alone.

    Target dose: The optimal maintenance dose varies by patient; in CONTINUATION-PV, the median cumulative 4-weekly dose in the sixth year of treatment was 499 mcg (IQR 268 to 782 mcg), with 61.9% of patients receiving doses at an extended 3- or 4-week interval.

    The dose titration of ropeginterferon is individualized, which means the prescribing clinician should be experienced in managing PV and comfortable with the titration process. The full prescribing information from PharmaEssentia should be reviewed for dose modification guidance related to hematologic toxicity, transaminase elevations, and other adverse events.


    Safety: The Established Besremi Profile

    The BESREMi Pen carries the same safety profile and the same boxed warning as the pre-filled syringe formulation. No new safety signals are associated with the pen device itself.

    Boxed warning: risk of serious disorders

    The Besremi prescribing information carries a boxed warning, the FDA’s strongest safety alert, for the risk of serious disorders including neuropsychiatric, autoimmune, ischemic, and infectious disorders. These risks are associated with the interferon alpha class broadly and have been observed at the doses used in therapeutic applications.

    Neuropsychiatric: Depression, suicidal ideation, and psychosis have been reported with interferon alfa therapy. Patients should be monitored closely for new or worsening psychiatric symptoms. Besremi should not be used in patients with a history of severe psychiatric disorders that are not well-controlled. Patients should be counseled to report any mood changes, sleep disturbances, or behavioral changes to their healthcare provider.

    Autoimmune disorders: Interferon alfa can exacerbate or trigger autoimmune conditions including thyroid disease, psoriasis, systemic lupus erythematosus, and rheumatoid arthritis. Thyroid function should be monitored before and periodically during treatment.

    Ischemic disorders: Ischemic events including cerebrovascular accidents, myocardial infarction, and peripheral vascular disease have been reported. Patients with pre-existing cardiovascular risk factors should be monitored appropriately.

    Infectious disorders: Immunosuppressive effects of interferon increase infection susceptibility. Serious and potentially fatal infections have been reported.

    Additional warnings and precautions:

    Safety itemClinical guidance
    HepatotoxicityMonitor liver function tests at baseline and during treatment; reduce or discontinue dose for significant transaminase elevation
    MyelosuppressionCBC monitoring at baseline and periodically; dose modification for significant cytopenias
    Pulmonary disordersMonitor for new or worsening pulmonary symptoms; rare but serious pulmonary adverse events reported with interferon class
    Ophthalmologic disordersRetinal disorders have been reported; ophthalmologic evaluation if new visual symptoms develop
    Driving and machineryAdvise patients to avoid driving or operating machinery if they experience dizziness, somnolence, or hallucination
    Embryo-fetal toxicityInterferon alfa can cause fetal harm; effective contraception required during treatment; women of childbearing potential should be counseled

    Common adverse reactions in PROUD-PV and CONTINUATION-PV included fatigue, arthralgia, influenza-like illness, pruritus, elevated liver enzymes, and injection site reactions. These are consistent with the interferon class profile. Most adverse events were mild to moderate and managed through dose adjustment or supportive care. The improved dosing schedule (every 2 to 4 weeks versus the 3-times-weekly schedule of older interferons) contributes substantially to the better tolerability profile compared to earlier interferon formulations used in PV.


    Where Besremi Fits in the Current PV Treatment Landscape

    PV management in 2026 centers on risk stratification based on age and prior thrombotic events, then selection among cytoreductive options for moderate-to-high-risk patients:

    TreatmentMechanismRole in PVMolecular effect
    PhlebotomyReduces red cell mass directlyUniversal; used to control hematocritNone
    Low-dose aspirinAntiplateletUniversal (absent specific contraindications)None
    HydroxyureaCytoreductive (oral chemotherapy)First-line cytoreduction for most patientsMinimal to no JAK2 allele burden reduction
    Besremi (ropeginterferon alfa-2b)Interferon-mediated suppression of mutant JAK2 cloneFirst-line or second-line cytoreduction; preferred for younger patients, women of childbearing age, patients desiring disease modificationSustained reduction in JAK2V617F allele burden; potential for treatment-free remission in deep molecular responders
    Ruxolitinib (Jakafi)JAK1/2 inhibitorSecond-line for hydroxyurea-intolerant or resistant patientsReduces inflammation and splenomegaly; limited molecular effect

    Besremi is particularly favored in the 2025 KDIGO clinical practice guidelines and NCCN guidelines for younger patients who will live with PV for decades and for whom disease modification at the clonal level is the most important long-term goal. It is also preferred in women of childbearing potential because hydroxyurea is teratogenic and cannot be used safely during pregnancy, while interferon alfa does not cross the placenta and has a more acceptable safety profile in this context.

    The choice between Besremi and hydroxyurea as initial cytoreductive therapy involves a careful discussion with the patient about self-injection every 2 to 4 weeks, the side effect profile of interferon versus hydroxyurea, the long-term molecular benefits of ropeginterferon, and the patient’s own goals for treatment. The BESREMi Pen makes the self-injection component of that discussion easier to navigate positively.


    What This Means for Patients and Hematologists

    For patients currently on Besremi pre-filled syringe

    The pen is an alternative option, not a mandatory switch. Patients who are comfortable and adherent with the pre-filled syringe can continue using it; the syringe remains commercially available. Patients who would benefit from a simpler injection experience, who have needle anxiety, or who have dexterity concerns should discuss transitioning to the pen with their hematologist or their specialty pharmacy.

    For patients newly starting Besremi

    The pen and the syringe contain the same drug at the same concentration and dose. The choice between them at treatment initiation is a patient preference and clinical discussion decision, not a clinical efficacy decision. For patients new to subcutaneous self-injection, the pen format may represent a lower-anxiety starting point.

    For hematologists

    The BESREMi Pen approval is administratively simple: same drug, same indication, same prescribing requirements. The clinical value is in supporting the treatment adherence that the long-term evidence base requires. PharmaEssentia’s patient support program, Aspire, provides injection training and support for both the syringe and pen formulations.

    As Dr. Mascarenhas’ comment indicates, the hematology community has long recognized that ropeginterferon’s clinical benefits are proportional to treatment duration and consistency. A device that reduces barriers to consistent self-injection is aligned with achieving the molecular depth of response that the PROUD-PV and CONTINUATION-PV long-term data demonstrate is achievable.

    For related HED coverage on myeloproliferative neoplasms and hematologic malignancy drug approvals, see our post on Tregzi (marnetegragene autotemcel) as the first precision-engineered cell therapy for allogeneic stem cell transplantation in blood cancers and our coverage of Sarclisa Escena as the first anticancer drug delivered via an on-body injector.

    For patients and families navigating a polycythemia vera diagnosis, the MPN Research Foundation (mpnresearchfoundation.org) and the MPN Advocacy and Education International maintain current patient resources, treatment information, and connection to the MPN specialist community.


    Sources

    PharmaEssentia FDA approval press release: PharmaEssentia Announces FDA Approval and U.S. Launch of BESREMi Pen (ropeginterferon alfa-2b-njft) for Polycythemia Vera. BusinessWire. June 26, 2026.

    PharmaEssentia newsroom: BESREMi Pen FDA approval and U.S. launch. us.pharmaessentia.com. June 26, 2026.

    Drugs.com approval news: PharmaEssentia Announces FDA Approval and U.S. Launch of BESREMi Pen. drugs.com. June 26, 2026.

    OncLive (dosing schedule, long-term data, Dr. Mascarenhas quote): FDA Approves Prefilled Pen for Ropeginterferon Alfa-2b in Polycythemia Vera. onclive.com. June 2026.

    Oncology Nurse Advisor (pen specifications and dosing): New Pen Formulation of Besremi Approved for Polycythemia Vera. oncologynurseadvisor.com. June 2026.

    Oncology Nursing News (nursing practice context): FDA Approves BESREMi Pen for Self-Administration in Polycythemia Vera. oncnursingnews.com. June 2026.

    Healio (device details): Prefilled pen device gains FDA approval for adults with polycythemia vera. healio.com. June 2026.

    PROUD-PV primary publication: Gisslinger H et al. Ropeginterferon alfa-2b versus standard therapy for polycythemia vera (PROUD-PV and CONTINUATION-PV): a randomised, non-inferiority, phase 3 trial and its extension study. Lancet Haematol. 2020;7(3):e196-e208.

    CONTINUATION-PV long-term outcomes (Leukemia 2022): Gisslinger H et al. Long-term outcomes of polycythemia vera patients treated with ropeginterferon alfa-2b. Leukemia. 2022.

    Event-free survival data (Leukemia 2023): Gisslinger H et al. Event-free survival in patients with polycythemia vera treated with ropeginterferon alfa-2b versus best available treatment. Leukemia. 2023.

    7.5-year QOL and long-term response data (OncLive EHA 2022 coverage): Ropeginterferon Alfa-2b Demonstrates Long-Term QOL Improvements in Polycythemia Vera. onclive.com.

    Long-term outcomes PMC publication: Long-term outcomes of polycythemia vera patients treated with ropeginterferon alfa-2b. PMC9061291.

    PROUD-PV trial registration: NCT01949805. ClinicalTrials.gov.

    CONTINUATION-PV trial registration: NCT02218047. ClinicalTrials.gov.

    Original Besremi FDA approval (2021): FDA approves ropeginterferon alfa-2b-njft for polycythemia vera. FDA.gov. November 12, 2021.

    Polycythemia vera StatPearls overview: Polycythemia Vera. StatPearls. NCBI.

    JAK2V617F molecular biology and long-term outcomes: Long-term outcomes of PV patients treated with ropeginterferon. PMC10539163.

    Besremi prescribing information: BESREMi (ropeginterferon alfa-2b-njft) Prescribing Information. PharmaEssentia. 2026.

    Besremi approval history: Besremi FDA Approval History. drugs.com.

    Patient resources: MPN Research Foundation | MPN Advocacy and Education International | PharmaEssentia Aspire patient support program | Leukemia and Lymphoma Society MPN resources

    Disclaimer: Health Evidence Digest provides general information about FDA approvals and health research for educational purposes. This content is not a substitute for professional medical advice. The BESREMi Pen approval does not change the approved indication, dosing, or safety profile of ropeginterferon alfa-2b-njft. Besremi carries a boxed warning for the risk of serious disorders including neuropsychiatric, autoimmune, ischemic, and infectious conditions. All treatment decisions for polycythemia vera, including initiation and dose titration of ropeginterferon, should be made in close collaboration with a board-certified hematologist experienced in the management of myeloproliferative neoplasms.
  • Multiple Myeloma Patients Spend Hours in Infusion Chairs Getting Anti-CD38 Antibodies. Sarclisa Escena Just Became the First Anticancer Drug Delivered by an On-Body Injector. Here Is What That Means.

    Multiple Myeloma Patients Spend Hours in Infusion Chairs Getting Anti-CD38 Antibodies. Sarclisa Escena Just Became the First Anticancer Drug Delivered by an On-Body Injector. Here Is What That Means.

    The essentials: On July 9 to 10, 2026, the FDA approved Sarclisa Escena (isatuximab-irfc, Sanofi-Aventis) for subcutaneous injection across all currently approved multiple myeloma indications for IV Sarclisa. Sarclisa Escena is the same isatuximab molecule as IV Sarclisa, delivered subcutaneously rather than intravenously. It is the first anticancer treatment approved for administration via an on-body injector (OBI). The approved indications (matching existing IV Sarclisa indications): in combination with pomalidomide and dexamethasone (Pd) for adults with multiple myeloma who have received at least one prior line of therapy including lenalidomide and a proteasome inhibitor; in combination with carfilzomib and dexamethasone (Kd) for adults with relapsed or refractory multiple myeloma after 1 to 3 prior lines of therapy; in combination with bortezomib, lenalidomide, and dexamethasone (VRd) for adults with newly diagnosed multiple myeloma not eligible for autologous stem cell transplantation. Administration: 1,400 mg fixed dose subcutaneous injection using the CirCLIQ on-body delivery system (OBDS) made by Enable Injections, or manual subcutaneous injection with a syringe and infusion set. The OBI is a wearable device with a concealed, retractable 30-gauge needle that delivers the drug hands-free via low-pressure interstitial flow. No hyaluronidase required. Weight-independent flat dosing replaces the weight-based IV dosing (10 mg/kg). The clinical basis: Phase 3 IRAKLIA (NCT05405166), 531 patients randomized 1:1 to subcutaneous OBI isatuximab plus Pd or IV isatuximab plus Pd. Published in Journal of Clinical Oncology. Co-primary endpoints: ORR and steady-state trough concentration. ORR 71.1% (SC-OBI) versus 70.5% (IV); relative risk 1.008 (95% CI 0.903 to 1.126); p=0.0006, meeting non-inferiority. Mean trough Ctrough at cycle 6 day 1: 499 μg/mL (SC-OBI) versus 340 μg/mL (IV); geometric mean ratio 1.532 (90% CI 1.316 to 1.784), also non-inferior and in fact higher with SC. Systemic infusion reactions: 1.5% (SC-OBI) versus 25.0% (IV). Injection site reactions: 0.4% of all OBI injections, all grade 1 or 2. 99.9% of injections completed without interruption. Patient satisfaction: 70% satisfied or very satisfied with SC-OBI versus 53.4% with IV (OR 2.036; 95% CI 1.425 to 2.908; p=0.0001). Additional supporting studies: IZALCO (NCT05704049, Phase 2, Kd combination); IsaSocut/ISASCOUT (NCT05889221, Phase 2, VRd combination, transplant-ineligible NDMM). European Commission approved Sarclisa Escena on June 8, 2026, across all indications.

    Multiple myeloma is a cancer that requires years of treatment. Not months. Years. Patients who achieve remission on first-line therapy eventually relapse and begin second-line treatment. Then third-line. Then fourth. The treatment calendar for a myeloma patient who responds well can span a decade or more of clinic visits, drug combinations, and ongoing monitoring. During that time, every hour spent sitting in an infusion chair is an hour that is not spent at work, with family, or simply living without the constant reminder that cancer still defines the schedule.

    Anti-CD38 antibodies, which include daratumumab (Darzalex) and isatuximab (Sarclisa), are among the most effective drugs in the myeloma armamentarium. They are also, in their intravenous form, among the most time-intensive. The first IV infusion of an anti-CD38 antibody typically takes 4 to 6 hours due to pre-medication requirements and slow infusion rates to manage infusion reactions. Subsequent infusions are faster but still take 1 to 3 hours. For a drug given weekly in cycle 1 and then every 2 weeks for relapsed disease, this adds up quickly.

    Daratumumab solved this with its subcutaneous formulation Darzalex Faspro, approved in 2020, which uses hyaluronidase to deliver the drug subcutaneously in a few minutes. Sarclisa Escena, approved July 9, 2026, solves the same problem for isatuximab, but takes the approach in a genuinely novel direction: it is the first anticancer drug in history approved for delivery via an on-body injector, a wearable device that administers the injection hands-free without the patient needing to hold a syringe, without requiring hyaluronidase, and with a concealed retractable needle that eliminates needle-stick risk for both patient and provider.

    The Phase 3 IRAKLIA trial showed that the SC-OBI approach is not merely convenient. It is clinically equivalent to IV isatuximab on every meaningful efficacy measure, produces higher steady-state drug concentrations, and reduces systemic infusion reactions from 25% with IV to 1.5% with the on-body approach.


    What Multiple Myeloma Is and Why CD38 Is Such an Important Target

    Multiple myeloma is a cancer of plasma cells, the antibody-producing cells of the immune system that reside in the bone marrow. In myeloma, malignant plasma cells proliferate uncontrollably, crowd out normal blood cell production, and produce large quantities of a dysfunctional monoclonal protein (M-protein) that serves as a disease biomarker but can also damage the kidneys. The resulting clinical picture includes anemia, bone lesions, kidney damage, immunosuppression, and hypercalcemia.

    Multiple myeloma is the second most common blood cancer in the United States, with approximately 36,000 new diagnoses and 12,000 deaths annually. It remains incurable for most patients, though effective modern treatments have extended median survival from approximately 3 years in the 1990s to 6 to 8 years or more for many patients today. Patients cycle through treatment regimens, entering remission, eventually relapsing, and then requiring a new regimen that typically includes drugs from different mechanistic classes.

    CD38 is a transmembrane glycoprotein expressed at very high levels on myeloma plasma cells, making it an ideal therapeutic target. CD38 is expressed on normal lymphoid and myeloid cells as well, but at much lower levels than on myeloma cells, providing a therapeutic window for anti-CD38 antibodies to selectively target the malignant population.

    Anti-CD38 antibodies kill myeloma cells through multiple mechanisms: antibody-dependent cellular cytotoxicity (ADCC), antibody-dependent cellular phagocytosis (ADCP), complement-dependent cytotoxicity (CDC), and direct apoptosis induction. They also deplete immunosuppressive CD38-positive regulatory T cells and regulatory B cells, which may additionally improve the anti-tumor immune response. This multi-mechanism killing is one reason CD38-directed antibodies are effective even in heavily pretreated myeloma and why they have become a backbone of therapy across multiple lines of treatment.


    What Isatuximab Is and How Sarclisa Escena Relates to IV Sarclisa

    Isatuximab (Sarclisa) is a CD38-directed IgG1 monoclonal antibody that differs from daratumumab in the specific epitope on CD38 it binds and in its mechanism of triggering apoptosis (daratumumab requires cross-linking for apoptotic signaling; isatuximab induces apoptosis through receptor clustering independent of cross-linking). In clinical practice, both are effective CD38-targeting antibodies used in complementary regimens in the myeloma treatment landscape.

    IV Sarclisa was approved by the FDA in:

    • March 2020 for relapsed/refractory myeloma in combination with pomalidomide and dexamethasone (ICARIA-MM trial)
    • March 2021 in combination with carfilzomib and dexamethasone (IKEMA trial)
    • March 2024 in combination with VRd for transplant-ineligible newly diagnosed myeloma (IMROZ trial)

    Sarclisa Escena is not a new drug. It is the same isatuximab-irfc molecule delivered by a different route. The “Escena” suffix distinguishes the subcutaneous formulation from the IV formulation for prescribing, dispensing, and packaging purposes. All three indications approved for IV Sarclisa are now equally approved for Sarclisa Escena SC, with the same combination regimen partners and the same patient eligibility criteria.

    The dose change is meaningful: IV isatuximab is dosed at 10 mg/kg, meaning the volume infused varies by patient weight. Sarclisa Escena uses a fixed flat dose of 1,400 mg regardless of patient weight. This simplifies preparation and administration, reduces the potential for weight-based dosing errors, and enables the on-body injector to deliver a predetermined fixed volume to every patient.


    The CirCLIQ On-Body Delivery System: What It Is and How It Works

    The CirCLIQ on-body delivery system (OBDS), manufactured by Enable Injections of Cincinnati, Ohio, is the central innovation of the Sarclisa Escena approval. Understanding what it does requires understanding why subcutaneous delivery of large-volume biologics has historically required either hyaluronidase or a slow infusion.

    The subcutaneous space has limited capacity. Subcutaneous tissues resist high-pressure injection of large volumes because the dense extracellular matrix of hyaluronan and collagen creates physical resistance. Conventional subcutaneous injections of most drugs deliver volumes under 1 to 2 mL. Biologics like anti-CD38 antibodies at therapeutic doses require much larger volumes.

    There are two established solutions. Hyaluronidase (used in Darzalex Faspro and Keytruda Qlex) temporarily breaks down the hyaluronan matrix, allowing larger volumes to be injected rapidly by dispersing through the loosened tissue. The CirCLIQ approach takes a different path: it uses low-pressure, interstitial-rate delivery, meaning it delivers the drug slowly enough that the subcutaneous tissue can accommodate the volume without requiring enzymatic disruption of the matrix.

    Concretely, the CirCLIQ device:

    • Is worn on the body surface (typically the abdomen) and attached by the patient or healthcare provider before administration begins
    • Contains a single-use, concealed, retractable 30-gauge needle that inserts automatically when activated, eliminating visible needle exposure and reducing sharps anxiety for needle-phobic patients
    • Delivers the drug hands-free once activated, freeing the patient and provider from holding a syringe during the infusion period
    • Uses flow rates calibrated to the patient’s interstitial pressure rather than a fixed pump rate, individualized delivery based on how the specific tissue responds
    • Does not require hyaluronidase as a co-formulation or co-injection
    • Completes drug delivery in approximately 7 to 9 minutes per the IRAKLIA experience, far shorter than IV infusions but longer than the 1 to 2 minutes for Keytruda Qlex’s conventional SC injection

    A critical safety feature: the needle retracts automatically after injection completion, preventing accidental needle-stick injuries. In IRAKLIA, 99.9% of all OBI injections (5,145 total injections analyzed) completed without interruption, demonstrating exceptional mechanical reliability across a large real-world operational dataset.

    For oncology practices, this also means nursing workload is different. Rather than manually maintaining an IV line and titrating infusion rates through an infusion pump, a nurse or medical assistant attaches the OBI device and activates it. The patient then waits, wearing the device, until delivery completes. The hands-free nature means nursing attention can be allocated elsewhere during the delivery period.


    The IRAKLIA Trial: Full Data

    Design

    IRAKLIA (NCT05405166) was an international, multicenter, open-label, randomized, Phase 3 non-inferiority trial. It enrolled 531 adults (age 18 or older) with relapsed/refractory multiple myeloma who had received at least one prior line of therapy. Patients were randomized 1:1 to:

    • Sarclisa Escena 1,400 mg SC via CirCLIQ OBI plus pomalidomide plus dexamethasone (n=263)
    • IV isatuximab 10 mg/kg plus pomalidomide plus dexamethasone (n=268)

    Both arms received isatuximab weekly in cycle 1, then every 2 weeks. Pomalidomide 4 mg daily on days 1 to 21 and dexamethasone 40 mg weekly (20 mg for patients aged 75 or older) were the standard partner regimen.

    Co-primary endpoints were ORR (by Independent Review Committee using 2016 IMWG criteria) and isatuximab trough plasma concentration at steady state (Ctrough at cycle 6, day 1 predose). Non-inferiority was declared if both primary endpoints met their prespecified non-inferiority margins. The trial was published in the Journal of Clinical Oncology (JCO) with a 12-month median follow-up.

    Efficacy results

    EndpointSC-OBI isatuximab (n=263)IV isatuximab (n=268)Result
    ORR (co-primary)71.1%70.5%Relative risk 1.008 (95% CI 0.903 to 1.126); p=0.0006; non-inferior
    Mean Ctrough at C6D1 (co-primary)499 μg/mL (SD 259)340 μg/mL (SD 169)Geometric mean ratio 1.532 (90% CI 1.316 to 1.784); non-inferior
    VGPR or better rateSimilar between armsSimilar between armsComparable depth of response
    Patient satisfaction (satisfied or very satisfied)70%53.4%OR 2.036 (95% CI 1.425 to 2.908); p=0.0001
    Median follow-up12 months12 months—

    Source: Richardson PG et al. IRAKLIA: Isatuximab Subcutaneous by On-Body Injector Versus Isatuximab Intravenous Plus Pd in R/R MM. JCO. 2025. doi:10.1200/JCO-25-00744. NCT05405166.

    The ORR non-inferiority result is the core efficacy finding: 71.1% versus 70.5%, a difference of 0.6 percentage points in a trial that randomized 531 patients, establishes that the SC-OBI route delivers identical anti-tumor activity to IV administration. The non-inferiority margin was met with high statistical confidence (p=0.0006).

    The Ctrough finding is particularly notable: the SC route actually achieved a higher mean steady-state trough concentration (499 μg/mL) than the IV route (340 μg/mL). This is not a paradox. With subcutaneous administration, drug is absorbed gradually from the subcutaneous depot over time, producing a flatter pharmacokinetic curve with higher trough levels compared to the sharp peak and faster decline seen with IV infusion. Higher troughs are generally associated with better sustained target coverage and may contribute to at least comparable or potentially superior outcomes with the SC formulation over longer follow-up periods.

    The patient satisfaction finding (70% satisfied or very satisfied with SC-OBI versus 53.4% with IV, p=0.0001) is a patient-reported outcome that the trial was specifically designed to capture and the FDA considered in its evaluation. A statistically significant, nearly 17-percentage-point improvement in patient satisfaction with the same clinical efficacy is a meaningful clinical finding, not a marketing data point.

    Safety results

    Safety itemSC-OBIIVClinical relevance
    Systemic infusion-related reactions1.5%25.0%Dramatic reduction; one of the most important safety differences
    Local injection site reactions0.4% of injections (all grade 1 or 2)—Rare, mild, and self-limiting
    Grade 3 or higher treatment-emergent adverse events81.7%76.1%Numerically higher with SC; reflects complex relapsed/refractory myeloma population; no unexpected signals
    Treatment discontinuation due to injection reactions0Not reportedNo discontinuations from injection site events with SC
    Injections completed without interruption99.9% (5,144 of 5,145)—Exceptional device reliability

    Source: JCO IRAKLIA publication; Applied Clinical Trials Online IRAKLIA/IZALCO data summary.

    The infusion reaction reduction from 25% to 1.5% is the most clinically impactful safety finding. Infusion-related reactions (IRRs) with IV anti-CD38 antibodies are a well-established class effect: daratumumab and isatuximab both require premedication with antihistamines, corticosteroids, and antipyretics before each IV infusion, and the first infusion is typically given slowly over 4 to 6 hours precisely because of IRR risk. These reactions, while usually manageable, add time, require nursing monitoring, and occasionally require interruption or rate adjustment. Some patients experience reactions severe enough to require treatment delays.

    The 1.5% systemic reaction rate with SC-OBI means the premedication burden and the nursing monitoring for systemic reactions are dramatically reduced, not eliminated but reduced to an extent that meaningfully changes the clinical experience of receiving isatuximab.

    The numerically higher grade 3 or higher TEAE rate with SC (81.7% versus 76.1%) reflects the overall adverse event burden of treating relapsed/refractory myeloma rather than a SC-specific safety concern. These events are consistent with the established IV isatuximab safety profile and reflect the toxicity of the full triplet regimen (isatuximab plus pomalidomide plus dexamethasone) in a population who has already received multiple prior therapies.

    Supporting studies: IZALCO and ISASCOUT

    Beyond IRAKLIA, the FDA’s approval across all three indications was further supported by:

    IZALCO (NCT05704049): Phase 2 study evaluating SC isatuximab via OBI in combination with carfilzomib and dexamethasone (Kd) in relapsed/refractory myeloma. In IZALCO, approximately 75% of patients preferred the OBI approach over manual subcutaneous injection, with high efficacy and minimal injection site reactions, providing patient preference data for the Kd combination regimen.

    IsaSocut/ISASCOUT (NCT05889221): Phase 2 study evaluating SC isatuximab in combination with VRd in transplant-ineligible newly diagnosed myeloma, providing supportive data for the NDMM indication.


    Sarclisa Escena’s Complete Indication Coverage

    IndicationPartnersPatient populationApproval basis
    Relapsed/refractory MM, at least 1 prior line including lenalidomide and a PIPomalidomide plus dexamethasone (Pd)AdultsIRAKLIA Phase 3 (primary pivotal)
    Relapsed/refractory MM, 1 to 3 prior linesCarfilzomib plus dexamethasone (Kd)AdultsIZALCO Phase 2 plus IV IKEMA extrapolation
    Newly diagnosed MM, transplant-ineligibleBortezomib plus lenalidomide plus dexamethasone (VRd)AdultsISASCOUT Phase 2 plus IV IMROZ extrapolation

    Safety: What the Full Prescribing Information Covers

    The safety profile of Sarclisa Escena follows the established profile of IV isatuximab with the key modification of substantially reduced systemic infusion reactions and the addition of local injection site reaction monitoring.

    Warnings and precautions from the Sarclisa Escena prescribing information:

    Hypersensitivity and administration reactions: Serious hypersensitivity reactions, including anaphylaxis, have been reported with isatuximab. For SC administration, systemic reactions occur at a dramatically lower rate than with IV (1.5% versus 25% in IRAKLIA), but monitoring for hypersensitivity remains required. Premedication with corticosteroids, antihistamines, and antipyretics is still recommended before administration, though the required observation period post-administration may differ from IV protocols. Clinicians should follow the Sarclisa Escena prescribing information specifically for SC premedication and monitoring guidance.

    Neutropenia: Neutropenia is one of the most common and serious adverse events with isatuximab-containing regimens. Grade 3 or higher neutropenia is expected in a substantial proportion of patients, particularly when combined with pomalidomide. CBC monitoring before each cycle is standard. G-CSF support may be required. Dose modifications for neutropenia follow the regimen-specific guidance in the prescribing information.

    Infections: Isatuximab causes immunosuppression through depletion of CD38-positive immune cells. Serious infections including pneumonia, upper respiratory tract infections, and opportunistic infections have been reported. Prophylactic antimicrobial coverage consistent with institutional protocols for myeloma regimens should be considered.

    Secondary primary malignancies: As with other myeloma regimens involving immunomodulatory drugs (IMiDs), secondary primary malignancies have been reported. Routine monitoring is recommended.

    Laboratory test interference: Isatuximab, as an IgG kappa monoclonal antibody, may be detected by serum protein electrophoresis and immunofixation assays used to monitor M-protein, potentially interfering with disease response assessment. This is a known class effect of anti-CD38 antibodies, and the prescribing information addresses how to distinguish isatuximab signal from M-protein response.

    Embryo-fetal toxicity: Isatuximab can cause fetal harm. Females of reproductive potential should use effective contraception during treatment and for 5 months after the last dose. Males with female partners of reproductive potential should use effective contraception during treatment and for 3 months after the last dose.


    What This Means for Patients and Oncology Practices

    For patients

    For a patient with relapsed myeloma starting isatuximab-Pd in the second or later line, Sarclisa Escena offers the same clinical activity as IV Sarclisa with three meaningful practical advantages: substantially fewer systemic infusion reactions (1.5% versus 25%), no IV line required, and a device-based administration that eliminates the need to sit connected to an IV drip for an extended period.

    The administration time with the OBI, approximately 7 to 9 minutes for the drug delivery itself plus setup and monitoring time, is not as fast as a 1- to 2-minute SC push injection. But it is substantially shorter than a 1- to 3-hour IV infusion on subsequent cycles, and the fact that it is hands-free changes the character of the clinical visit. The patient wears the device and waits; the nurse does not need to maintain a drip line throughout.

    For patients receiving isatuximab as part of the VRd regimen for newly diagnosed transplant-ineligible disease, where therapy may continue for years, the cumulative reduction in infusion chair time and in systemic IRR events is substantial over a full treatment course.

    The question of whether home administration of Sarclisa Escena is possible in the future is a natural one given the on-body injector format. The current approval specifies administration with a healthcare provider present. Sanofi has indicated that home administration is a future potential that the technology enables, but it is not part of the current label or commercial rollout.

    For oncology practices

    The CirCLIQ OBI changes the nursing workflow for isatuximab administration in ways that vary by practice setting. Setup, patient education on wearing the device, and post-administration monitoring remain required. But the hands-free delivery frees nursing time during the actual drug administration period compared to IV management. For infusion centers operating at capacity with long chair times, the shift from 1 to 3 hours of IV infusion to a shorter SC OBI session could increase throughput.

    The absence of hyaluronidase in the Sarclisa Escena formulation is also a practical supply chain point: no separate co-formulation is required, and the flat 1,400 mg dose eliminates weight-based calculation and the preparation variability that comes with it.

    As Dr. Mohamad Mohty, Professor of Hematology at Sorbonne University and Head of Clinical Hematology and Cellular Therapy at Saint-Antoine Hospital in Paris, noted: “The ability to administer a therapy through an on-body injector, particularly an anti-CD38 monoclonal antibody with well-established efficacy, either in the clinic or at home, represents a meaningful step forward.”

    For related HED coverage on multiple myeloma therapeutics, see our posts on Pomalyst (pomalidomide) losing exclusivity and what generic pomalidomide means for myeloma access in the 2026 LOE series, and on the Tregzi (marnetegragene autotemcel) approval for allogeneic stem cell transplantation in blood cancers.

    For patients and families navigating a multiple myeloma diagnosis, the Multiple Myeloma Research Foundation (themmrf.org; 1-888-841-6673) and the International Myeloma Foundation (myeloma.org; 1-800-452-CURE) maintain current patient resources, treatment information, and clinical trial directories.


    Sources

    FDA approval announcement: FDA approves isatuximab-irfc for subcutaneous injection for multiple myeloma indications. FDA.gov. July 9, 2026.

    Sanofi FDA approval press release: Sanofi’s subcutaneous Sarclisa Escena approved in the US as first anticancer treatment administered via on-body injector. GlobeNewswire. July 10, 2026.

    Drugs.com approval news: FDA Approves Sarclisa Escena (isatuximab-irfc) Subcutaneous Injection for the Treatment of Multiple Myeloma. drugs.com. July 10, 2026.

    IRAKLIA primary JCO publication: Richardson PG et al. Isatuximab Subcutaneous by On-Body Injector Versus Isatuximab Intravenous Plus Pomalidomide and Dexamethasone in Relapsed/Refractory Multiple Myeloma: Phase III IRAKLIA Study. Journal of Clinical Oncology. 2025. doi:10.1200/JCO-25-00744.

    IRAKLIA trial registration: NCT05405166. ClinicalTrials.gov.

    ASCO Post clinical summary: FDA Approves Isatuximab-irfc for Subcutaneous Injection for Multiple Myeloma Indications. ascopost.com. July 2026.

    OncLive (OBI mechanism, safety data, IZALCO preference data): FDA Approves Subcutaneous Isatuximab Delivered Via On-Body Delivery System for Multiple Myeloma. onclive.com. July 2026.

    CancerNetwork (patient satisfaction OR data): FDA Approves Subcutaneous Isatuximab in Multiple Myeloma. cancernetwork.com. July 2026.

    Targeted Oncology (full indications and supporting studies): FDA Approves Subcutaneous Isatuximab for Multiple Myeloma. targetedonc.com. July 2026.

    PharmExec (CirCLIQ mechanism detail and competitive context): FDA Approves Subcutaneous Sarclisa Escena for Multiple Myeloma. pharmexec.com. July 2026.

    BioPharm International (IRAKLIA full data table, EC approval context): EC Approves Sanofi’s Subcutaneous Isatuximab for Multiple Myeloma Across All Existing Indications. biopharminternational.com. June 2026.

    Applied Clinical Trials (IRAKLIA/IZALCO combined data summary): Phase III IRAKLIA and Phase II IZALCO Trials Support Sarclisa On-Body Delivery. appliedclinicaltrialsonline.com. October 2025.

    International Myeloma Foundation approval news: Subcutaneous Sarclisa (isatuximab-irfc) FDA Approved for Myeloma. myeloma.org. July 2026.

    OncoDaily clinical overview: FDA Approved Subcutaneous Isatuximab: Advancing Anti-CD38 Therapy Delivery in Multiple Myeloma. oncodaily.com. July 2026.

    ASH 2025 body weight PK sub-analysis: Isatuximab Subcutaneous by On-Body Injector in R/R MM: Effect of Body Weight on Pharmacokinetics. Blood. 2025;146(Supplement 1):5812.

    IZALCO trial registration: NCT05704049. ClinicalTrials.gov.

    ISASCOUT trial registration: NCT05889221. ClinicalTrials.gov.

    IV Sarclisa original FDA approval: FDA approves isatuximab-irfc for multiple myeloma. FDA.gov.

    CD38 biology: CD38 in Multiple Myeloma. PMC7734386.

    Multiple myeloma overview: Multiple Myeloma. StatPearls. NCBI.

    Sarclisa Escena prescribing information: SARCLISA ESCENA (isatuximab-irfc) Prescribing Information. Sanofi-Aventis. 2026.

    Sarclisa Escena approval history: Sarclisa Escena FDA Approval History. drugs.com.

    Enable Injections (CirCLIQ manufacturer): Enable Injections. enableinjections.com.

    Patient resources: Multiple Myeloma Research Foundation: 1-888-841-6673 | International Myeloma Foundation: 1-800-452-CURE | Leukemia and Lymphoma Society | Sanofi Sarclisa patient support

    Disclaimer: Health Evidence Digest provides general information about FDA approvals and health research for educational purposes. This content is not a substitute for professional medical advice. Sarclisa Escena (isatuximab-irfc) is approved for subcutaneous administration and currently requires administration with a healthcare provider present. Treatment decisions for multiple myeloma, including regimen selection and the choice between IV Sarclisa and Sarclisa Escena SC, should be made in close collaboration with a board-certified hematologist or medical oncologist experienced in myeloma management.
  • IgA Nephropathy Silently Damages Kidneys for Years Before Most Patients Know It Is Happening. Trutakna Just Became the First Approved Therapy to Target Its Root Immunological Cause.

    The essentials: On July 7, 2026, the FDA granted accelerated approval to Trutakna (atacicept-vymj, Vera Therapeutics) to reduce proteinuria in adults with primary IgA nephropathy (IgAN) at risk for disease progression. Trutakna is a recombinant fusion protein that simultaneously inhibits both B-cell activating factor (BAFF) and A proliferation-inducing ligand (APRIL), two cytokines that drive the B-cell activity responsible for producing the abnormal IgA antibodies that cause this disease. It is the first and only FDA-approved therapy to block both BAFF and APRIL, making it mechanistically distinct from every other approved IgAN therapy. It is the sixth drug approved for IgAN in the United States, joining Tarpeyo (budesonide EC, Calliditas, 2021), Filspari (sparsentan, Travere, 2023), Voyxact/Fabhalta (iptacopan, Novartis, 2024), Vanrafia (atrasentan, Otsuka, 2024), and Kinpeygo (budesonide, released outside U.S.). Administration: 150 mg subcutaneous injection once weekly, self-administered by the patient at home using a pre-filled autoinjector. No infusion center required. The clinical basis: prespecified 36-week interim analysis of the ongoing Phase 3 ORIGIN 3 trial (NCT04716231), enrolling 431 adults with biopsy-confirmed IgAN. Analysis population: first 203 participants who received at least 1 dose. Primary endpoint: change in 24-hour urine protein-to-creatinine ratio (UPCR) compared to placebo at 36 weeks. Results: 46% reduction from baseline in UPCR (atacicept arm); 42% reduction versus placebo (p less than 0.0001). Important caveat: this is an accelerated approval based on reduction of proteinuria as a surrogate endpoint. It has not yet been established whether Trutakna slows kidney function decline over the long term, as measured by eGFR. Continued approval may be contingent on confirmatory eGFR data from the ongoing ORIGIN 3 trial, which Vera Therapeutics and the FDA have agreed to analyze earlier than originally planned. eGFR results are anticipated in Q3 2026. An sBLA for full approval is targeted for Q4 2026. BLA accepted with Priority Review in January 2026. Safety signals: infections in 32% (atacicept) versus 28% (placebo); injection site reactions in 30% (atacicept) versus 5% (placebo); live vaccines are contraindicated during treatment.

    IgA nephropathy is the most common biopsy-proven primary glomerulonephritis worldwide, yet most patients who have it don’t know for years. The disease begins silently, with abnormal IgA antibodies depositing in the glomeruli of the kidneys and slowly damaging the filtering units that keep waste in the urine and protein in the bloodstream. The first sign is often blood in the urine after an upper respiratory infection, or protein showing up on a routine urinalysis. The diagnosis requires a kidney biopsy. And between 30% and 50% of untreated patients will progress to kidney failure within 20 to 25 years.

    For most of the history of nephrology, treatment consisted of blood pressure control, RAAS blockade to reduce proteinuria, and in some patients a course of systemic corticosteroids with their accompanying side effects and limited long-term efficacy. Then, between 2021 and 2024, the IgAN treatment landscape transformed rapidly as the FDA approved five drugs targeting different aspects of the disease’s pathophysiology.

    Trutakna (atacicept-vymj, Vera Therapeutics), approved July 7, 2026, is the sixth. What makes it mechanistically important within this crowded field is that it targets the disease earlier in its pathogenic cascade than any of the others: at the B-cell cytokine level where the abnormal IgA antibody production begins, using a dual-target approach that blocks both BAFF and APRIL simultaneously. No other approved IgAN drug does this. The 36-week Phase 3 interim data showed a 42% reduction in proteinuria versus placebo. Whether that proteinuria reduction translates into preserved kidney function over years is the critical question, and the answer is coming soon.


    What IgA Nephropathy Is: The Four-Hit Disease

    IgA nephropathy, also known as Berger’s disease after the French nephrologist Jean Berger who first described it in 1968, is defined by mesangial deposits of IgA-dominant immune complexes in the kidney. Understanding what goes wrong requires following a sequence of immunological events that researchers now describe as the “four-hit hypothesis.”

    Hit 1: Aberrant IgA1 glycosylation. IgA1, one of the two subclasses of IgA antibody, has a hinge region with multiple O-linked glycan chains. In patients with IgAN, these glycans are incompletely formed: they lack the normal galactose residues and are described as galactose-deficient IgA1 (Gd-IgA1). Gd-IgA1 is produced in higher quantities in IgAN patients than in healthy individuals and is the molecular abnormality that drives the entire downstream cascade.

    Hit 2: Autoantibody production. The body recognizes the aberrant Gd-IgA1 as foreign and produces anti-glycan autoantibodies (IgG and IgA) directed against the abnormal sugar residues. These autoantibodies are the second abnormality.

    Hit 3: Immune complex formation. The autoantibodies bind to circulating Gd-IgA1 to form large immune complexes. These complexes circulate in the bloodstream and are too large to be efficiently cleared by normal mechanisms.

    Hit 4: Mesangial deposition and kidney injury. The immune complexes deposit in the mesangium, the connective tissue between the glomerular capillaries. Mesangial cells respond by proliferating and producing inflammatory cytokines and extracellular matrix proteins. The complement system is activated through the lectin and alternative pathways. The resulting glomerular inflammation and fibrosis progressively damage the kidney’s filtering function, reflected clinically as proteinuria, hematuria, and eventually declining eGFR.

    The critical insight from this four-hit model is that hit 1, the overproduction of Gd-IgA1, is fundamentally a B-cell problem. The abnormal antibodies come from B cells and plasma cells that have been inappropriately activated by cytokines in the mucosa and lymphoid tissue. This is where BAFF and APRIL become central to the pathophysiology and where Trutakna’s mechanism fits.

    Why IgAN is more common in some populations than others IgAN is the most common primary glomerulonephritis worldwide, but its distribution is uneven. Prevalence is highest in East Asia, where IgAN accounts for 40% to 50% of biopsy-proven glomerulonephritis cases. In Europe it accounts for 20% to 30%, and in North America 10% to 20%. The higher prevalence and more aggressive disease course in East Asian populations likely reflects both genetic susceptibility variants and differences in mucosal immune activation. Overall incidence is at least 2.5 cases per 100,000 adults per year. In practical terms, given that kidney biopsies are not performed as readily in all healthcare systems, IgAN is almost certainly substantially underdiagnosed, with many patients carrying the disease without a confirmed pathological diagnosis.

    How Atacicept Works: Dual BAFF and APRIL Inhibition

    BAFF (B-cell activating factor, also known as BLyS) and APRIL (A proliferation-inducing ligand) are two cytokines produced primarily by innate immune cells, dendritic cells, macrophages, and epithelial cells in response to mucosal immune stimulation. Both act on receptors expressed on B cells and plasma cells (the antibody-secreting cell type that B cells mature into) to promote their survival, proliferation, and differentiation into antibody-producing cells.

    In IgAN, both BAFF and APRIL are overexpressed, particularly in mucosal sites including the gut-associated lymphoid tissue and tonsils, which are thought to be the primary sites of Gd-IgA1 production. The elevated BAFF and APRIL levels drive excessive B-cell and plasma cell survival, amplifying the production of both Gd-IgA1 itself and the autoantibodies that bind it to form immune complexes. Reducing BAFF and APRIL levels should reduce this aberrant B-cell activity, lower Gd-IgA1 and autoantibody production, and thereby reduce the formation and mesangial deposition of pathogenic immune complexes.

    Atacicept is a recombinant fusion protein combining the extracellular domain of the transmembrane activator and calcium modulator and cyclophilin ligand interactor (TACI) receptor with the Fc portion of human IgG1. TACI is the receptor that naturally binds both BAFF and APRIL. By mimicking this receptor in soluble form, atacicept acts as a decoy: it captures both BAFF and APRIL in the circulation before they can bind to B cells and plasma cells, neutralizing both cytokines simultaneously.

    This dual neutralization is the key mechanistic distinction from the only other APRIL-directed therapy approaching approval for IgAN: sibeprenlimab (Vertex Pharmaceuticals), which targets only APRIL. Whether blocking both BAFF and APRIL provides additive clinical benefit over blocking APRIL alone is a question that current trial programs will ultimately need to address through comparative data or head-to-head studies. The available data suggest meaningful clinical activity for both approaches; which performs better in the long term remains to be established.

    Other approved IgAN therapies address the disease through entirely different mechanisms: Tarpeyo and Kinpeygo target mucosal IgA production through gut-targeted corticosteroid action; Filspari combines endothelin A receptor blockade with angiotensin receptor blockade (sparsentan); Vanrafia blocks the endothelin A receptor (atrasentan); and Fabhalta inhibits complement factor B (iptacopan). The mechanistic diversity of the approved IgAN landscape reflects the multiple pathogenic pathways contributing to the four-hit cascade and provides clinicians and patients with options targeting different aspects of the disease.


    The ORIGIN 3 Trial: What the Data Shows and What It Does Not Yet Establish

    Trial design

    ORIGIN 3 (NCT04716231) is an ongoing global, multicenter, randomized, double-blind, placebo-controlled Phase 3 trial enrolling 431 adults with biopsy-confirmed primary IgAN. Patients were randomized 1:1 to atacicept 150 mg administered subcutaneously once weekly via autoinjector or placebo. The trial is still running in its placebo-controlled, blinded phase to evaluate the primary long-term efficacy endpoint of change in eGFR.

    The accelerated approval was based on a prespecified interim analysis of the first 203 patients who received at least 1 dose of atacicept or placebo and had reached the 36-week assessment point. The primary endpoint of this interim analysis was change in 24-hour urine protein-to-creatinine ratio (UPCR) from baseline to week 36.

    Efficacy results at 36 weeks

    EndpointAtacicept (n=approximately 101)Placebo (n=approximately 102)Result
    UPCR reduction from baseline46%ReferenceStatistically significant and clinically meaningful
    UPCR reduction versus placebo42%Referencep less than 0.0001
    Analysis timing36-week prespecified interim36-week prespecified interimPer prespecified analysis plan

    Source: Vera Therapeutics FDA approval press release. GlobeNewswire. July 7, 2026. ORIGIN 3 NCT04716231.

    A 42% reduction in UPCR compared to placebo at 36 weeks is a clinically meaningful reduction in proteinuria. In IgAN clinical trials and regulatory frameworks, proteinuria measured by UPCR is now an accepted surrogate endpoint for predicting long-term kidney outcomes, based on consistent observational data showing that proteinuria reduction correlates with slower eGFR decline over years of follow-up. The FDA accepted proteinuria reduction as the basis for accelerated approval across multiple prior IgAN approvals, including Tarpeyo, Filspari, and Fabhalta.

    What is not yet established

    The prescribing label for Trutakna includes a critical qualification that patients and clinicians should understand directly:

    “This indication is approved under accelerated approval based on a reduction of proteinuria. It has not been established whether Trutakna slows kidney function decline over the long-term in patients with IgAN. Continued approval for this indication may be contingent upon verification and description of clinical benefit in the ongoing ORIGIN 3 trial.”

    In plain terms: the drug reduces proteinuria, and proteinuria is a surrogate marker for kidney health. But the confirmatory evidence showing that this proteinuria reduction actually translates into slower kidney function loss over years, as measured by eGFR trajectory, has not yet been generated. That evidence is coming from the ongoing ORIGIN 3 trial, and Vera Therapeutics has stated it reached agreement with the FDA to conduct the eGFR analysis earlier than originally planned. Results are anticipated in Q3 2026, and a supplemental BLA for full approval is targeted for Q4 2026.

    This is the standard accelerated approval pathway in IgAN and is not unique to atacicept. The entire recent IgAN drug approval wave has followed this same proteinuria-first-then-eGFR framework. The precedent for conversion to full approval on confirmatory eGFR data in IgAN has been established by prior approvals in this space. Whether ORIGIN 3’s eGFR data confirms the expected clinical benefit is the question that matters most for long-term prescribing confidence.


    The IgAN Treatment Landscape After July 2026

    Understanding where Trutakna fits requires seeing the full current picture of approved IgAN therapies and their distinct mechanisms:

    DrugCompanyMechanismFDA approvalApproval type
    Tarpeyo (budesonide EC)CalliditasGut-targeted corticosteroid (reduces mucosal IgA production)December 2021Accelerated; full approval 2023
    Filspari (sparsentan)TravereDual endothelin A and angiotensin receptor antagonistFebruary 2023Accelerated; full approval 2024
    Fabhalta (iptacopan)NovartisComplement factor B inhibitorAugust 2024Accelerated
    Vanrafia (atrasentan)OtsukaSelective endothelin A receptor antagonistAugust 2024Full approval (ALIGN trial)
    Voyxact (iptacopan)NovartisComplement factor B inhibitorFull complement indicationOverlapping with Fabhalta
    Trutakna (atacicept)Vera TherapeuticsDual BAFF and APRIL inhibitorJuly 7, 2026Accelerated

    Note: Sibeprenlimab (Vertex), targeting APRIL only, is in Phase 3 and has not yet been approved.

    The mechanistic diversity of this landscape matters clinically. Patients with IgAN may benefit from different approaches depending on where in the four-hit cascade their disease is most driven, their comorbidities and contraindications, and the specific features of their disease at the time of treatment initiation. Atacicept’s upstream B-cell cytokine targeting provides an option that addresses the source of Gd-IgA1 production, which is distinct from the complement inhibition, hemodynamic, and mucosal corticosteroid approaches of other approved drugs.

    The competitive landscape also creates questions about combination therapy: could addressing multiple pathogenic steps simultaneously, such as reducing Gd-IgA1 production with atacicept while blocking complement activation with iptacopan, provide additive benefit? These are questions that ongoing research will address but that are outside the current label for any of these agents.


    Dosing and Administration

    Trutakna is administered as a 150 mg subcutaneous injection once weekly. The injection is self-administered by the patient at home using a pre-filled autoinjector. Injection sites include the abdomen, thigh, or upper arm, rotating sites with each weekly injection.

    The home self-administration model is a meaningful practical advantage for a drug intended for long-term use in a patient population managing a chronic progressive kidney disease. Patients receive training on autoinjector technique before beginning self-injection, typically through Vera Therapeutics’ patient support program.

    No dose adjustment is specified for mild to moderate renal impairment, which is relevant because many IgAN patients present with some degree of kidney function reduction at the time of treatment initiation. Prescribing information should be reviewed for guidance in patients with more severe renal impairment.


    Safety: What the ORIGIN 3 Data Covers

    The safety profile from the ORIGIN 3 interim analysis was broadly consistent with the class-level risks of BAFF and APRIL inhibition, reflecting their roles in B-cell homeostasis and immune function.

    Key safety findings from ORIGIN 3 interim:

    Safety itemAtaciceptPlaceboClinical relevance
    Any infection32%28%Modest increase; B-cell suppression reduces immune competence
    Injection site reactions30%5%The most distinct adverse event profile for atacicept; predominantly mild local reactions
    Serious infectionsLow absolute rateLow absolute rateMonitor for serious or unusual infections throughout treatment

    Warnings and precautions from the Trutakna prescribing information:

    Serious infections: BAFF and APRIL support B-cell survival and function. By inhibiting both, atacicept reduces B-cell populations and the antibodies they produce, including normal protective antibodies. This creates a degree of immunosuppression that increases infection susceptibility. Serious infections requiring hospitalization have been reported. Clinicians should assess for active infection before initiating Trutakna and should not initiate in patients with active infections. Patients should be monitored for infection throughout treatment and instructed to report new symptoms promptly.

    Live vaccines contraindicated: Because Trutakna suppresses B-cell function and antibody responses, live attenuated vaccines should not be administered to patients receiving the drug. Vaccinations with live vaccines should be completed before initiating treatment. Non-live vaccines may have reduced efficacy during treatment; the timing of non-live vaccinations relative to atacicept dosing should be discussed with the prescriber.

    Hypogammaglobulinemia: Sustained BAFF and APRIL inhibition can reduce immunoglobulin levels over time. Monitoring of immunoglobulin levels is recommended. Patients with pre-existing hypogammaglobulinemia may be at higher risk for infectious complications.

    Hypersensitivity reactions: Serious hypersensitivity reactions have been reported with atacicept. Patients should be observed after injection for signs of hypersensitivity and instructed to seek medical attention for any serious reaction.

    Embryo-fetal toxicity: Atacicept can cause fetal harm based on its mechanism of action affecting B-cell development. Females of reproductive potential should use effective contraception during treatment and for a specified period after the last dose. Pregnancy testing before initiating treatment is recommended for females of reproductive potential.


    What This Means for Patients and Clinicians

    For patients with primary IgAN

    Trutakna adds a meaningful new option to the IgAN treatment landscape, particularly for patients who have not achieved adequate proteinuria control on existing therapies, who are intolerant to current options, or whose disease is driven primarily by the upstream B-cell cytokine pathways that BAFF and APRIL regulation addresses.

    The practical advantages of Trutakna for patients include once-weekly home self-administration (eliminating infusion center visits), a well-defined and manageable side effect profile, and a mechanism that targets the immunological source of the disease rather than its downstream consequences.

    The important transparency point every patient deserves: the approval is based on reducing proteinuria, a surrogate marker. The evidence that this proteinuria reduction translates into slower progression to kidney failure, the outcome that matters most, is currently awaited from the ongoing ORIGIN 3 confirmatory analysis. This is not a reason to avoid the drug, because every other recently approved IgAN drug followed the same pathway, and the proteinuria-to-eGFR correlation is well-established. But it is information that should be part of a shared decision-making conversation with your nephrologist.

    The confirmatory eGFR data expected in Q3 2026 will be one of the most watched datasets in nephrology this year. If ORIGIN 3 shows preserved kidney function alongside the proteinuria reduction, the case for Trutakna in the IgAN treatment algorithm will strengthen considerably.

    For nephrologists

    Trutakna’s dual BAFF/APRIL mechanism fills a specific niche in the IgAN therapeutic landscape: upstream B-cell cytokine targeting for patients where reducing aberrant Gd-IgA1 production is the primary therapeutic goal. The 42% placebo-adjusted UPCR reduction at 36 weeks is consistent with the proteinuria reduction seen with other approved IgAN agents and provides a basis for use in clinical practice pending confirmatory eGFR data.

    The comparative effectiveness question between atacicept and sibeprenlimab (APRIL-only inhibition), and between both of these upstream B-cell targeting approaches and the complement, hemodynamic, and mucosal corticosteroid approaches, will take years of real-world experience and potentially head-to-head trials to fully resolve. In the meantime, the mechanistic diversity of the approved IgAN landscape supports individualized treatment selection based on patient disease characteristics, comorbidities, and prior therapy history.

    The infection monitoring consideration and the live vaccine contraindication are the most practically important safety management points for ongoing surveillance in atacicept-treated patients.

    For related HED coverage on rare kidney disease and immunology drug approvals, see our post on Tregzi (marnetegragene autotemcel-vldq) receiving FDA approval as the first precision-engineered cell therapy for allogeneic stem cell transplantation and our coverage of the Lumvoa (veligrotug-vvze) approval for thyroid eye disease across both active and chronic disease phases.

    If you or a family member has been diagnosed with IgA nephropathy, the National Kidney Foundation (kidney.org; 1-800-622-9010) and the IgA Nephropathy Foundation maintain current patient resources, treatment information, and clinical trial directories.


    Sources

    Vera Therapeutics FDA approval press release: Vera Therapeutics Receives FDA Accelerated Approval for TRUTAKNA for Adult Patients with Primary IgA Nephropathy. GlobeNewswire. July 7, 2026.

    Drugs.com approval news: FDA Grants Accelerated Approval for Trutakna (atacicept-vymj) for Adult Patients with Primary IgA Nephropathy. drugs.com. July 7, 2026.

    HCPLive clinical summary (ORIGIN 3 data, safety profile): FDA Approves Atacicept (Trutakna) for IgA Nephropathy. hcplive.com. July 2026.

    AJMC clinical and competitive landscape analysis: FDA Approves Atacicept for IgA Nephropathy. ajmc.com. July 2026.

    Fierce Pharma (competitive landscape, sibeprenlimab context): Vera’s dual-target atacicept wins FDA approval for IgAN. fiercepharma.com. July 2026.

    Pharmaceutical Commerce (specialty launch context): What Trutakna’s Approval Means for Specialty Launches. pharmaceuticalcommerce.com. July 2026.

    Trutakna approval history: Trutakna FDA Approval History. drugs.com.

    ORIGIN 3 trial registration: NCT04716231. ClinicalTrials.gov.

    BAFF and APRIL role in IgAN pathogenesis: The role of BAFF and APRIL in IgA nephropathy: pathogenic mechanisms and targeted therapies. PMC10867227.

    IgAN four-hit pathophysiology: The Pathophysiology of IgA Nephropathy. PMC3892742.

    Gd-IgA1 and immune complex formation: The Origin and Activities of IgA1-Containing Immune Complexes in IgA Nephropathy. PMC4828451.

    IgAN clinical trials overview: IgA Nephropathy: An Overview of the Clinical Trials. Kidney Medicine. 2025.

    IgAN StatPearls overview: IgA Nephropathy (Berger Disease). StatPearls. NCBI.

    Tarpeyo FDA approval: FDA approves budesonide for IgA nephropathy. FDA.gov.

    Filspari FDA approval: FDA approves sparsentan for IgA nephropathy. FDA.gov.

    Fabhalta/Voyxact FDA approval: FDA approves iptacopan for IgA nephropathy. FDA.gov.

    Vanrafia FDA approval: FDA approves atrasentan for IgA nephropathy. FDA.gov.

    Trutakna prescribing information: TRUTAKNA (atacicept-vymj) Prescribing Information. Vera Therapeutics. 2026.

    KDIGO 2025 IgAN guideline: Executive summary of the KDIGO 2025 Clinical Practice Guideline for the Management of IgA Nephropathy and IgA Vasculitis. Kidney Int. 2025;108(4):548-554.

    Patient resources: National Kidney Foundation: 1-800-622-9010 | IgA Nephropathy Foundation | American Kidney Fund | Vera Therapeutics patient support

    Disclaimer: Health Evidence Digest provides general information about FDA approvals and health research for educational purposes. This content is not a substitute for professional medical advice. Trutakna received accelerated approval based on reduction of proteinuria as a surrogate endpoint; it has not yet been established that the drug slows long-term kidney function decline. Decisions about initiating Trutakna for primary IgA nephropathy should be made in close consultation with a board-certified nephrologist who can evaluate proteinuria levels, eGFR trajectory, kidney biopsy findings, and all treatment options in the context of each individual patient’s disease characteristics.